ACR Meeting Abstracts

ACR Meeting Abstracts

  • Meeting Abstracts
    • All Meetings
    • ACR Convergence 2026
    • PRSYM 2026
    • ACR Convergence 2025
    • Download Abstract Supplements
  • Keyword Index
  • My Favorites
    • View & print my favorites
  • Search

Home » Meeting Abstracts » ACR Convergence 2024

Abstract Number: 2475

The Critical Role of Annual HRCT in Identifying ILD Progression and Assessing Outcome in SSc

Anna-Maria Hoffmann-Vold1, Simon Beyeler2, Liubov Petelytska3, Håvard Fretheim1, Trond Mogens Aaløkken4, Mike Becker5, Hilde Jenssen Bjørkekjær6, Cathrine Brunborgg1, Cosimo Bruni7, Christian Clarenbach8, Phuong Phuong Diep9, Rucsandra Dobrota7, Michael T Durheim1, Muriel Elhai10, Thomas Frauenfelder8, Suzana Jordan7, Emily Langballe11, Øyvind Midtvedt12, Carina Mihai7, Adela Sarbu8, Marco Sprecher8, Øyvind Molberg13 and Oliver Distler14, 1Oslo University Hospital, Oslo, Norway, 2University Hospital Zurich, Zürich, Zurich, Switzerland, 3University Hospital Zurich, Zurich, Switzerland, 4Medicine, Oslo, Norway, Oslo, Norway, 5Center of Experimental Rheumatology, Department of Rheumatology, University Hospital Zurich, University of Zurich, Zürich, Switzerland, 6Department of Rheumatology, Hospital of Southern Norway, Kristiansand, Kristiansand, Norway, 7University Hospital Zurich, University of Zurich, Zurich, Switzerland, 8University Hospital Zurich, Zurich, Zurich, Switzerland, 9Oslo University Hospital, Department of Respiratory Disease, Oslo, Norway, 10University Hospital zurich, Zürich, Switzerland, 11Oslo University Hospital, Department of Rheumatology, Oslo, Norway, 12Oslo University Hospital, Oslo, Oslo, Norway, 13Department of Rheumatology, Oslo University Hospital, Rikshospitalet, Oslo, Norway, 14Department of Rheumatology, University Hospital Zurich, University of Zurich, Zurich, Switzerland, Zurich, Switzerland

Share on X (Twitter) Share on Facebook Share on LinkedIn Share on Email
Print

Meeting: ACR Convergence 2024

Keywords: Imaging, interstitial lung disease, prognostic factors, Systemic sclerosis

Session Information

Date: Monday, November 18, 2024

Title: Systemic Sclerosis & Related Disorders – Clinical Poster III

Session Type: Poster Session C

Session Time: 10:30AM-12:30PM

Background/Purpose: Progression of interstitial lung disease (ILD) reduces long-term survival in patients with systemic sclerosis (SSc). Monitoring with lung function testing every 3–6 months for the 1st year and less frequently afterwards is recommended in the recent ACR/Chest guidelines. Follow-up HRCT is recommended as needed. The objective of this study was to assess the impact of serial HRCT to identify ILD progression and its ability to predict mortality.

Methods: We included all SSc-ILD patients from Oslo and Zurich with ILD on HRCT, and available consecutive annual lung function assessments including forced vital capacity (FVC) and diffusing capacity for carbon monoxide (DLCO), HRCT, respiratory symptoms, and vital status at study end. ILD progression was defined by the 2022 ATS/ERS/JRS/ALAT guideline progressive pulmonary fibrosis (PPF) criteria over 12 ±3 months. The PPF criteria are consisting of the following with the subcriteria (1) worsening of respiratory symptoms; (2) absolute decline in FVC ≥5% or in DLCO ≥10% and (3) disease progression on HRCT. HRCTs were assessed by an experienced radiologist. We assessed the prevalence of PPF and the subcriteria comprising the definition. Cox regression was applied to identify the impact of PPF and its subcriteria on mortality. Kaplan Meier estimates were used to analyze 3-year survival.

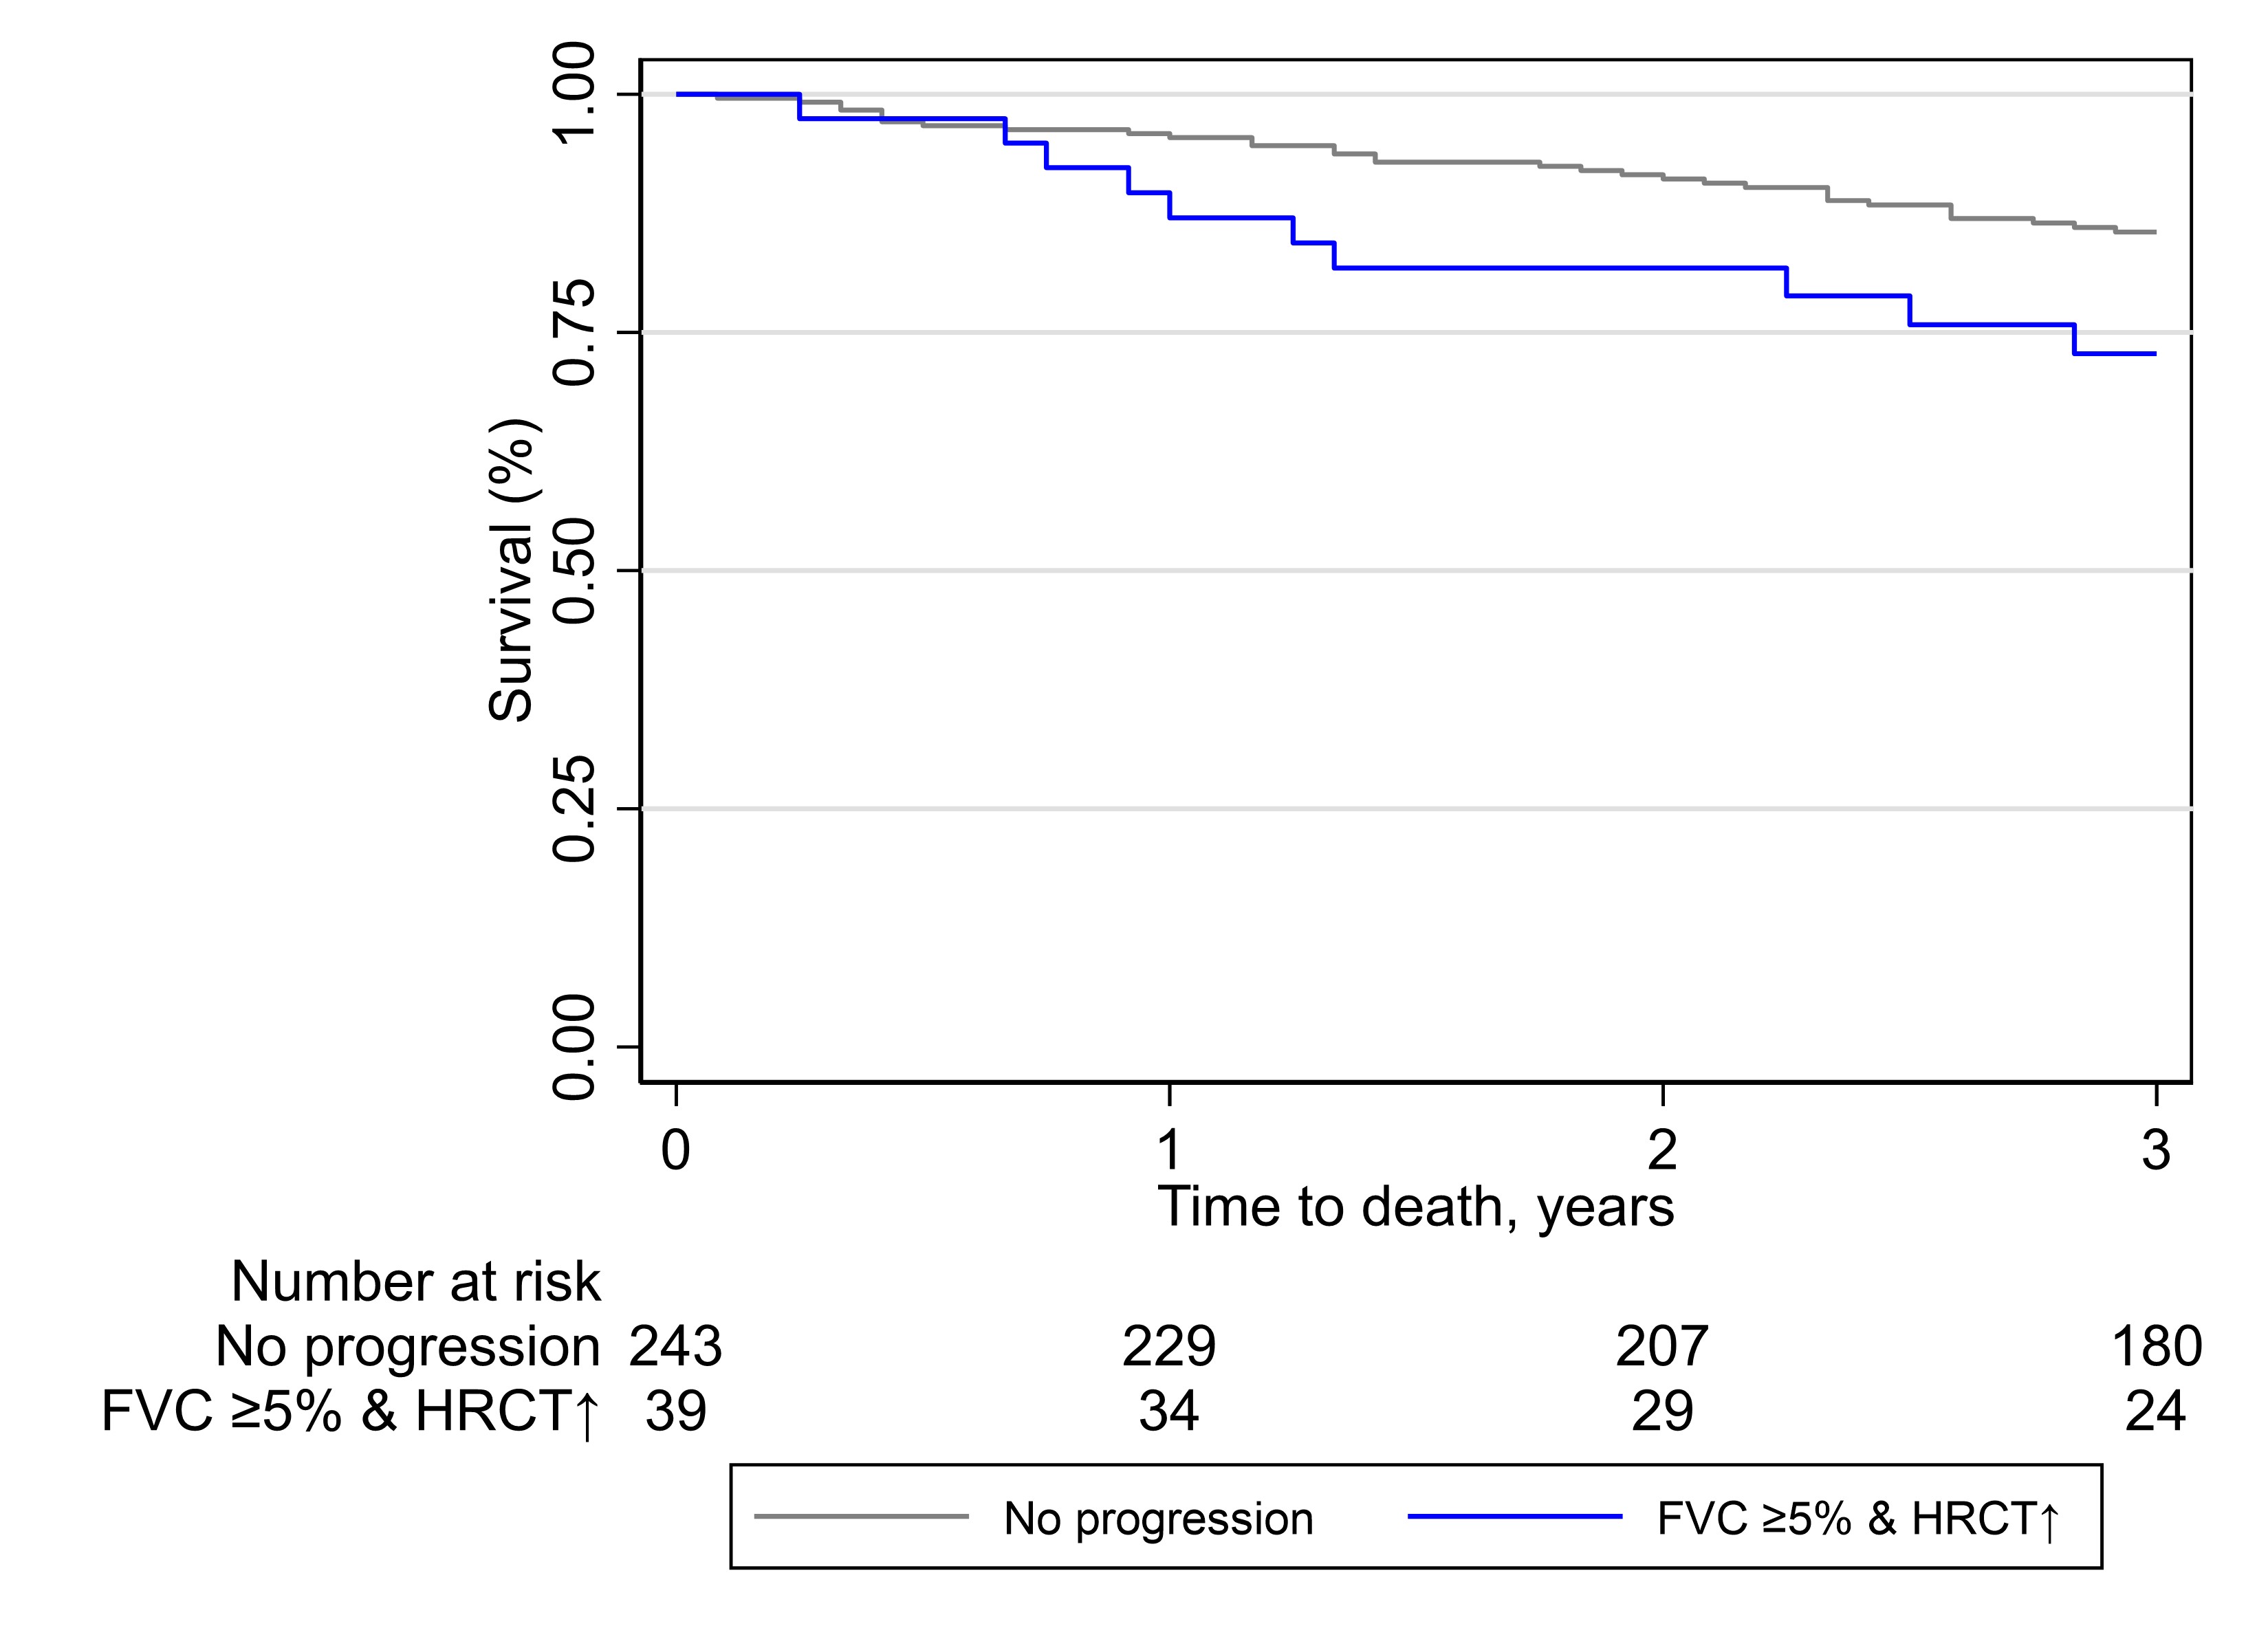
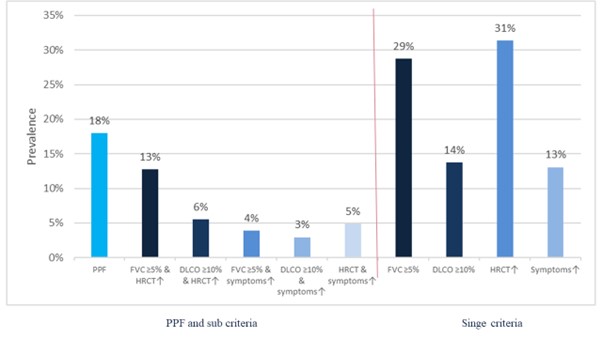
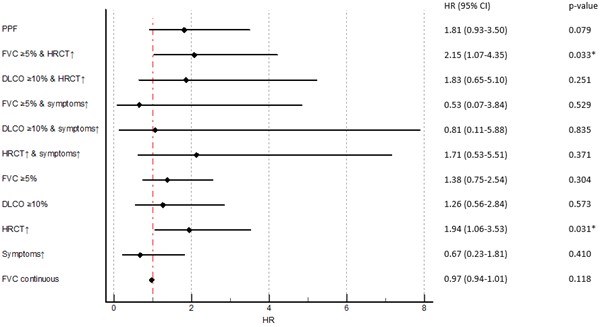
Results: We identified 306 SSc-ILD patients mirroring a typical SSc-ILD population with 74 (24%) males, 120 (39%) with diffuse SSc, 114 (37%) with anti-topoisomerase I antibodies, mean disease duration of 9.3 (±11.3) years, mean FVC of 87% (±19.8), DLCO of 65% (±19.6) and 81 (28%) with >20% of fibrosis on HRCT. We identified 55 (18%) SSc-ILD patients with PPF over 12 ±3 months. Fulfilment of the PPF criteria was mainly driven by the combination of absolute FVC decline ≥5% and worsening on HRCT (39 (13%)), followed by absolute DLCO decline ≥10% and worsening on HRCT (17 (6%)) and worsening on HRCT and respiratory symptoms (15 (5%)) (Figure 1). We assessed the impact of PPF and its subcategories on mortality and determined which specific criteria had the strongest impact. Over mean 3.5 (±0.87) years, 45 (15%) patients died, with 12 (27%) showing PPF over the first 12 months. While PPF itself was not associated with mortality, worsening on HRCT alone as well as in combination with FVC ≥5% decline predicted mortality (Figure 2). PPF showed no significant association with 3-year-mortality, but the combination of worsening on HRCT and absolute FVC decline ≥5% was significantly reducing the 1- and 3-year survival with p=0.039 (Figure 3).

Conclusion: Worsening on HRCT is the driving parameter of the PPF criteria and the strongest predictor for reduced survival. Annual HRCT is therefore of high important to identify ILD progression in SSc and to risk-stratify patients. Not using HRCT leads to missed opportunities for timely identification of ILD progression and for optimized disease management.
Supporting image 1

Figure 1: Prevalence of PPF and its sub criteria in SSc-ILD

Supporting image 2

Figure 2: The impact of PPF and its sub criteria on mortality assessed by cox regression

Supporting image 3

Figure 3: The impact of FVC decline and worsening of ILD on HRCT (blue) compared to no worsening (grey) on 3-year survival assessed by Kaplan-Meier estimates (p=0.039)


Disclosures: A. Hoffmann-Vold: Arxx Therapeutics, 2, Boehringer Ingelheim, 2, 5, 6, 12, Support for travel, Genentech, 2, Janssen, 2, 5, 6, Medscape, 2, 6, 12, Support for travel, Merck/MSD, 2, Novartis, 6, Pliant Therapeutics, 2, Roche, 2, 6, 12, Support for travel, Werfen, 2; S. Beyeler: None; L. Petelytska: None; H. Fretheim: Bo, 6; T. Aaløkken: None; M. Becker: Amgen, 2, 6, EMDO Foundation, 5, FOREUM, 5, GlaxoSmithKlein(GSK), 6, Innovative Medicines Initiative (IMI), 5, Novartis, 5, 6, Vifor, 2, 6; H. Jenssen Bjørkekjær: None; C. Brunborgg: None; C. Bruni: AbbVie/Abbott, 12, Educational grant, Boehringer-Ingelheim, 2, 12, Congress support, EMDO Foundation, 5, European Scleroderma Trials and Research Group (EUSTAR), 5, Foundation for research in Rheumatology (FOREUM), 5, Gruppo Italiano Lotta alla Sclerodermia (GILS), 5, Novartis Foundation for biomedical research, 5, Scleroderma Clinical Trials Consortium (SCTC), 5, Scleroderma Research Foundation (SRF), 5, Wellcome Trust, 12, Educational grant; C. Clarenbach: None; P. Diep: None; R. Dobrota: Actelion, 5, 6, Amgen, 12, Congress support, Boehringer-Ingelheim, 1, Iten-Kohaut Foundation, 5, Otsuka, 12, Congress support, Pfizer, 5, Walther and Gertrud Siegenthaler Fellowship, 5; M. Durheim: None; M. Elhai: AstraZeneca, 12, Congress support, Janssen, 12, Congress support, Novartis, 5; T. Frauenfelder: AGFA, 1, Boehringer-Ingelheim, 6, Bracco, 6; S. Jordan: None; E. Langballe: None; Ø. Midtvedt: None; C. Mihai: Boehringer-Ingelheim, 1, 6, 12, Congress support, Janssen, 1, MED Talks Switzerland, 6, Medbase, 6, Mepha, 6, Novartis, 1, 6, PlayToKnow, 6; A. Sarbu: None; M. Sprecher: None; Ø. Molberg: None; O. Distler: 4P-Pharma, 2, “mir-29 for the treatment of systemic sclerosis” (US8247389, EP2331143), 10, AbbVie, 2, Acceleron, 2, Alcimed, 2, Altavant Sciences, 2, Amgen, 2, AnaMar, 2, Arxx, 2, AstraZeneca, 2, Bayer, 2, 6, Blade Therapeutics, 2, Boehringer Ingelheim, 2, 5, 6, Citrus AG, 12, Co-founder, Corbus Pharmaceuticals, 2, CSL Behring, 2, EMD Serono, 2, ERS/EULAR Guidelines, 12, Co-Chair, EUSTAR, 12, President, FOREUM Foundation, 12, Chair of Executive Committee, Galapagos, 2, Glenmark, 2, Gossamer, 2, Hartmann Müller Foundation, 12, Member Board of Trustees, Horizon, 2, Janssen, 2, 6, Kymera, 2, 5, Lupin, 2, Medscape, 2, 6, Merck/MSD, 2, Miltenyi Biotec, 2, Mitsubishi Tanabe, 2, 5, Nkarta Inc., 2, Novartis, 2, Orion, 2, Prometheus Biosciences, 2, Redxpharma, 2, Roivant, 2, Swiss Academy of Medical Sciences, 12, Senat Member, Swiss Clinical Quality Management in Rheumatic Diseases, 12, Member Board of Trustees, Topadur, 2, UCB, 2.

To cite this abstract in AMA style:

Hoffmann-Vold A, Beyeler S, Petelytska L, Fretheim H, Aaløkken T, Becker M, Jenssen Bjørkekjær H, Brunborgg C, Bruni C, Clarenbach C, Diep P, Dobrota R, Durheim M, Elhai M, Frauenfelder T, Jordan S, Langballe E, Midtvedt Ø, Mihai C, Sarbu A, Sprecher M, Molberg Ø, Distler O. The Critical Role of Annual HRCT in Identifying ILD Progression and Assessing Outcome in SSc [abstract]. Arthritis Rheumatol. 2024; 76 (suppl 9). https://acrabstracts.org/abstract/the-critical-role-of-annual-hrct-in-identifying-ild-progression-and-assessing-outcome-in-ssc/. Accessed .

ACR Meeting Abstracts - https://acrabstracts.org/abstract/the-critical-role-of-annual-hrct-in-identifying-ild-progression-and-assessing-outcome-in-ssc/

My Favorites

Save and print abstracts during your browser session by clicking the “Favorite” button at the bottom of any abstract (must have cookies enabled in browser). See saved favorites.

Abstract Policies

  • ACR Convergence Abstract Embargo Policies
  • ACR Convergence Abstract Permissions & Reprints
  • PRSYM Abstract Policies

ACR Convergence. Where Rheumatology Meets

ACR Convergence 2026

Join us November 6-11 in Orlando, Florida.
See Registration Information

  • Contact ACR
  • Privacy Policy
  • ACR Policies
  • Cookie Preferences

© Copyright 2026 American College of Rheumatology