
Session Information
Date: Sunday, November 17, 2024
Session Type: Poster Session B
Session Time: 10:30AM-12:30PM
Background/Purpose: Improving health literacy in patients with rheumatic diseases is important, as many have chronic, complex diagnoses treated with high-risk medications. Poor health literacy puts patients at risk for healthcare disparity, and may be due to education level, language barriers, socioeconomic status and/or access to education material. While some factors are poorly remediable, others may improve with intervention. We piloted a quality improvement initiative to characterize patients’ health literacy and to improve their diagnosis and medication understanding via physician-provided education materials.
Methods: Patients with established rheumatic diagnoses from three distinct healthcare systems in New York City (public safety net, private teaching, Veterans Affairs (VA) hospitals) were administered surveys during clinic visits from September 2022-January 2024. A baseline survey assessed patients’ ability to identify their diagnoses and medications from a list of options. Primary language, education level, self-reported health literacy, and desire for more education material were documented. Printed education materials and counseling on knowledge gaps were provided in English or Spanish, and repeat surveys were administered at a follow-up visit to assess effectiveness of the intervention.
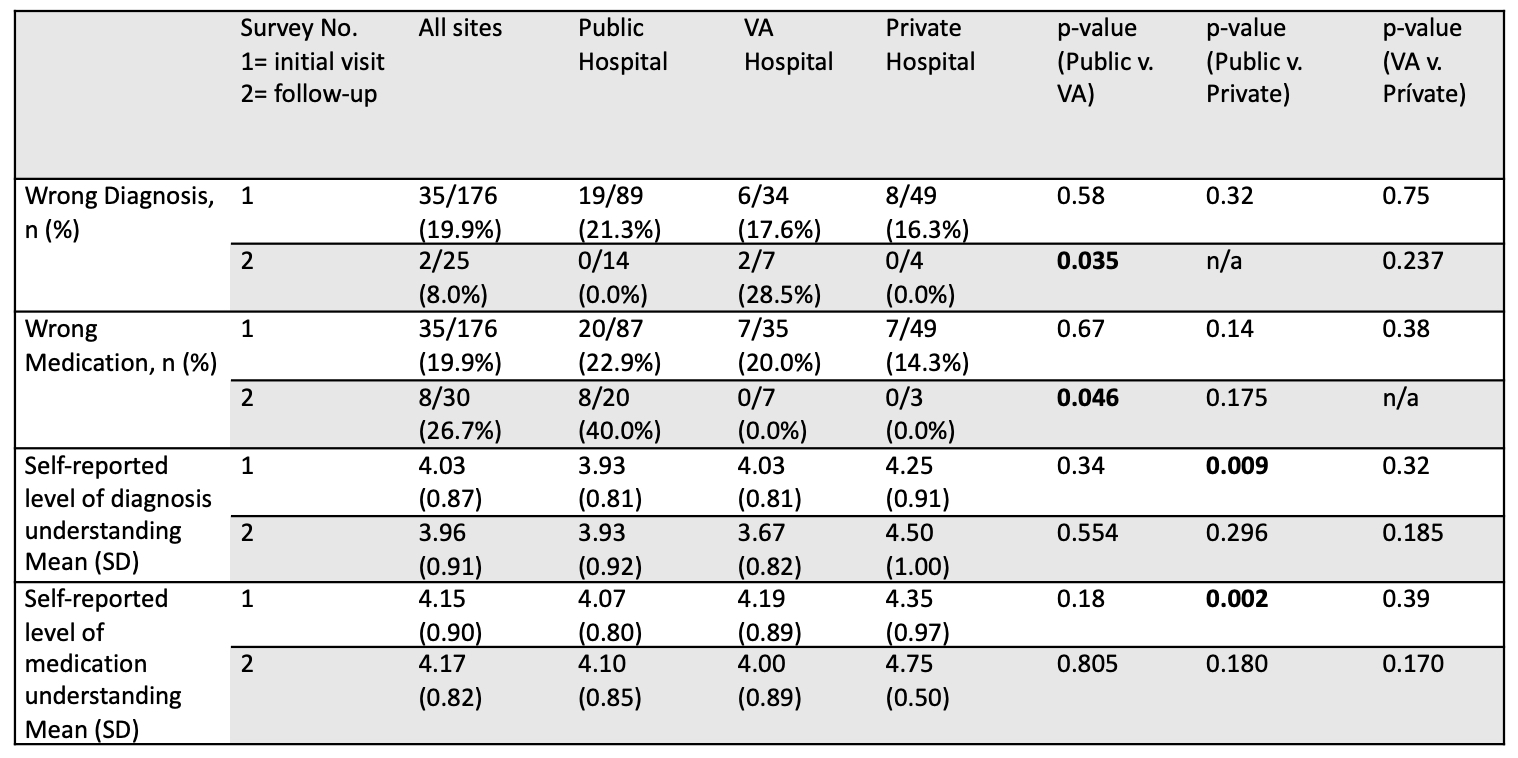
Results: 182 patients completed the baseline survey and 52 completed the follow-up survey over the 2-year study period. Overall, 19.9% of patients selected the wrong diagnosis at baseline and 8% selected the wrong diagnosis on follow-up surveys (Table 1). The greatest improvement was seen at the public hospital; initially 21.3% of patients selected a wrong diagnosis which improved to 0%. Across all sites, 19.9% of patients selected the wrong medications at baseline: at the private hospital and the VA, this decreased to 0% on follow-up, while it increased from 22.9% to 40% at the public hospital.
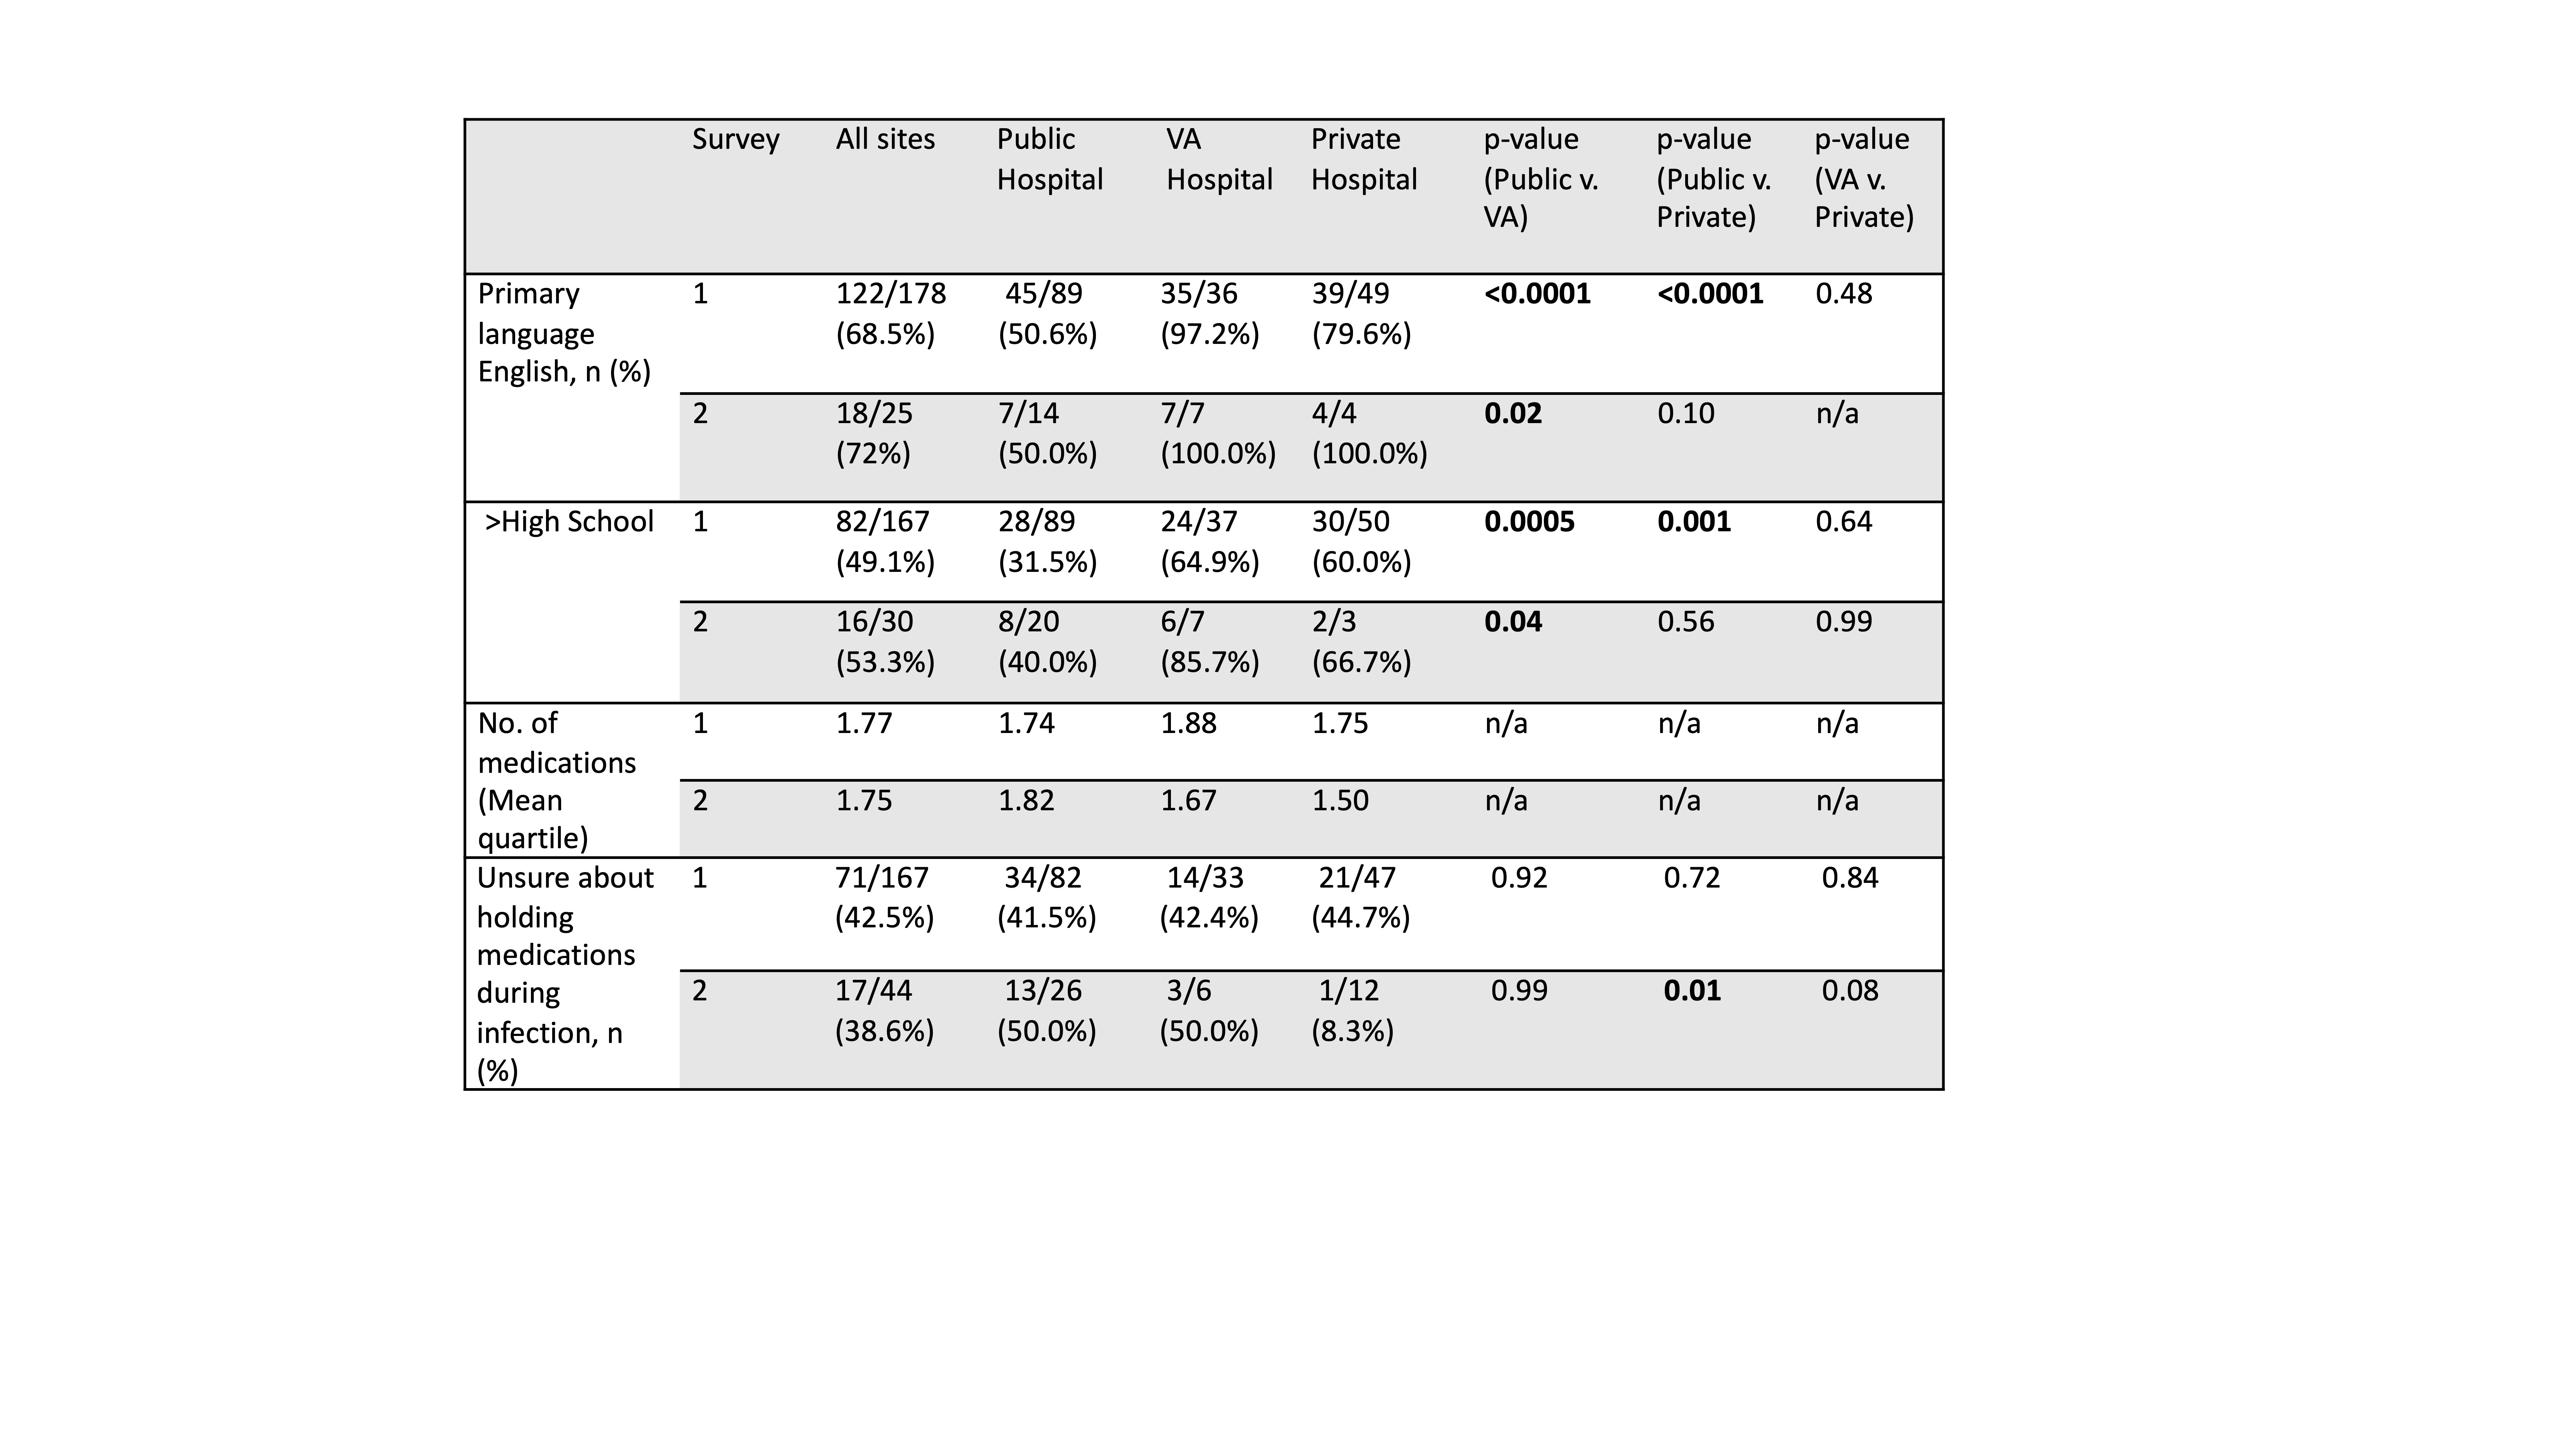
Self-reported level of understanding was quantified on a 1-5 scale (higher=better). At baseline, self-reported understanding of diagnoses and medications was lowest at the public hospital at 3.93 and 4.07, and highest at the private hospital at 4.25 and 4.35, respectively. Overall, 42.5% were unsure of when to stop medications during an infection, which decreased to 38.6% on follow-up (Table 2). Most patients desired more education material for both diagnoses and medications.
Conclusion: Rheumatology patients’ ability to correctly identify and understand their diagnoses and medications improved with provision of education material. However, patients’ ability to identify their medications did not improve at the public hospital, while it improved at the private and VA hospitals, suggesting that medication literacy is an area for intervention within public hospitals. In addition, patients at the public hospital were the most vulnerable population: they took the most medications, were least likely to speak English and to have attended college, and had lower self-reported level of understanding of diagnoses and medications. Our study highlights the importance of identifying and educating patients at highest risk of health disparity. The optimal way to improve patient health literacy is an important area for future study.
To cite this abstract in AMA style:
Leung N, Corbitt K, Howe C, Amarnani A, Law J, Sorrento C, Gutowski E, Novack J, Guan M, Goldberg S, Ahmed T, Anderson M, Pillinger M, Stream S. A 2-Year Pilot Project to Identify and Address Disparities in Health Literacy in Patients with Rheumatic Diseases Through Distribution of Surveys and Patient Education Materials [abstract]. Arthritis Rheumatol. 2024; 76 (suppl 9). https://acrabstracts.org/abstract/a-2-year-pilot-project-to-identify-and-address-disparities-in-health-literacy-in-patients-with-rheumatic-diseases-through-distribution-of-surveys-and-patient-education-materials/. Accessed .ACR Meeting Abstracts - https://acrabstracts.org/abstract/a-2-year-pilot-project-to-identify-and-address-disparities-in-health-literacy-in-patients-with-rheumatic-diseases-through-distribution-of-surveys-and-patient-education-materials/