ACR Meeting Abstracts

ACR Meeting Abstracts

  • Meeting Abstracts
    • All Meetings
    • ACR Convergence 2026
    • PRSYM 2026
    • ACR Convergence 2025
    • Download Abstract Supplements
  • Keyword Index
  • My Favorites
    • View & print my favorites
  • Search

Home » Meeting Abstracts » ACR Convergence 2023

Abstract Number: 1701

Treatment Regimens and Mortality in Systemic Sclerosis-associated Pulmonary Arterial Hypertension in Light of the 2022 ESC/ERS Guidelines

Hilde Jenssen Bjørkekjær1, Cosimo Bruni2, Cathrine Brunborg3, Patricia Carreira4, Paolo Airò5, Carmen Pilar Simeon-Aznar6, Marie-Elise Truchetet7, Alessandro Giollo8, Alexandra Balbir-Gurman9, Mickael Martin10, Christopher Denton11, Armando Gabrielli12, Havard Fretheim13, Imon Barua13, Helle Bitter14, Oyvind Midtvedt13, Torhild Garen15, Kaspar Broch16, Arne Andreassen17, Yoshiya Tanaka18, Gabriela Riemekasten19, Ulf Müller-Ladner20, marco Matucci Cerinic21, Iván Castellvi22, Elise Siegert23, Eric Hachulla24, Oliver Distler2 and Anna-Maria Hoffmann-Vold13, 1Department of Rheumatology, Hospital of Southern Norway, Kristiansand & University of Oslo, Institute of Clinical Medicine, Oslo, Norway, 2Department of Rheumatology, University Hospital Zurich, University of Zurich, Zurich, Switzerland, 3Oslo Centre for Biostatistics and Epidemiology, Research Support Services, Oslo University Hospital - Rikshospitalet, Oslo, Norway, 4Hospital Universitario 12 de Octubre, Madrid, Spain, 5Spedali Civili di Brescia, Scleroderma UNIT, UOC Reumatologia ed Immunologia Clinica, Piazzale Spedali Civili 1, 25123, Brescia, Italy, 6Department of Internal Medicine, Systemic Autoimmune Diseases Unit, Hospital Universitario Vall d'Hebronh, Barcelona, Spain, 7Bordeaux University Hospital, Bordeaux, France, 8University of Verona, Rheumatology Section, Department of Medicine, Verona, Italy, Verona, Italy, 9Rheumatology Institute, Rambam Health Care Campus and Rappaport Faculty of |Medicine, Technion, Haifa, Israel, 10Department of Internal Medicine, INSERM U1313, Poitiers University, Poitiers University Hospital, Poitiers, France, 11University College London, London, United Kingdom, 12Ospedali Riuniti Marche, Ancona, Italy, 13Oslo University Hospital, Oslo, Norway, 14Sorlandet sykehus, Kristiansand, Norway, 15Dept of Rheumatology, University Hospital Oslo, Oslo, Norway, 16Oslo University Hospital, Rikshospitalet, Department of Cardiology, Oslo, Norway, KG Jebsen center, Institute for Experimental Medical Research, University of Oslo, Oslo, Norway, 17Oslo University Hospital, Rikshospitalet, Department of Cardiology, Oslo, Norway, 18University of Occupational and Environmental Health, Kitakyushu, Japan, 19University Clinic Schleswit-Holstein (UKSH), Lübeck, Germany, 20Justus Liebig University Gießen, Campus Kerckhoff, Bad Nauheim, Germany, 21Unit of Immunology, Rheumatology, Allergy and Rare diseases, IRCCS San Raffaele Hospital, Milan, Milan, Italy, 22Hospital de Santa Creu i Sant Pau, Barcelona, Spain, 23Department of Rheumatology, Charité University Hospital, Charité Platz 1, D-10117, Berlin, Germany, 24University of Lille, Lille, France

Share on X (Twitter) Share on Facebook Share on LinkedIn Share on Email
Print

Meeting: ACR Convergence 2023

Keywords: Clinical practice guidelines, pulmonary, Systemic sclerosis

Session Information

Date: Monday, November 13, 2023

Title: Abstracts: Systemic Sclerosis & Related Disorders II: Clinical Research

Session Type: Abstract Session

Session Time: 4:00PM-5:30PM

Background/Purpose: The 2022 ESC/ERS Guidelines recommend upfront combination therapy for low- and intermediate-risk, and triple therapy for high-risk patients with systemic sclerosis (SSc)-associated pulmonary arterial hypertension (PAH).1 There is no treatment recommendation for patients with mean pulmonary arterial pressure (mPAP) 21-24 mmHg and pulmonary vascular resistance (PVR) 2-3 WU. We aimed to assess treatment regimens, risk stratification, and mortality according to mPAP and PVR thresholds.

Methods: We included SSc patients from the EUSTAR database who were diagnosed with PAH by right heart catheterization (RHC) between 2001-2021 (Project Number: CP122). PAH was defined as mPAP >20 mmHg, pulmonary artery wedge pressure ≤15 mmHg, and PVR >2 WU. We excluded patients with previous PAH-specific treatment and meaningful interstitial lung disease (ILD), defined as an extent of ILD >20% on HRCT or FVC < 70% in patients with missing quantification. We stratified patients into four risk groups based on WHO-functional class (FC), six-minute walk distance (6MWD), and NT-proBNP applying the COMPERA 2.0 risk stratification.2 Initial treatment regimens were defined as (1) upfront monotherapy with endothelin receptor antagonists, phosphodiesterase-5 inhibitors, or prostanoids; (2) upfront combination therapy; or (3) no therapy.

Survival was evaluated using Kaplan–Meier analysis and log-rank test. We assessed treatment regimens segregated by mPAP and PVR thresholds (lower thresholds: mPAP 21-24 mmHg and/or PVR 2-3 WU vs. higher thresholds: mPAP ≥25 mmHg and PVR ≥3 WU) and by risk stratification. We assessed the impact of initial treatment regimens on mortality using Cox regression adjusted for age, male sex, DLCO, mPAP and PVR thresholds, treatment-naïve status, and risk stratification.

Results: Of 890 patients who had RHC, 367 were eligible (table). Survival was significantly lower in the group with higher mPAP and PVR thresholds (p< 0.001) (table). The 5-year survival according to risk stratification for low-, intermediate-low, intermediate-high, and high risk was 85%, 86%, 60% and 25%, respectively.

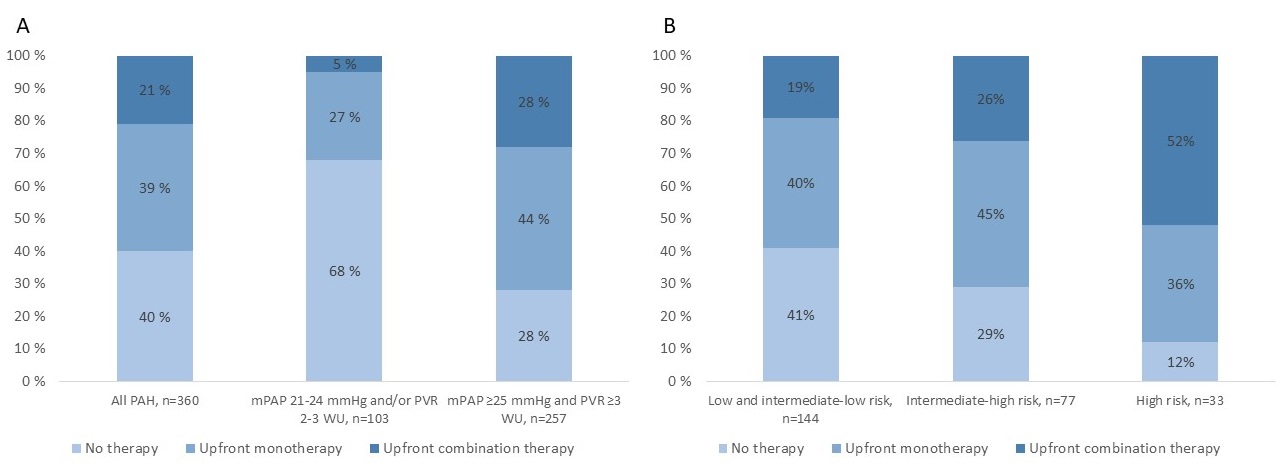
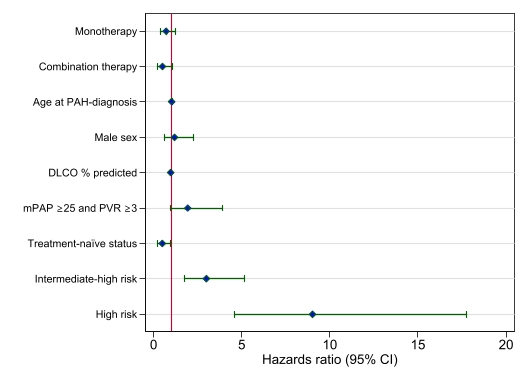
Upfront combination therapy was used more frequently in patients with mPAP ≥25 mmHg and PVR ≥3 WU (p< 0.001) and in patients in the high-risk group (p=0.002) (fig. 1 a-b). Despite at high risk and higher thresholds, 40% of these patients did not receive any treatment (fig. 1a). In multivariable Cox regression analysis, upfront combination therapy was numerically associated with reduced mortality compared with no treatment (HR 0.50, 95% CI (0.23 - 1.09), p=0.08) (fig. 2).

Conclusion: Our study shows that survival is impaired in SSc-PAH regardless mPAP and PVR thresholds, particularly in patients at intermediate-high and high risk. Current results show a trend toward reduced mortality for upfront combination therapy, and that many patients are not treated according to guideline recommendations. We suggest considering treatment in patients with lower mPAP and PVR thresholds and a more aggressive treatment approach in patients at intermediate-high risk to increase survival over time.

References:
1Humbert, Eur Heart J, 2022
2Hoeper, Eur Respir J, 2022

Supporting image 1

Table: Demographic and clinical characteristics by mPAP and PVR thresholds

Supporting image 2

Figure 1: Proportion of patients starting upfront monotherapy, upfront combination therapy or none segregated by (A) mPAP and PVR thresholds, and (B) risk stratification

Supporting image 3

Figure 2: Impact of upfront mono- or combination therapy on mortality compared with no treatment adjusted for other risk factors in multivariable Cox regression model


Disclosures: H. Jenssen Bjørkekjær: Janssen, 5; C. Bruni: AbbVie/Abbott, 5, Boehringer-Ingelheim, 2, 12, Travel Support, Eli Lilly, 6; C. Brunborg: None; P. Carreira: None; P. Airò: Boehringer-Ingelheim, 2, 5, 6, Bristol-Myers Squibb(BMS), 2, 5, 6, CSL Behring, 2, 5, 6, Janssen-Cilag, 2, 5, 6, Novartis, 2, 5, 6, Roche, 2, 5, 6; C. Simeon-Aznar: None; M. Truchetet: AbbVie/Abbott, 2, 6, Boehringer-Ingelheim, 2, 6, Gilead, 5, 6, Merck/MSD, 6, UCB, 6, 12, support for conferences; A. Giollo: Eli Lilly, 6, Galapagos, 2, 6, Novartis, 2, Sandoz, 2; A. Balbir-Gurman: None; M. Martin: Boehringer-Ingelheim, 6, GlaxoSmithKlein(GSK), 6; C. Denton: AbbVie, 2, Acceleron, 2, Arxx Therapeutics, 5, Bayer, 2, Boehringer-Ingelheim, 2, 6, Corbus, 2, 6, CSL Behring, 2, 5, GlaxoSmithKline, 2, 5, Horizon Therapeutics, 2, Inventiva, 2, 5, Janssen, 6, Roche, 2, Sanofi, 2, Servier, 5; A. Gabrielli: Boehringer-Ingelheim, 12, Educational Grants, Janssen, 12, Educational Grants, Roche, 12, Educational Grants; H. Fretheim: actelion, 5, bayer, 2, Boehringer-Ingelheim, 6, GlaxoSmithKlein(GSK), 5; I. Barua: None; H. Bitter: Boehringer-Ingelheim, 6; O. Midtvedt: None; T. Garen: None; K. Broch: Amgen, 2, 6, AstraZeneca, 2, 6, Boehringer-Ingelheim, 2, 6, Novartis, 2, 6, Orion Pharma, 2, 6, Pfizer, 2, 6, Pharmacosmos, 2, 6; A. Andreassen: Amgen, 2, 6, Janssen, 2, 6, Novartis, 2, 6, Orion Pharma, 2, 6, Pfizer, 2, 6; Y. Tanaka: AbbVie, 6, AstraZeneca, 6, BMS, 6, Boehringer-Ingelheim, 6, Chugai, 5, 6, Eisai, 5, 6, Eli Lilly, 6, Gilead, 6, GSK, 6, Mitsubishi-Tanabe, 5, Pfizer, 6, Taiho, 6, Taisho, 5, 6; G. Riemekasten: None; U. Müller-Ladner: None; m. Matucci Cerinic: accelerong, 2, 6, actelion, 2, 6, bayer, 2, 6, biogen, 2, 6, Boehringer-Ingelheim, 2, 6, Chemomab, 2, 6, corbus, 2, 6, CSL Behring, 2, 6, Eli Lilly, 2, 6, galapagos, 2, 6, Inventiva, 2, 6, Janssen, 2, 6, Merck/MSD, 2, 6, Mitsubishi, 2, 6, Pfizer, 2, 6, regeneron, 2, 6, Roche, 2, 6, samsung, 2, 6; I. Castellvi: None; E. Siegert: None; E. Hachulla: Bayer, 2, CSL Behring, 5, GlaxoSmithKlein(GSK), 2, 5, 6, johnson&Johnson, 2, 5, 6, Novartis, 2, 5, Otsuka, 6, Roche-Chugai, 2, 5, 6, sanofi-genzyme, 2, 5, Sobi, 5; O. Distler: 4P-Pharma, 2, 5, 6, AbbVie, 2, 5, 6, Acceleron, 2, 5, 6, Alcimed, 2, 5, 6, Altavant Sciences, 2, 5, 6, Amgen, 2, 5, 6, AnaMar, 2, 5, 6, Arxx, 2, 5, 6, AstraZeneca, 2, 5, 6, Bayer, 2, 5, 6, Blade Therapeutics, 2, 5, 6, Boehringer Ingelheim, 2, 5, 6, Citus AG, 12, Co-Founder, Corbus Pharmaceuticals, 2, 5, 6, CSL Behring, 2, 5, 6, Galapagos, 2, 5, 6, Galderma, 2, 5, 6, Glenmark, 2, 5, 6, Gossamer, 2, 5, 6, Horizon Therapeutics, 2, 5, 6, Janssen, 2, 5, 6, Kymera, 2, 5, 6, Lupin, 2, 5, 6, Medscape, 2, 5, 6, Miltenyi Biotec, 2, 5, 6, Mitsubishi Tanabe, 2, 5, 6, MSD, 2, 5, 6, Novartis, 2, 5, 6, Patent issued “mir-29 for the treatment of systemic sclerosis” (US8247389, EP2331143), 10, Prometheus Biosciences, 2, 5, 6, Redx Pharma, 2, 5, 6, Roivant, 2, 5, 6, Topadur, 2, 5, 6; A. Hoffmann-Vold: Arxx Therapeutics, 2, Boehringer-Ingelheim, 2, 5, 6, 12, Support for travel, Genentech, 2, Janssen, 2, 5, 6, Medscape, 2, 6, 12, Support for travel, Roche, 2, 6, 12, Support for travel.

To cite this abstract in AMA style:

Jenssen Bjørkekjær H, Bruni C, Brunborg C, Carreira P, Airò P, Simeon-Aznar C, Truchetet M, Giollo A, Balbir-Gurman A, Martin M, Denton C, Gabrielli A, Fretheim H, Barua I, Bitter H, Midtvedt O, Garen T, Broch K, Andreassen A, Tanaka Y, Riemekasten G, Müller-Ladner U, Matucci Cerinic m, Castellvi I, Siegert E, Hachulla E, Distler O, Hoffmann-Vold A. Treatment Regimens and Mortality in Systemic Sclerosis-associated Pulmonary Arterial Hypertension in Light of the 2022 ESC/ERS Guidelines [abstract]. Arthritis Rheumatol. 2023; 75 (suppl 9). https://acrabstracts.org/abstract/treatment-regimens-and-mortality-in-systemic-sclerosis-associated-pulmonary-arterial-hypertension-in-light-of-the-2022-esc-ers-guidelines/. Accessed .

ACR Meeting Abstracts - https://acrabstracts.org/abstract/treatment-regimens-and-mortality-in-systemic-sclerosis-associated-pulmonary-arterial-hypertension-in-light-of-the-2022-esc-ers-guidelines/

My Favorites

Save and print abstracts during your browser session by clicking the “Favorite” button at the bottom of any abstract (must have cookies enabled in browser). See saved favorites.

Abstract Policies

  • ACR Convergence Abstract Embargo Policies
  • ACR Convergence Abstract Permissions & Reprints
  • PRSYM Abstract Policies

ACR Convergence. Where Rheumatology Meets

ACR Convergence 2026

Join us November 6-11 in Orlando, Florida.
See Registration Information

  • Contact ACR
  • Privacy Policy
  • ACR Policies
  • Cookie Preferences

© Copyright 2026 American College of Rheumatology