
Session Information
Date: Monday, November 9, 2020
Title: RA – Treatments IV: New Therapies & Strategies (2008–2012)
Session Type: Abstract Session
Session Time: 5:00PM-5:50PM
Background/Purpose: The EULAR recommendations, updated in 20161 and 20192, propose the initiation of glucocorticoid (GC) therapy in combination with cDMARDs background therapy for every patient with early rheumatoid arthritis (ERA).
The aim of this study is to evaluate the proportion of patients with ERA who have been treated with GC in daily practice, to analyse the baseline characteristics of these patients, and to assess the clinical benefit and side effects of GC during 5 years of follow-up.
Methods: We included patients with ERA from the UCLouvain Brussels cohort who met the ACR/EULAR 2010 classification criteria and were naïve to cDMARDs. Treatments were initiated based on the decision of a senior rheumatologist. We retrospectively collected patient characteristics prior to the introduction of cDMARDs with or without GC. Efficiency and serious adverse events were analysed at 6 months, 1 year, 3 years and 5 years.
Results: Data from 474 eligible ERA patients were collected. The average age of the population is 48.9 years. 70.5% of the patients are women. 27.3% are smokers and 68.8% are positive for anti-citrullinated protein antibody (ACPA).
178 patients (37.7 %) initiated GC compared to 294 patients (62.3%) who received only NSAIDs and/or analgesics in combination with cDMARDs.
At baseline, the elevation of CRP is the main factor that favors the initiation of GC (CRP 2.9 vs 2.0 mg/dl, p = 0.015) followed by smoking habits (34.2% vs 23.3%, p = 0.018), the absence of ACPA (37.2% vs 27.6%, p = 0.037), the prescription of methotrexate as a monotherapy (70.6% vs 50.5%, p < 0.001), and the age (50.6 vs 48.0, p = 0.050). Other parameters such as swollen joint count, tender joint count, DAS28-CRP, HAQ or baseline erosion were similar between groups.
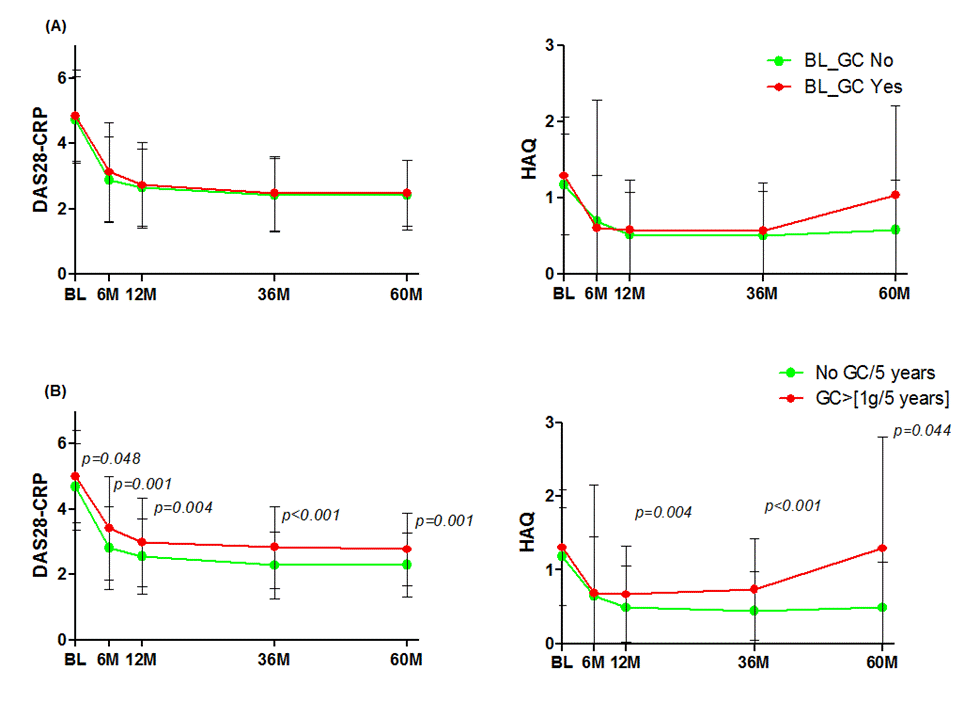
5 years follow-up of DAS28-CRP, HAQ or VAS pain values did not differ between the two groups (Fig1A).
Interestingly, patients not exposed at baseline to GC showed a higher remission rate (DAS28-CRP< 2.6) of 48.4% vs 44.3% at 6 months.
We also analysed a subgroup of patients (n=139) who received a cumulative dose of more than 1 g of prednisolone during the 5 years period. We confirmed the baseline differences for CRP, smoking habits, age and found in this subgroup more males (36.7% vs 28.2%, p=0.021) and higher DAS-28CRP values (5.0 vs 4.7, p=0.048). During the 5 years follow up, DAS-28CRP, VAS pain and HAQ remained significantly higher leading to a higher number of bioDMARDs prescribed in this group (Fig1B). More severe infections were reported in this subgroup (11.5% vs 4.2%). Bone densitometry values, number of fractures, and cardiovascular profiles were similar between groups.
Conclusion: In our ERA cohort, initiation of GC treatment does not add additional benefit for the short and long-term control of the disease.
GC were more prescribed in seronegative RA patients with higher level of inflammation and we confirm that patients exposed to higher cumulative doses of GC are at higher risk to develop severe infections.
Further studies are needed to support that GC induction therapy should not be offered to all ERA patients.
To cite this abstract in AMA style:
Sapart E, Sokolova T, de Montjoye S, Dierckx S, Nzeusseu Toukap A, Avramovska A, Durez P. Should We Use Glucocorticoid in Early Rheumatoid Arthritis? : Results at 5 Years from the ERA Louvain Brussels Cohort [abstract]. Arthritis Rheumatol. 2020; 72 (suppl 10). https://acrabstracts.org/abstract/should-we-use-glucocorticoid-in-early-rheumatoid-arthritis-results-at-5-years-from-the-era-louvain-brussels-cohort/. Accessed .ACR Meeting Abstracts - https://acrabstracts.org/abstract/should-we-use-glucocorticoid-in-early-rheumatoid-arthritis-results-at-5-years-from-the-era-louvain-brussels-cohort/