
Session Information
Session Type: Abstract Submissions (ACR)
Background/Purpose:
Glucocorticoids are the cornerstone of therapy in patients with polymyositis (PM) and dermatomyositis (DM). However, side effects are common. Furthermore, glucocorticoids exhibits an potential inhibitory effects on skeletal muscle regeneration. Therefore disease-modifying antirheumatic drugs (DMARDs) are used as glucocorticoids sparing agents. To date limited studies are available in which the glucocorticoids sparing effects of DMARDs are evaluated. The aim of this study is to analyze whether an early start of DMARDs in patients with PM or DM leads to the opportunity to taper dosage of glucocorticoids early.
Methods:
All available patients with PM and DM of the Nijmegen Myositis inception cohort which was started in 2009 were included. The data available of this cohort consist of clinical features at diagnosis combined with follow up information on treatment and complications. All patient fulfilled the Bohan and Peter diagnostic criteria.
Early start of DMARD was defined as start of methotrexate, azathioprine, hydrochloroquine, mycophenolate, tacrolimus or sulfasalazine within 3 months after diagnosis. Dosage of less than 15 mg of prednisone was regarded as clinical relevant tapering. Two subgroups (early DMARD and non-early DMARD) were compared to analyze for time to reach the dosage of 15 mg prednisone with a follow-up of 1 year using a multivariate cox proportional hazards model.
Results:
In the early DMARD starters group 36 patients were included and 25 patients as non-early DMARD starters. The mean age in early DMARD starters was 46 (SD 17) and 37 years (SD 17) in the non-early DMARD starters group. Clinical features and serology revealed no significant differences (Table 1).
Table 1. Study population characteristics
|
Characteristics |
Early DMARD starters
(n =36) |
Non-early DMARD starters
(n =25) |
Significance (p-value) |
|
Age, mean±SD (years) |
46 ± 17 |
38 ± 17 |
NS |
|
Gender (male/female) |
15/21 |
7/18 |
NS |
|
Type of myositis (PM/DM) |
23/13 |
15/10 |
NS |
|
Serum CK at diagnosis, median (Units/liter) |
2467 (386-7370) |
1523 (400-7275) |
NS |
|
ANA |
21/32 (66%) |
19/24 (79.2%) |
NS |
|
Anti-SSA |
10/33 (30%) |
8/24 (33%) |
NS |
|
Anti-SSB |
1/33 (3%) |
1/24 (4%) |
NS |
|
Anti-Jo1 |
9/33 (27%) |
9/24 (38%) |
NS |
|
Interstitial lung disease* |
8/36 (22%) |
4/25 (16%) |
NS |
*Interstitial lung disease, defined as fibrosis on HRCT-scan or < 70 % vital capacity
on pulmonary function within 1 year after diagnosis; NS: not significant
In a Cox regression analysis, early start of DMARD therapy was found to be an independent predictor of tapering dosage of prednisone to less than 15mg (hazard ratio, 2.3; 95% CI, 1.1-4.8; p = 0.03) (fig.1).
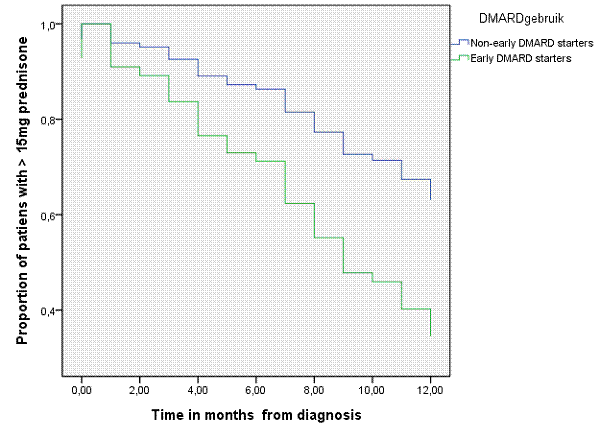
Figure 1: Survival curve of early and non-early DMARD starters for time to reach < 15 mg of prednisone use.
Conclusion:
Simultaneous start of DMARD therapy with glucocorticoids leads to the opportunity to taper glucocorticoids to clinical significant lower dosages within 1 year after diagnosis in patients with PM and DM compared to adding DMARDs later or glucocorticoids alone in the course of the disease.
Disclosure:
K. J. Bhansing,
None;
P. L. Van Riel,
None;
S. Pillen,
None;
B. G. M. van Engelen,
None;
M. C. Vonk,
Actelion, Pfizer, GSK, United Therapeutics,
2,
Actelion, Pfizer, GSK, United Therapeutics,
5,
Actelion, Pfizer, GSK, United Therapeutics,
8.
ACR Meeting Abstracts - https://acrabstracts.org/abstract/simultaneous-initiating-of-glucocorticoids-and-disease-modifying-antirheumatic-drug-therapy-in-polymyositis-and-dermatomyositis-patients-results-in-the-opportunity-to-taper-dosage-of-glucocortico/