
Session Information
Date: Sunday, October 26, 2025
Session Type: Poster Session A
Session Time: 10:30AM-12:30PM
Background/Purpose: Comorbid depression is common in patients with autoimmune diseases and is associated with increased healthcare utilization and death. Despite American College of Rheumatology recommendations for annual depression screening, it is often lacking in rheumatology practices, particularly in safety-net settings. We aimed to implement workflows for depression screening with appropriate mental health follow-up referrals in an urban, safety-net rheumatology clinic using the Institute for Healthcare Improvement’s Model for Improvement.
Methods: This was a quality improvement project conducted by an interprofessional team of medical students, nurses, medical assistants (MAs), and a rheumatologist. Data were collected from workflow observations, stakeholder interviews, and Patient Health Questionnaire-9 (PHQ-9) forms, a validated tool to screen for depressive symptoms in multiple languages used by primary care at our institution. Patients literate in English, Spanish, or Chinese presenting to rheumatology clinics were eligible for screening, unless screened within the past 12 months. A standardized protocol for PHQ-9 collection, documentation, and follow-up was developed. PHQ-9 scores were documented in the electronic medical record (EMR) and a retrospective chart review was conducted to assess accuracy and completeness of documentation. Language concordant educational materials were created for patients who scored >4 on the PHQ-9. Referrals to behavioral health and primary care notification were made for scores ≥10; patients endorsing suicidal ideation were assessed for immediate safety needs and brought to psychiatric emergency services if needed. Implementation occurred over three plan-do-study-act (PDSA) cycles: first by students, then by MAs with student observation, and finally by MAs independently.
Results: We identified 117 patients eligible for screening. One patient declined screening and was excluded. Of the remaining 116 patients, 109 (94%) were screened for depressive symptoms and 48 (44%) screened positive (PHQ-9 >4), with 24 (22%) having PHQ-9 scores ≥ 10 that corresponded to moderate or severe symptoms (Fig. 1). Ten patients endorsed passive suicidal ideation and received timely safety assessments. All patients who screened positive were offered appropriate follow-up based on their PHQ-9 scores. Screening rates varied across PDSA cycles: 100% in the first, 82% in the second, and 94% in the third cycle. Correct documentation in the EMR went from 29% to 96% to 84% across the three cycles (Fig. 2). In qualitative follow-up interviews, clinic staff reported high acceptability of the new workflow and confidence in managing depression screening.
Conclusion: Screening for depressive symptoms in patients with rheumatic diseases and providing appropriate mental health follow-up in rheumatology clinics at a safety-net hospital is feasible. Although managing positive screens required staff training and interdepartmental coordination, clear protocols allowed for smooth implementation. Iterative workflow improvements can enable screening rates to remain high and improve documentation.
 Figure 1. Severity of Depressive Symptoms Among 109 Patients Screened with PHQ-9
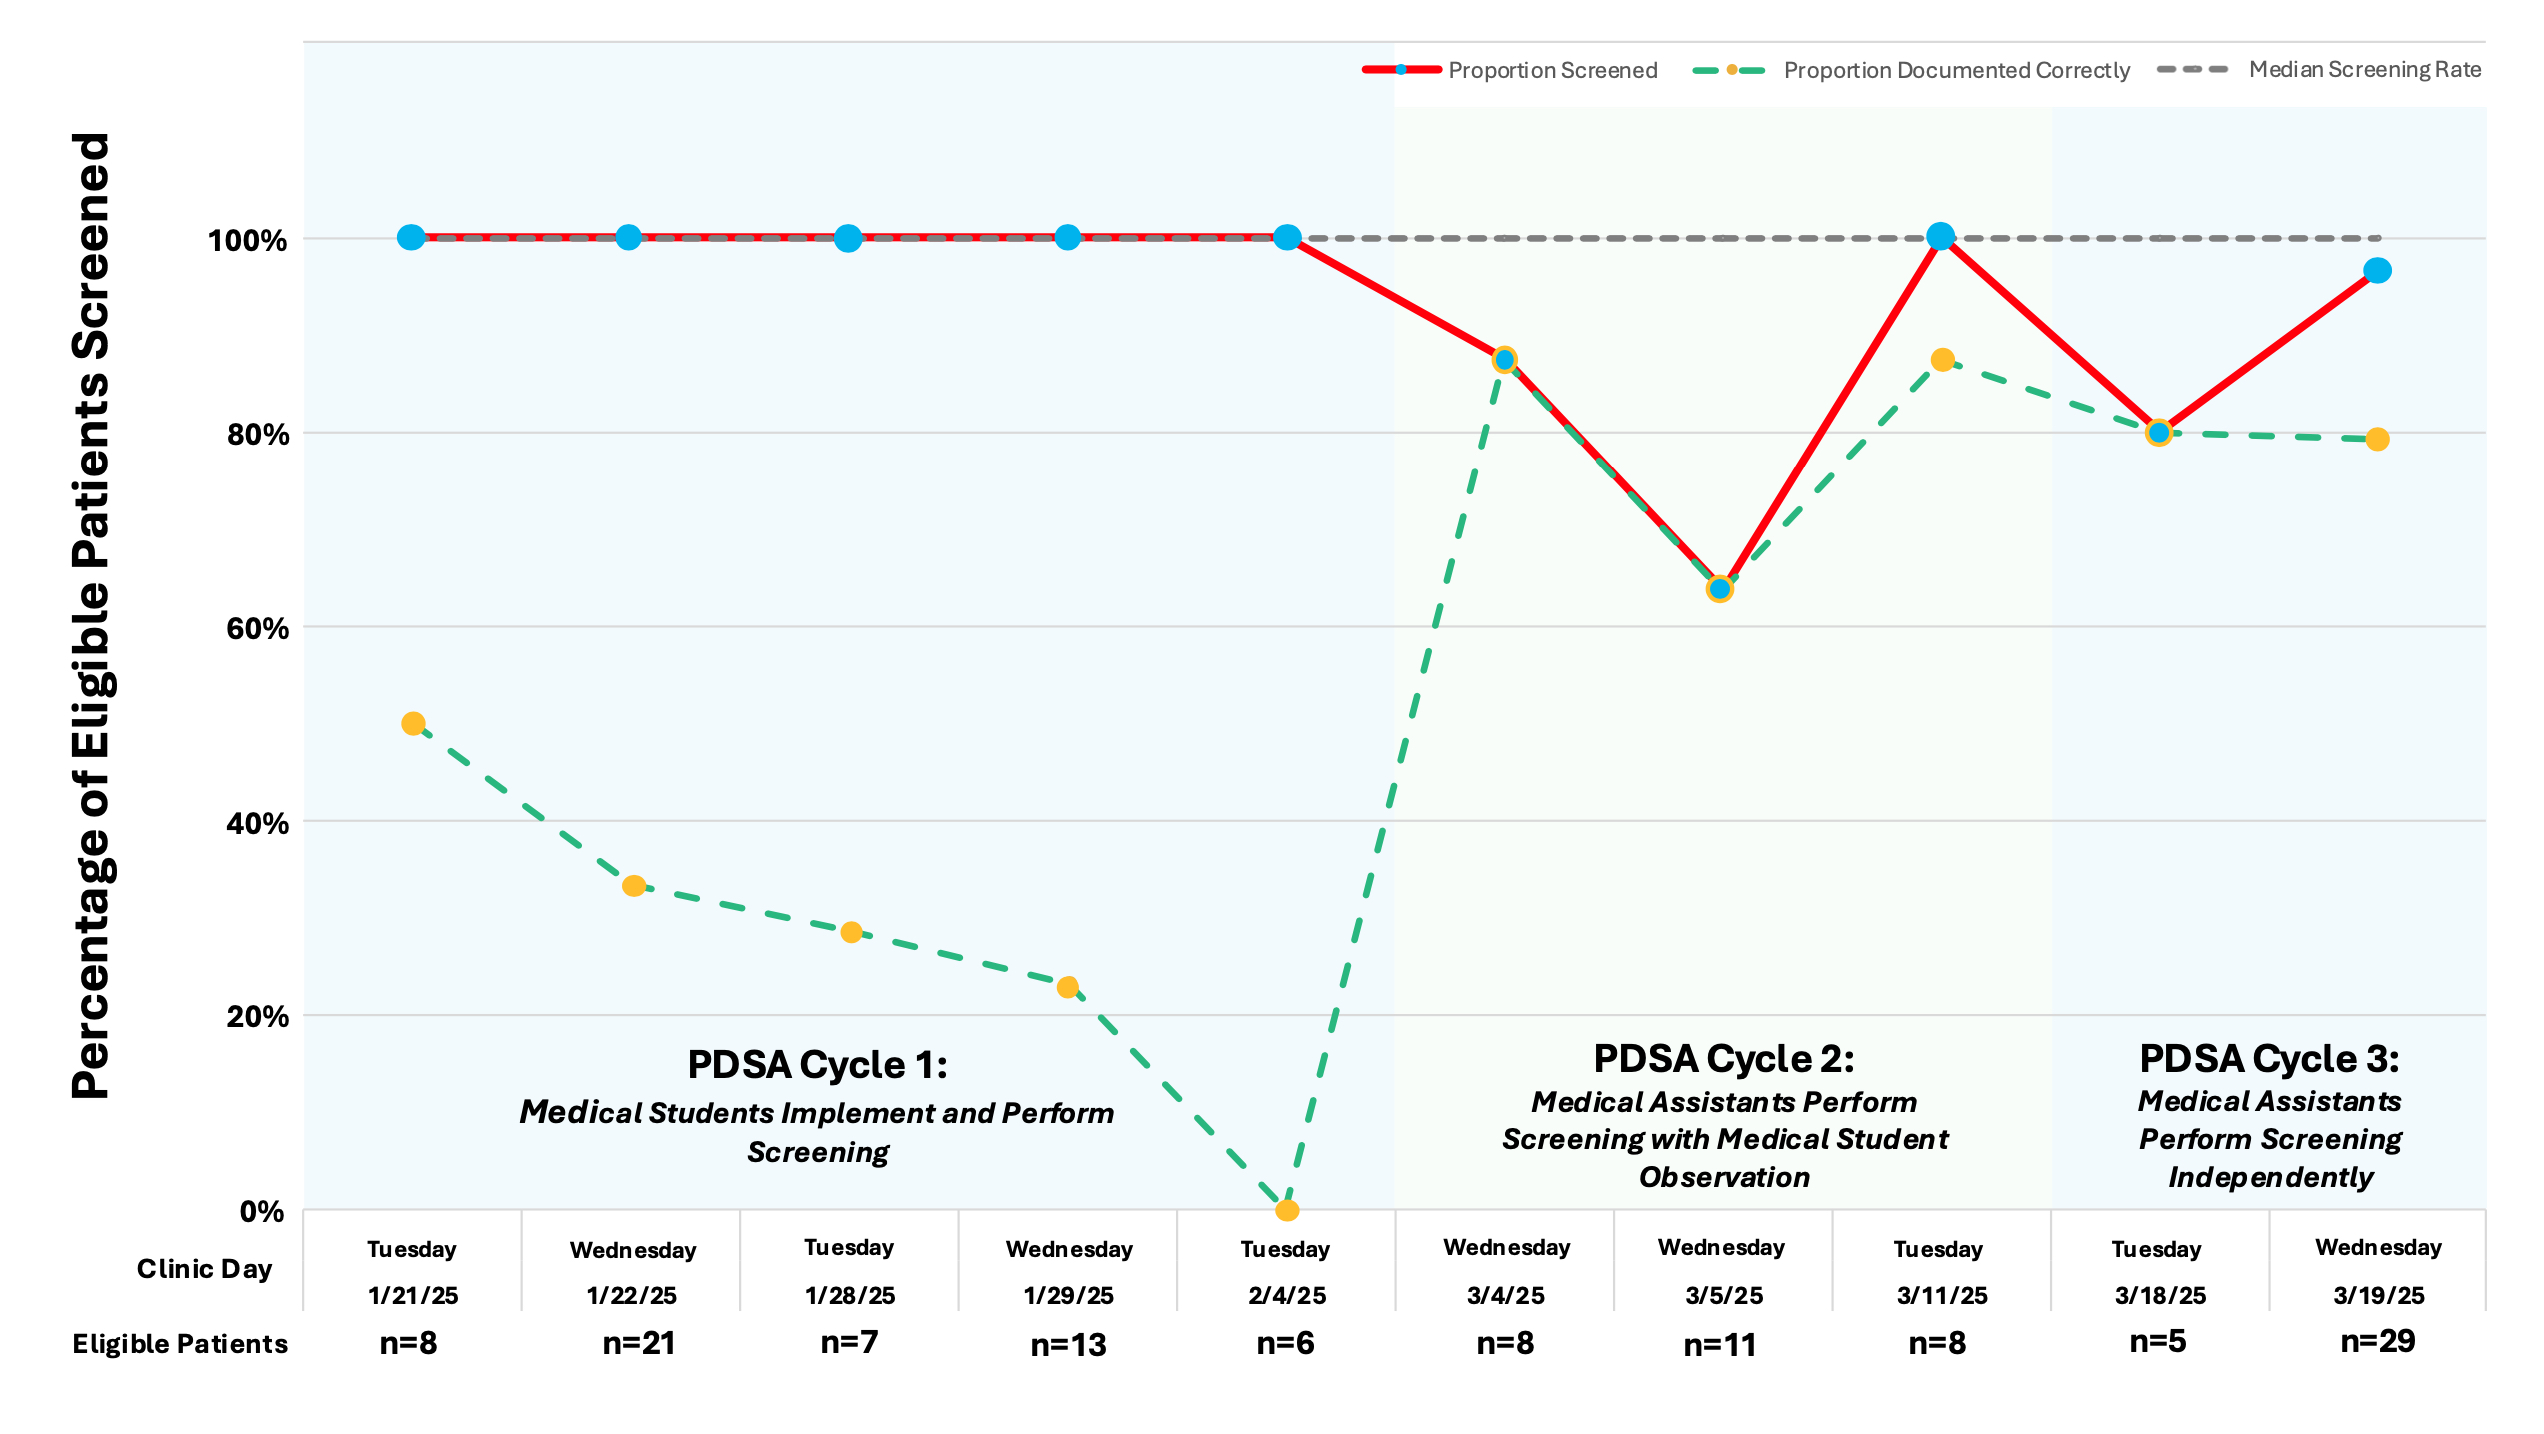 Figure 2. Rates of PHQ-9 Screening and Documentation After Workflow Implementation in a Safety-net Rheumatology Clinic Across Three PDSA Cycles (Jan – Mar 2025)
To cite this abstract in AMA style:
Grossman C, Chhabra J, Gonzalez Sanchez X, Brito K, Friskey J, Abel B, Margaretten M. A Joint Effort: Implementing Depression Screening in a Safety-Net Rheumatology Clinic [abstract]. Arthritis Rheumatol. 2025; 77 (suppl 9). https://acrabstracts.org/abstract/a-joint-effort-implementing-depression-screening-in-a-safety-net-rheumatology-clinic/. Accessed .ACR Meeting Abstracts - https://acrabstracts.org/abstract/a-joint-effort-implementing-depression-screening-in-a-safety-net-rheumatology-clinic/