ACR Meeting Abstracts

ACR Meeting Abstracts

  • Meeting Abstracts
    • All Meetings
    • PRSYM 2026
    • ACR Convergence 2025
    • Download Abstract Supplements
  • Keyword Index
  • My Favorites
    • View & print my favorites
  • Search

Home » Meeting Abstracts » ACR/ARHP Annual Meeting 2016

Abstract Number: 3031

Rethinking Primary Sjögren’s Syndrome: Stratification By Clinical Phenotypes to Improve Understanding of Disease Pathogenesis, Trial Design, Clinical Management and Prospective Health Gains?

Dennis Lendrem1, Nadia Howard Tripp2,3, Xavier Mariette4, Svein Joar A. Johnsen5, Jessica Tarn6, Katie Hackett6, Bridget Griffiths7, Sheryl Mitchell8, Alain Saraux9, Valerie Devauchelle10, Katrine Norheim11, John D. Isaacs12, Peter McMeekin13,14, Simon Bowman15, Roald Omdal16, Jacques-Eric Gottenberg17 and Wan-Fai Ng18, 1Newcastle upon Tyne, Newcastle University, Newcastle upon Tyne, United Kingdom, 2Institute of Cellular Medicine, Newcastle University, Newcastle-upon-Tyne, United Kingdom, 3Newcastle-upon-Tyne Hospitals NHS Foundation Trust, Newcastle-upon-Tyne, United Kingdom, 4Université Paris-Sud, AP-HP, Hôpitaux Universitaires Paris-Sud, Paris, France, 5Clinical Immunology Unit, Department of Internal Medicine, Stavanger University Hospital, Stavanger, Norway, 6Newcastle University, Newcastle-upon-Tyne, United Kingdom, 7Rheumatology, Freeman Hospital, Newcastle Upon Tyne, United Kingdom, 8Freeman Hospital, Newcastle upon Tyne, United Kingdom, 9Rheumatology Department, CHU de la Cavale Blanche, Brest Cedex, France, 10Service de Rhumatologie, Department of Rheumatology, Brest University Hospital, Brest, France, Brest, France, 11Stavanger University Hospital, Stavanger, Norway, 12Newcastle University and the Freeman Hospital, Newcastle-upon-Tyne, United Kingdom, 13Institute of Health and Society, Newcastle University, Newcastle-upon-Tyne, United Kingdom, 14Northumbria University, Newcastle-upon-Tyne, United Kingdom, 15Department of Rheumatology, University Hospitals Birmingham NHS Foundation Trust, Birmingham, United Kingdom, 16University of Bergen, Bergen, Norway, 17Department of Rheumatology, Strasbourg University Hospital, Strasbourg, France, 18Institute of Cellular Medicine, Newcastle University, Newcastle upon Tyne, United Kingdom

Share on X (Twitter) Share on Facebook Share on LinkedIn Share on Email
Print

Meeting: ACR/ARHP Annual Meeting 2016

Date of first publication: September 28, 2016

Keywords: Disease Activity, patient outcomes and phenotypes, Sjogren's syndrome

Session Information

Date: Tuesday, November 15, 2016

Title: Sjögren's Syndrome I: Clinical Insights

Session Type: ACR Concurrent Abstract Session

Session Time: 2:30PM-4:00PM

Background/Purpose: Primary SjšgrenÕs Syndrome (pSS) is a chronic autoimmune rheumatic disease causing a wide-range of symptoms including dryness, pain and fatigue. Individual patient experiences of pSS vary resulting in a heterogeneous patient population.  We use patient reported symptoms to identify distinct clinical pSS phenotypes and use these to explore underlying biological differences.

Methods: We used Patient Reported Outcome Measures (PROMs) to clinically phenotype 594 patients on the United Kingdom Primary SjšgrenÕs Syndrome Registry. Phenotype patterns were identified using hierarchical cluster analysis of patient reported rating scales for pain, fatigue, dryness, anxiety and depression. Non-parametric analysis of variance was used to evaluate biological differences between these clusters. We then used the same PROMs to phenotype 463 pSS patients from Norwegian and French cohorts, in order to validate these four phenotypes independently.

Results: We identified four phenotypic clusters, which we refer to as Low Symptom Burden (LSB), High Symptom Burden (HSB), Dryness Dominant (DD) and Low Anxiety and Depression (LAD) – with marked differences in health status and quality of life (TTO p <0á0001, EQ-5D VAS p <0á0001). Furthermore, there were significant differences on clinical measures of disease activity (ESSDAI p=0á039), and objective dryness measures (salivary flow p=0á007, SchirmerÕs p=0á014).  In addition, there were marked differences in biological parameters (IgG p<0á0001, lymphocytes p=0á0005, ESR p=0á003, IL-17 p=0á0174 and TNFα p=0á0133) between clusters, suggesting possible distinct underlying endotypes. Significant biological and clinical differences in IgG, Lymphocytes, ESR, ESSDAI, and Salivary Flow remained across the four phenotypes in our validation cohorts.

Conclusion: We have identified and independently validated four distinct pSS clinical phenotypes with associated biological differences.  There are marked differences in the potential health gains for these four clusters with important implications for clinical management, trial design and therapeutic development for pSS.
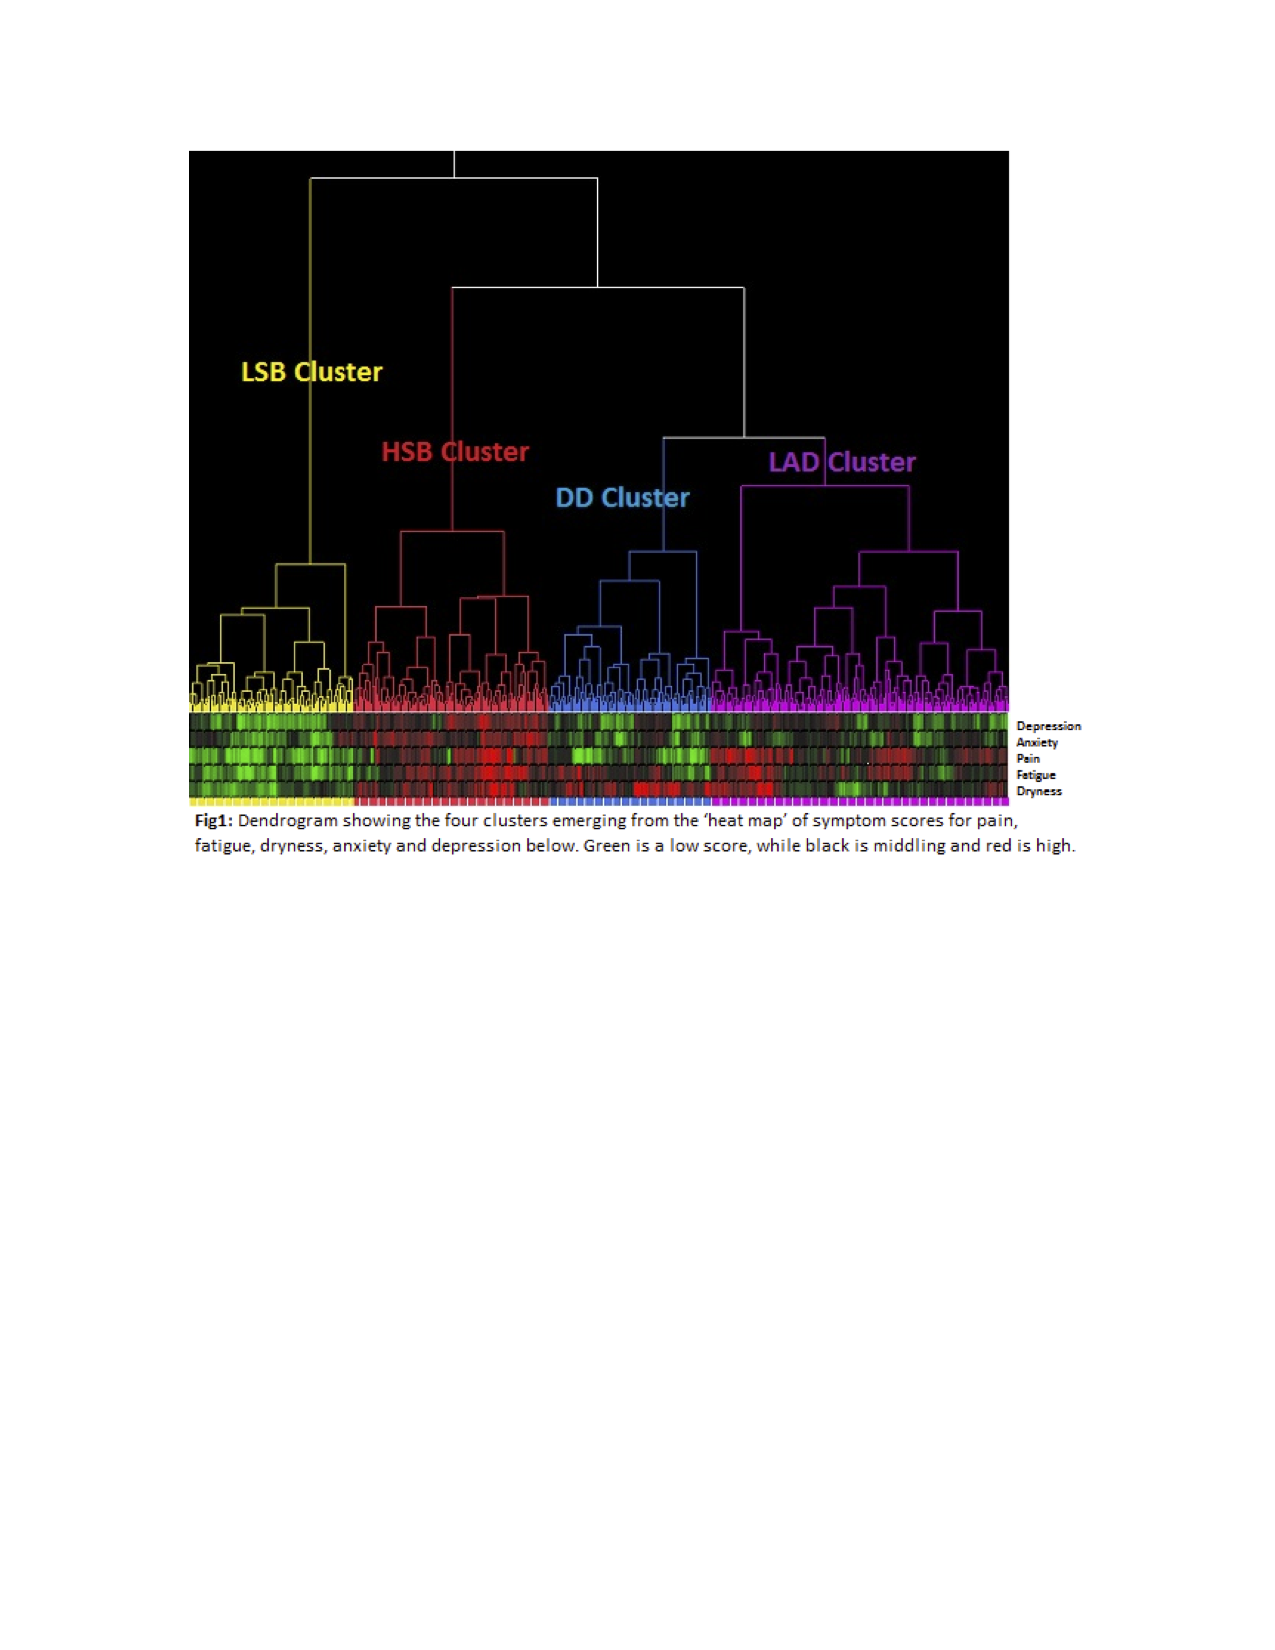
Table 1: Clinical and biological differences across phenotypes. Median values in bold, 25th and 75th centile below, with UKPSSR cohort in white and the two validation cohorts shaded in grey.

Parameter Cohort LSB HSB DD LAD P-value
Lymphocytes (x 109 /L) UK 1.20 1.00, 1.60 1.50 1.20, 1.80 1.27 0.95, 1.72 1.32 1.04, 1.70 0.0005
Lymphocytes (x 109 /L) Stavanger 1.35 0.73, 1.73 1.9 1.6, 2.35 1.2 0.85, 1.4 1.8 1.3, 2 0.0330
Lymphocytes (x 109 /L) French 1.32 1.0, 1.8 1.48 1.1, 1.7 1.18 1.0, 1.6 1.5 1.1, 1.8 0.0251
Lymphocytes (x 109 /L) Combined 1.25 1, 1.62 1.5 1.2, 1.77 1.2 0.95, 1.67 1.4 1.08, 1.8 <0.0001
IgG (mg/dL) UK 17.97 14.51, 22.94 14.10 11.05, 18.20 16.63 13.00, 20.85 14.35 11.03, 19.48 <0.0001
IgG (mg/dL) Stavanger 13.95 10.7, 16 11.1 9.3, 11.9 14.9 12.4, 18 11.7 10, 13.1 0.0054
IgG (mg/dL) French 15 12.3, 18.7 12.8 10.7, 16.7 15.2 11.1, 20.6 12.45 9.8, 16.1 0.0028
IgG (mg/dL) Combined 16.6 13.2, 21.5 13.4 10.7, 17 12.5 16.0, 20.3 13.2 10.3, 17.9 <0.0001
Salivary Flow (ml/15 mins) UK 0.40 0.00, 1.05 0.20 0.00, 1.00 0.05 0.00, 0.75 0.30 0.00, 1.20 0.0097
Salivary Flow (ml/15 mins) Stavanger 1.65 0.4, 2.2 0.8 0.1, 2.5 0.2 0, 0.68 0.9 0, 1.7 0.1212
Salivary Flow (ml/15 mins) French 0.24 0.1, 1.71 0.4 0.1, 2.23 0.02 0.00, 0.2 0.22 0.08, 1.5 <0.0001
Salivary Flow (ml/15 mins) Combined 0.3 0.06, 1.45 0.25 0, 1.3 0.05 0, 0 0.3 0.04, 1.4 <0.0001
SchirmerÕs I test (mm/5 mins) UK 3.00 0.00, 6.75 3.00 0.50, 10.50 2.00 0.00, 6.50 4.00 1.00, 10.50 0.0136
SchirmerÕs I test (mm/5 mins) Stavanger 7 2.5, 13.6 6.75 2.8, 23.1 1.5 0, 4.5 5.5 2.5, 14.5 0.0204
SchirmerÕs I test (mm/5 mins) French 5 2, 15 5.75 2.13, 14.38 7 0, 13 7.5 3.5, 15 0.2644
SchirmerÕs I test (mm/5 mins) Combined 3.9 0.5, 9 5 1, 12.5 2.3 0, 7.1 5 2, 12.5 <0.0001
ESSDAI UK 2.00 1.00, 6.00 4.00 1.00, 8.00 4.00 1.00, 7.00 4.00 2.00, 8.00 0.0193
ESSDAI Stavanger 2.5 0.75, 5.75 5 0.5, 12.5 5.5 1.5, 8 5 0.75, 10.5 0.8333
CRP (mg/L) UK 4.00 2.40, 5.00 5.00 3.00, 5.00 5.00 3.00, 5.00 5.00 2.00, 5.00 0.0327
CRP (mg/L) Stavanger 2.15 1.45, 4.6 3 1, 3.05 1.4 1, 2.6 1.2 1, 2.3 0.3522
ESR (mm/hr) UK 24.00 13.50, 42.50 20.00 10.00, 39.00 23.50 12.00, 43.00 17.00 8.00, 32.00 0.0064
ESR (mm/hr) Stavanger 10 4.5 3 2.5, 9.5 8.5 5, 21.5 7 4, 16 0.3286
IL-17 UK 42.2 0, 203 0 0, 21 2.8 0, 68 8.5 0, 73 0.0174
TNF-α UK 29 1, 88 0 0, 11 3.4 0, 26 7 0, 29 0.0133
EQ-5D (VAS) UK 80.00 70.00, 89.50 43.00 30.00, 60.00 67.00 50.00, 79.00 60.00 50.00, 70.00 ²0.0001
EQ-5D TTO UK 0.80 0.76, 1.00 0.52 -0.02, 0.69 0.80 0.69, 0.85 0.69 0.59, 0.76 ²0.0001


Disclosure: D. Lendrem, None; N. Howard Tripp, None; X. Mariette, None; S. J. A. Johnsen, None; J. Tarn, None; K. Hackett, None; B. Griffiths, None; S. Mitchell, None; A. Saraux, None; V. Devauchelle, None; K. Norheim, None; J. D. Isaacs, None; P. McMeekin, None; S. Bowman, None; R. Omdal, None; J. E. Gottenberg, None; W. F. Ng, None.

To cite this abstract in AMA style:

Lendrem D, Howard Tripp N, Mariette X, Johnsen SJA, Tarn J, Hackett K, Griffiths B, Mitchell S, Saraux A, Devauchelle V, Norheim K, Isaacs JD, McMeekin P, Bowman S, Omdal R, Gottenberg JE, Ng WF. Rethinking Primary Sjögren’s Syndrome: Stratification By Clinical Phenotypes to Improve Understanding of Disease Pathogenesis, Trial Design, Clinical Management and Prospective Health Gains? [abstract]. Arthritis Rheumatol. 2016; 68 (suppl 10). https://acrabstracts.org/abstract/rethinking-primary-sjogrens-syndrome-stratification-by-clinical-phenotypes-to-improve-understanding-of-disease-pathogenesis-trial-design-clinical-management-and-prospective-health-gains/. Accessed .

ACR Meeting Abstracts - https://acrabstracts.org/abstract/rethinking-primary-sjogrens-syndrome-stratification-by-clinical-phenotypes-to-improve-understanding-of-disease-pathogenesis-trial-design-clinical-management-and-prospective-health-gains/

My Favorites

Save and print abstracts during your browser session by clicking the “Favorite” button at the bottom of any abstract (must have cookies enabled in browser). See saved favorites.

Abstract Policies

  • ACR Convergence Abstract Embargo Policies
  • ACR Convergence Abstract Permissions & Reprints
  • PRSYM Abstract Policies

ACR Convergence. Where Rheumatology Meets

ACR Convergence 2026

Join us November 6-11 in Orlando, Florida.
See Registration Information

  • Contact ACR
  • Privacy Policy
  • ACR Policies
  • Cookie Preferences

© Copyright 2026 American College of Rheumatology