
Session Information
Date: Tuesday, November 15, 2016
Session Type: ACR Poster Session C
Session Time: 9:00AM-11:00AM
Background/Purpose: The goal of this study was to validate a claims-based statistical model to predict disease activity measured by the 28-joint count Disease Activity Score (DAS28) in a population of Veteran patients enrolled in the VARA registry.
Methods: VARA enrolled Veterans were included in the study if they had a healthcare encounter during the 365-days prior to their DAS28 score and were without diagnoses of cancer, organ transplantation, or other autoimmune diseases. Models using claims data were developed to predict the first DAS28 fulfilling these criteria. Three models were developed based on initial selection of variables for analyses. All variables included in the model were required to have a prevalence in the population ³1%. The 1st model started with 253 variables believed to be associated with disease activity (all clinical predictors). The 2nd model leveraged hierarchical classification systems for pharmacy, procedure and diagnostic codes along with the clinically derived variables for high-dimensional variable selection of 1,275 possible predictors (all predictors). The 3rd approach pre-screened all predictors with a significant bivariate association with the DAS28 resulting in 279 predictors (pre-screening). Models were also compared for patients with <5 years of RA disease to those ³5 years of RA disease. The least absolute shrinkage and selection operator (LASSO) with 5-fold cross-validation was used for variable selection and model development. The classification accuracy was examined for 4 disease activity categories: remission (<2.6), low (2.6-3.1), moderate (3.2-5.1) and high (>5.1) activity.
Results: There were 1,582 Veterans who fulfilled inclusion criteria. The adjusted r-square for the 3 models tested ranged from 0.221-0.223 (Table 1). The number of predictors in the final models were 32 for the clinical predictors, 45 for all predictors and 46 among pre-screened. The adjusted r-square for models based on patients with <5 years (n=429) of RA disease were slightly better than for patients with ³5 years (n=1056) of RA disease. Correct Classification ranged from 40% to 41% for the three models.
Conclusion: The multiple models tested found many predictors with significant unique correlation with the DAS28. Nevertheless, the overall model performance revealed similar results and showed relatively weak overall predictive accuracy in measuring disease activity when using DAS28 as the dependent variables. The models performed poorly at predicting patients with remission and high disease activity making the overall correct classification rate <50% for all models. Duration of disease did not have a large impact on model performance. Future research should investigate additional strategies to collect disease activity measures directly from medical records and allow inclusion of additional laboratory and other clinical data. 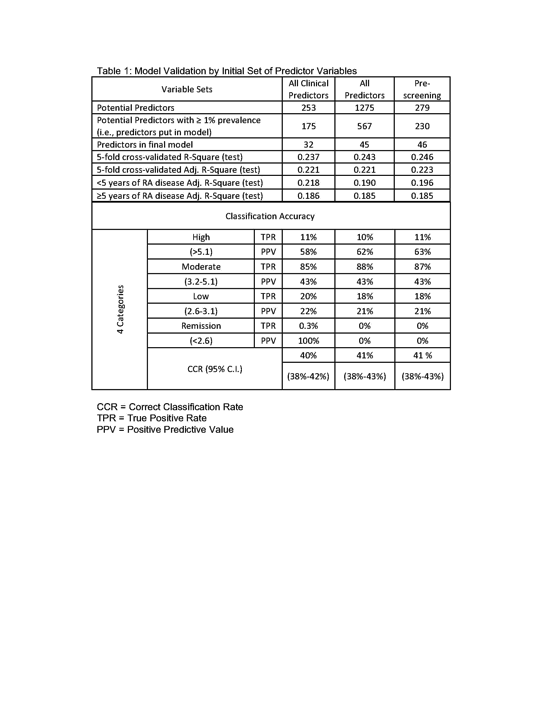
To cite this abstract in AMA style:
Sauer B, Teng CC, Accortt N, Burningham Z, Collier D, Trivedi M, Cannon GW. Models Using Claims-Based Administrative Data Are Poor Predictors of Rheumatoid Arthritis Disease Activity in VA Rheumatoid Arthritis (VARA) Patients [abstract]. Arthritis Rheumatol. 2016; 68 (suppl 10). https://acrabstracts.org/abstract/models-using-claims-based-administrative-data-are-poor-predictors-of-rheumatoid-arthritis-disease-activity-in-va-rheumatoid-arthritis-vara-patients/. Accessed .ACR Meeting Abstracts - https://acrabstracts.org/abstract/models-using-claims-based-administrative-data-are-poor-predictors-of-rheumatoid-arthritis-disease-activity-in-va-rheumatoid-arthritis-vara-patients/