ACR Meeting Abstracts

ACR Meeting Abstracts

  • Meeting Abstracts
    • All Meetings
    • ACR Convergence 2026
    • PRSYM 2026
    • ACR Convergence 2025
    • Download Abstract Supplements
  • Keyword Index
  • My Favorites
    • View & print my favorites
  • Search

Home » Meeting Abstracts » ACR/ARP Annual Meeting 2019

Abstract Number: 2729

Ixekizumab in Non-Radiographic Axial Spondyloarthritis: Primary Results from a Phase 3 Trial

Atul Deodhar1, Désirée van der Heijde 2, Lianne Gensler 3, Tae-Hwan Kim 4, Walter P. Maksymowych 5, Mikkel Østergaard 6, Denis Poddubnyy 7, Helena Marzo-Ortega 8, Louis Bessette 9, Tetsuya Tomita 10, Gaia Gallo 11, David Adams 11, Ann Leung 12, Fangyi Zhao 11, Maja Hojnik 11, Hilde Carlier 13 and Joachim Sieper 14, 1Oregon Health & Science University, Portland, OR, 2Leiden University Medical Center, Leiden, Netherlands, 3University San Francisco California, San Francisco, CA, 4Hanyang University Hospital for Rheumatic Diseases, Seoul, Republic of Korea, 5University of Alberta, Edmonton, AB, Canada, 6Copenhagen Center for Arthritis Research, University of Copenhagen, Copenhagen, Denmark, 7Charité - Universitätsmedizin Berlin and German Rheumatism Research Centre, Berlin, Germany, Berlin, Germany, 8NIHR Leeds Biomedical Research Centre, Leeds Teaching Hospitals NHS Trust, University of Leeds, Leeds, Leeds, United Kingdom, 9Laval University, Quebec City, QC, Canada, 10Osaka University Graduate School of Medicine, Osaka, Japan, 11Eli Lilly and Company, Indianapolis, IN, 12Syneos Health, Raleigh, NC, 13Eli Lilly and Company, Indianapolis, 14Charité Universitätsmedizin Berlin, Germany, Berlin, Germany

Share on X (Twitter) Share on Facebook Share on LinkedIn Share on Email
Print

Meeting: ACR/ARP Annual Meeting 2019

Keywords: axial spondyloarthritis and interleukins (IL), non-radiographic

Session Information

Date: Tuesday, November 12, 2019

Title: 5T047: Plenary III (2727–2732)

Session Type: Plenary Session III

Session Time: 11:00AM-12:30PM

Background/Purpose: Ixekizumab (IXE), a high affinity IL-17A monoclonal antibody, previously showed efficacy in AS/radiographic-axSpA1,2. COAST-X (NCT02757352) is a phase 3 study that assessed efficacy and safety of IXE in patients (pts) with active nr-axSpA and objective signs of inflammation.

Methods: COAST-X was a 52-wk, randomized, double-blind, PBO-controlled study enrolling adults with an established diagnosis of axSpA who met ASAS classification (but not modified New York) criteria, had BASDAI ≥4, back pain ≥4, inflammation [sacroiliitis on MRI or elevated CRP >5 mg/L], and inadequate response or intolerance to NSAIDs. All images were centrally read. After stratification by country and screening MRI/CRP status, pts were randomized 1:1:1 to 80 mg IXE every 4 wks (Q4W), 80 mg IXE every 2 wks (Q2W), or PBO. Changes to conventional background medication (NSAIDs, csDMARDs, analgesics, and low dose corticosteroids) as well as escape to open label (OL) IXE Q2W were allowed at investigator discretion after Wk 16. Subsequent escape to OL TNF-inhibitor treatment was permitted after ≥8 wks of OL IXE Q2W. Primary endpoints were ASAS40 at Wks 16 and 52. Patients missing data or switched to OL IXE Q2W were imputed as non-responder. A logistic regression model with nonresponder imputation was used for categorical data. A mixed effects model of repeated measures was used for continuous variables. Analysis of covariance was used for sacroiliac joint (SIJ) MRI SPARCC scores.

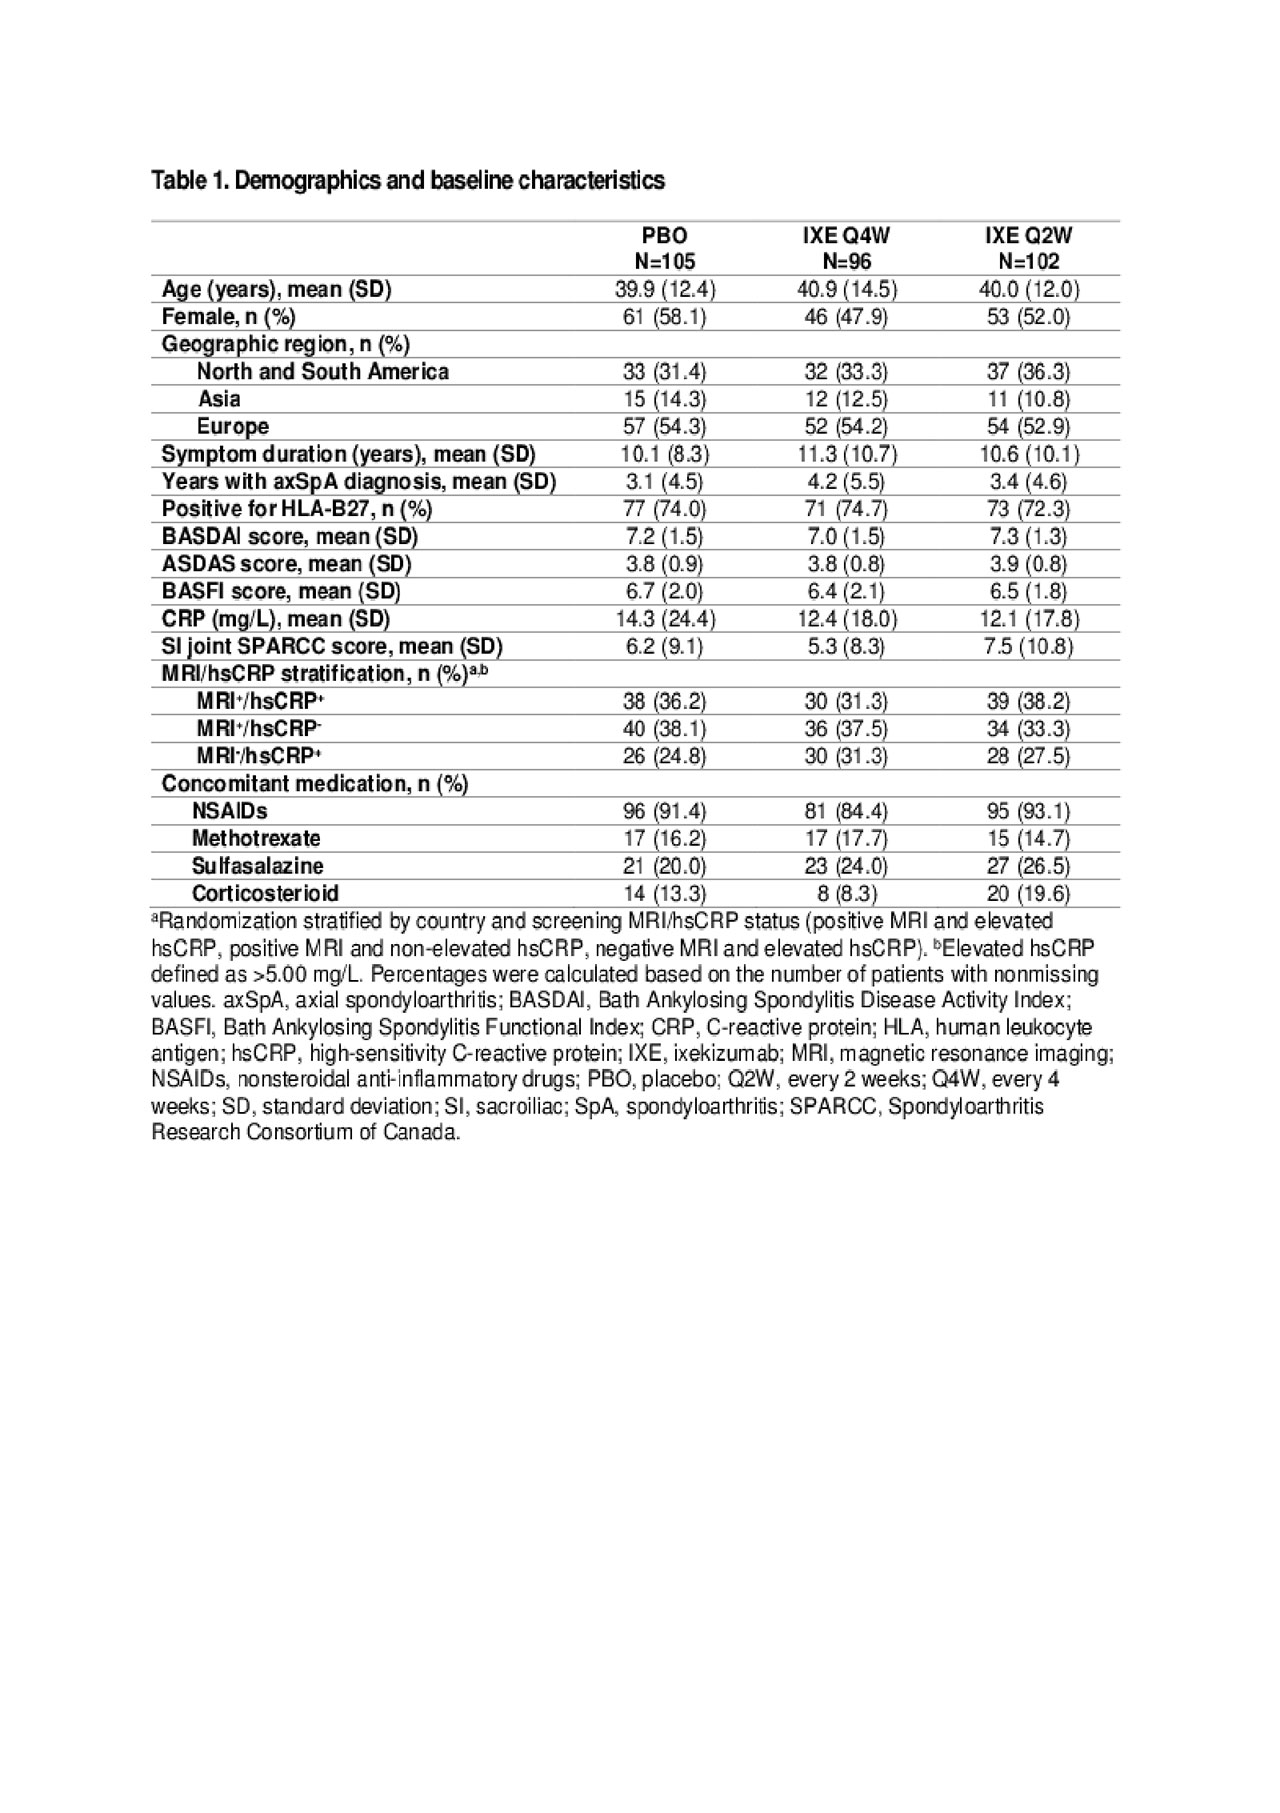
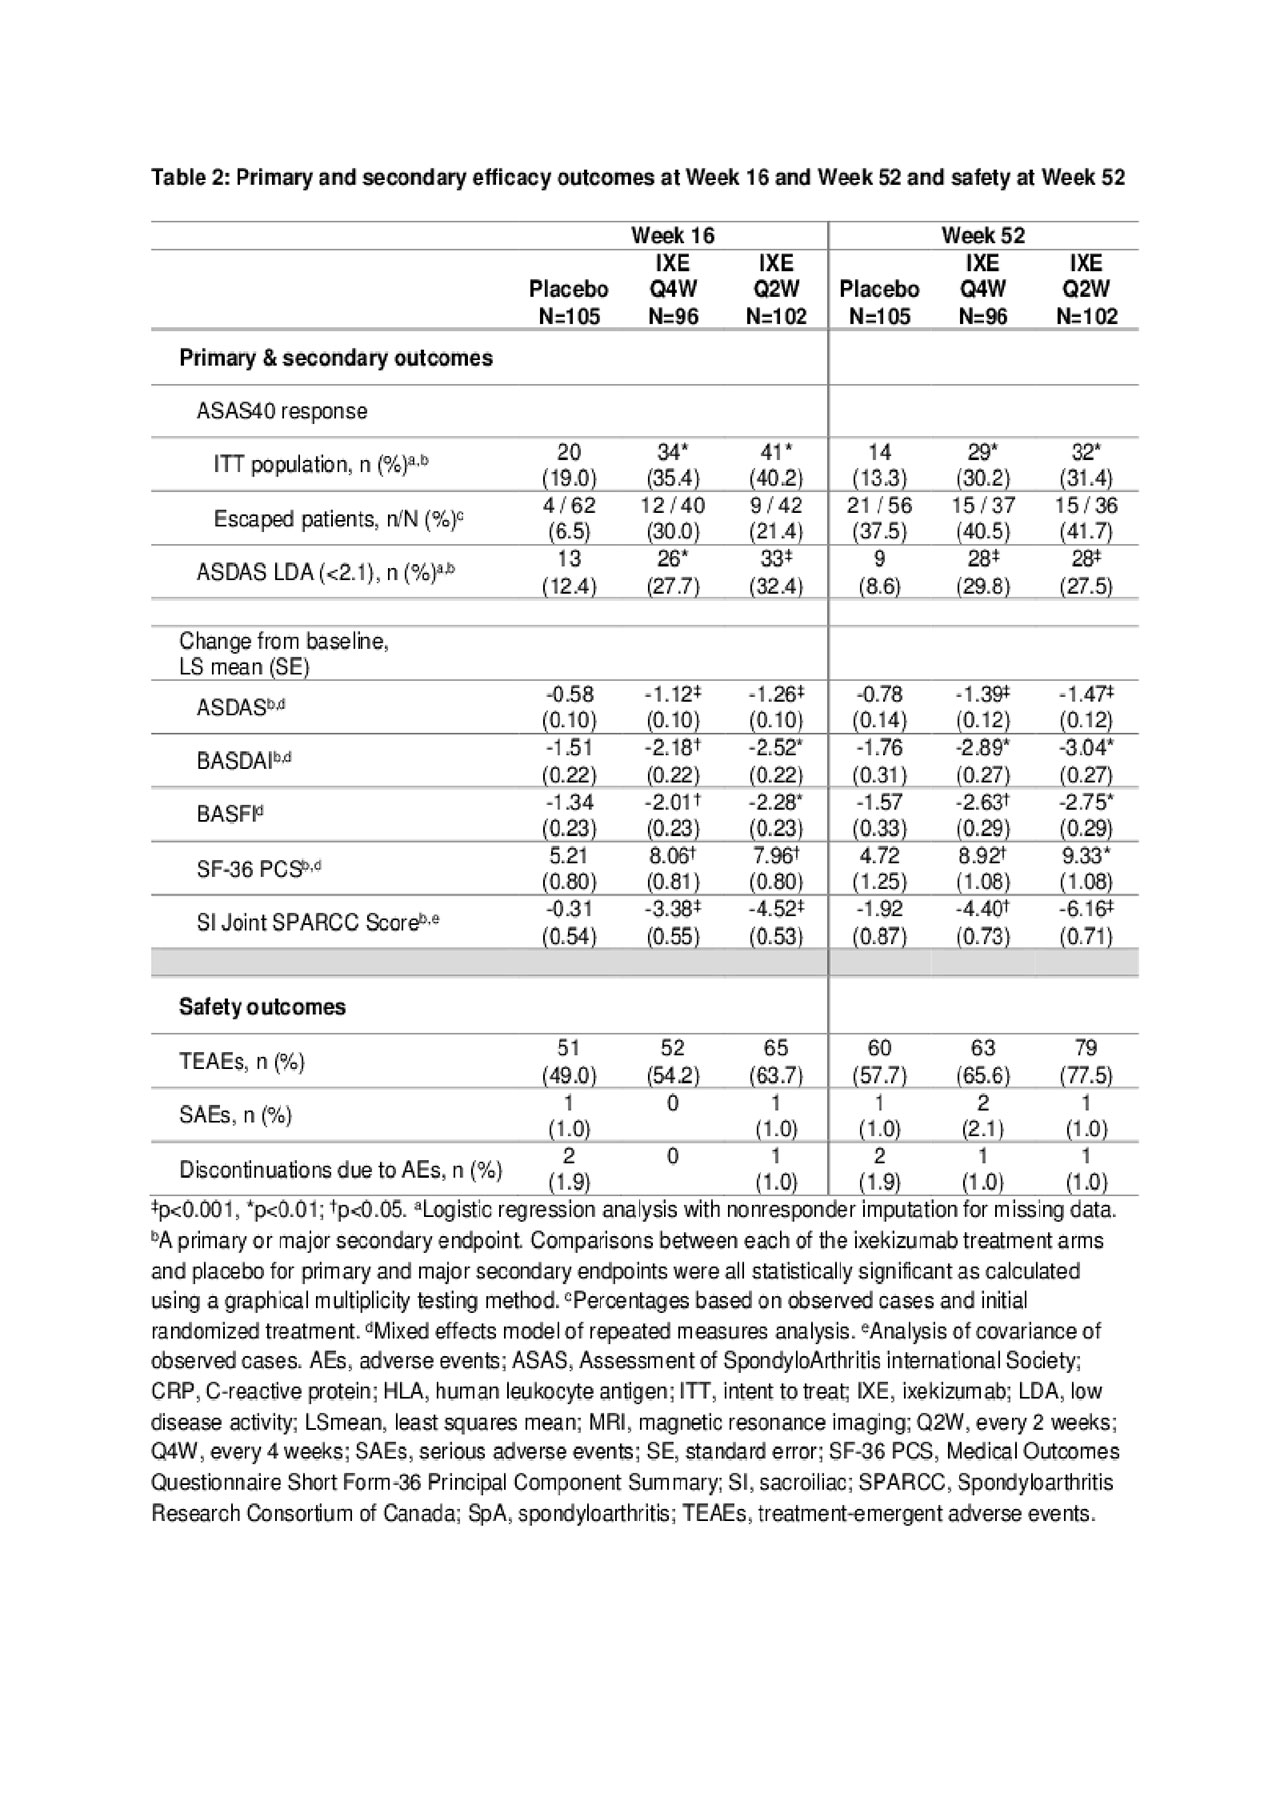
Results: Table 1 shows baseline characteristics; 303 subjects were randomized: PBO (N=105), IXE Q4W (N=96), IXE Q2W (N=102). Significantly more pts achieved ASAS40 at Wk 16: IXE Q2W (40%), IXE Q4W (35%) vs PBO (19%, p< 0.01) and at Wk 52: IXE Q2W (31%), IXE Q4W (30%) vs PBO (13%, p< 0.01) (Fig. & Table 2). Compared to PBO, pts on either IXE regimen had significantly greater changes from baseline at Wk 16 and Wk 52 for disease activity, functional status, and SIJ SPARCC scores (Fig. & Table 2). Statistically significant improvements for both IXE regimens vs PBO were first observed at Wk 1 for ASAS40. A notable proportion of pts who escaped to OL IXE Q2W had ASAS40 response at the time of escape (16.7%, 25%, and 6.5% on IXE Q2W, IXEQ4W, and PBO, respectively), and ASA40 rates increased further on open label IXE Q2 (Table 2). The frequency of serious adverse events and adverse events that led to treatment discontinuation was low and similar across all arms (Table 2). No new safety signal was identified. Conclusion: The primary endpoint of ASAS40 and all major secondary endpoints for IXE Q4W and Q2W were met at Wk 16 and Wk 52 with no unexpected safety findings. IXE added to conventional background medication was superior to conventional background medication and PBO for improving signs, symptoms, and inflammation on MRI in pts with nr-axSpA.

References

  1. Deodhar, et al. (2018). Arthritis Rheumatol. 71(4):599-611.
  2. van der Heijde, et al. (2018). Lancet. 392(10163):2441-51.
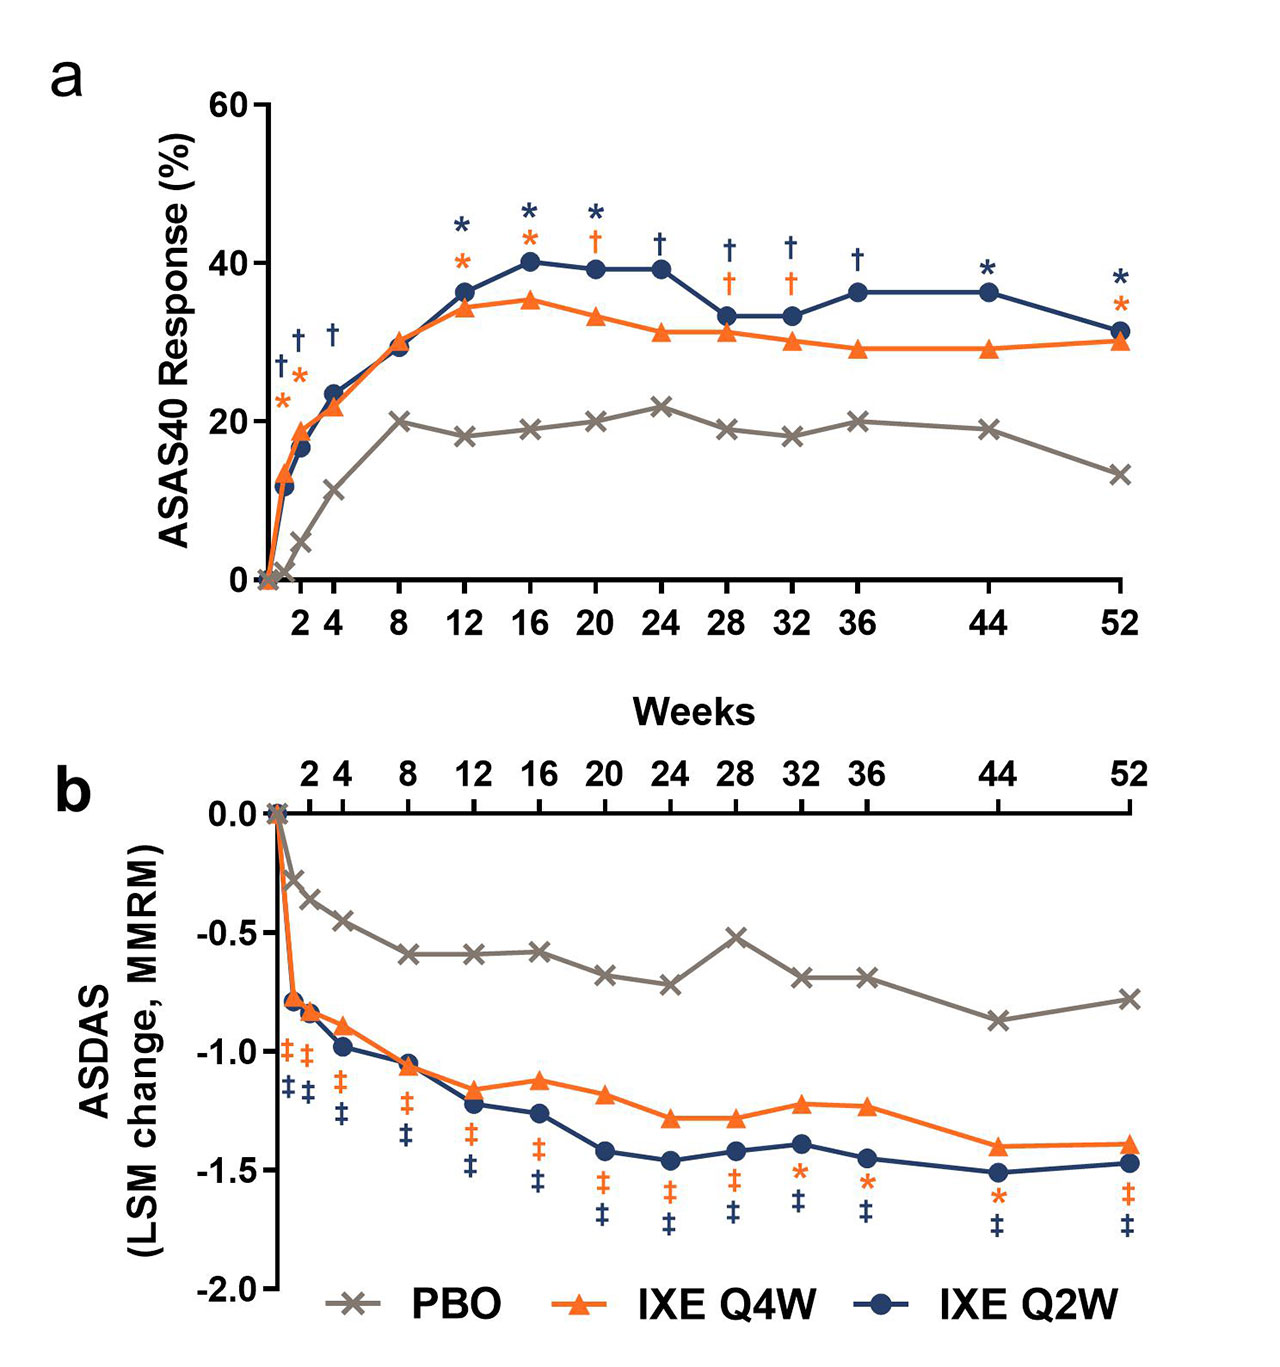
Figure: Key efficacy outcomes over 52 weeks. -a- ASAS40 responses and -b- ASDAS LSM change from baseline over 52 weeks are shown for PBO, IXE Q4W, and IXE Q2W. For ASAS40, a logistic regression model was used for comparisons between placebo and IXE treatment arms; missing data and switch to open-label IXE Q2 were considered as nonresponse. For ASDAS comparisons were made by mixed model of repeated measures -MMRM-. ‡p<0.001, *p<0.01; †p<0.05. ASAS, Assessment of SpondyloArthritis international Society; ASDAS, Ankylosing Spondylitis Disease Activity Scores; IXE, ixekizumab; LSM, least squares mean; PBO, placebo; Q2W, every 2 weeks; Q4W, every 4 weeks.


Table 1


Table2


Disclosure: A. Deodhar, AbbVie, 2, 5, 9, Abbvie, 5, 8, Abbvie, Amgen, Boehringer Ingelheim, BMS, Eli Lilly, GlaxoSmithKline, Janssen, Novartis AG, Pfizer, and UCB Pharma, 5, 8, AbbVie, Amgen, Boehringer Ingelheim, BMS, Eli Lilly, GSK, Galapagos, Janssen, Novartis, Pfizer and UCB, 5, AbbVie, Amgen, Boehringer Ingelheim, Bristol Myers Squibb, Eli Lilly, Glaxo Smith and Klein, Janssen, Novartis, Pfizer, UCB, 5, Amgen, 5, 8, 9, BMS, 2, 5, 8, BMS, Eli Lilly, Glaxo Smith & Kline, Janssen, Novartis, Pfizer, UCB, 2, BMS, Eli Lilly, GlaxoSmithKline, Janssen, Novartis AG, Pfizer, UCB Pharma, 2, Boehringer Ingelheim, 5, 8, Boehringer-Ingelheim, 5, 8, Bristol Myers Squibb, 2, 5, Bristol-Myers Squibb, 2, 5, 8, Eli Lilly, 2, 5, 8, 9, Eli Lilly and Company, 2, 5, Eli Lilly,, 5, Eli Lilly, GSK, Novartis, Pfizer and UCB, 2, Galagagos, 5, Galapagos, 5, 8, 9, Glaxo Smith & Klein, 2, Glaxo Smith & Kline, 2, 5, 8, Glaxo Smith Klein, 5, Glaxo SmithKlein, 2, 5, GlaxoSmithKlein, 2, 5, GlaxoSmithKline, 2, 5, 8, GSK, 2, 5, Janssen, 2, 5, 8, 9, Janssen Pharmaceutica, 2, 5, Janssen Research & Development, LLC, 2, Lilly, 2, 5, Novartis, 2, 5, 8, 9, Pfizer, 2, 5, 8, 9, UCB, 2, 5, 8, 9; D. van der Heijde, AbbVie, 5, AbbVie, Amgen, Astellas, AstraZeneca, BMS, 5, Amgen, 5, Astellas, 5, 9, Astellas Pharma, 5, AstraZeneca, 5, BMS, 5, Boehringer Ingelheim, 5, Boehringer Ingelheim, Celgene, Daiichi, Eli-Lilly, Galapagos, Gilead, GSK, Janssen, Merck, Novartis, Pfizer, Regeneron, Roche, Sanofi, Takeda, UCB, 5, Boehringer-Ingelheim, 5, Bristol-Myers Squibb, 5, Celgene, 5, Daiichi, 5, 9, Daiichi Sankyo, 5, Director of Imaging Rheumatology, 6, Director of Imaging Rheumatology bv, 9, Eli Lilly, 5, Eli Lilly and Company, 5, Eli-Lilly, 5, Galapagos, 5, Gilead, 5, Gilead Sciences, Inc., 5, GlaxoSmithKline, 5, Glaxo-Smith-Kline, 5, GSK, 5, 8, Imaging Rheumatology bv, 9, Imaging Rheumatology BV, 9, Imaging Rheumatology bv., 9, Janssen, 5, 8, Janssen Pharmaceutica, 5, Merck, 5, 8, Novartis, 5, 8, Pfizer, 5, 8, Pfizer Inc, 5, Regeneron, 5, 8, Rheumatology bv, 4, 9, Roche, 5, 8, Sanofi, 5, 8, Takeda, 5, 8, Takeda Pharmaceutical Company, 5, UCB, 5, 8, UCB Pharma, 5; L. Gensler, AbbVie, 2, 5, Abbvie, 2, 9, Amgen, 2, Amgen, AbbVie and Novartis, 2, Center for Disease Control, 8, Division of Vaccine Injury Compensation, 8, Eli Lilly, 5, 9, Eli Lilly and Company, 9, Galapagos, 5, 9, Galapagos, Janssen, Eli Lilly, Novartis, Pfizer, and UCB, 5, Janssen, 5, 9, Novartis, 2, 5, 9, Pfizer, 2, 9, Spondylitis Association of America, 6, Spondyloarthritis Research and Treatment Network (SPARTAN), 6, UCB, 2, 5, 9, UCB Pharma, 2, 9; T. Kim, None; W. Maksymowych, Eli Lilly and Company, 2, 5, 8, AbbVie, 2, 5, 8, Novartis, 2, 5, 8, Pfizer, 2, 5, 8, UCB, 2, 5, 8, Celgene, 5, Boehringer Ingelheim, 5, Galapagos, 5, CaRE Arthritis, 6; M. Østergaard, AbbVie, 2, 8, 9, Abbvie, 2, 5, 8, Abbvie, BMS, Boehringer-Ingelheim, Celgene, Eli Lilly, Hospira, Janssen, Merck, Novartis, Novo, Orion, Pfizer, Regeneron, Roche, UCB, 5, 8, Abbvie, BMS, Boehringer-Ingelheim, Celgene, Eli-Lilly, Hospira, Janssen, Merck, Novartis, Novo, Orion, Pfizer, Regeneron, Roche, and UCB, 5, 8, Abbvie, Celgene, Centocor, Merck, and Novartis, 2, Abbvie, Celgene, Centocor, Merck, Novartis, 2, BMS, 2, 5, 8, 9, Boehringer Ingelheim, 5, 8, Boehringer-Ingelheim, 2, 8, Boehringer-ingelheim, 9, Celgene, 2, 5, 8, Centocor, 2, Eli Lilly, 5, 8, 9, Eli Lilly and Company, 5, 8, Eli-Lilly, 2, 8, Hospira, 2, 5, 8, Janssen, 2, 5, 8, 9, Merck, 2, 5, 8, 9, Novartis, 2, 5, 8, Novo, 2, 5, 8, Novo Nordisk, 5, 8, Orion, 2, 5, 8, Pfizer, 2, 5, 8, 9, Regeneron, 2, 5, 8, Roche, 2, 5, 8, roche, 9, Sandoz, 2, 8, Sanofi, 2, 8, UCB, 2, 5, 8; D. Poddubnyy, Abbvie, 2, 5, 8, AbbVie, 2, 5, 8, BMS, 5, 8, Celgene, 5, 8, Eli Lilly, 5, 8, Eli Lilly and Company, 2, 5, 8, Lilly, 5, 8, MSD, 2, 5, 8, Novartis, 2, 5, 8, Pfizer, 2, 5, 8, Roche, 5, 8, UCB, 5, 8; H. Marzo-Ortega, AbbVie, 5, 8, AbbVie, Celgene, Janssen, Lilly, Novartis, Pfizer and UCB, 5, Abbvie, Celgene, Janssen, Lilly, Novartis, Pfizer, Ucb, 5, 8, AbbVie, Celgene, Janssen, Lilly, Novartis,Pfizer and UCB, 8, Celgene, 5, 8, Eli Lilly and Company, 5, 8, Janssen, 2, 5, 8, Janssen and Novartis, 2, Janssen, Novartis, 2, Novartis, 2, 5, 8, Pfizer, 5, 8, UCB, 5, 8; L. Bessette, AbbVie, 2, 5, 8, Abbvie, 2, 5, 8, Amgen, 2, 5, 8, Amgen, BMS, Janssen, Roche, UCB Pharma, AbbVie Inc, Pfizer, Merck, Celgene, Sanofi, Eli Lilly, and Novartis., 2, 5, 8, BMS, 2, 5, 8, Bristol-Myers Squibb, 2, 5, 8, Bristol-Myers-Squibb, 2, 5, 8, Celgene, 2, 5, 8, Eli Lilly, 2, 5, 8, Eli Lilly and Company, 2, 5, 8, Janssen, 2, 5, 8, Lilly, 2, 5, 8, Merck, 2, 5, 8, Novartis, 2, 5, 8, Pfizer, 2, 5, 8, Pfizer Inc, 2, 5, Roche, 2, 5, 8, Sanofi, 2, 5, 8, UCB, 2, 5, 8, UCB Pharma, 2, 5; T. Tomita, AbbVie, 5, 8, Astellas, 5, 8, BMS, 5, 8, Eisai, 5, 8, Eli Lilly and Company, 5, 8, Janssen, 5, 8, Mitsubishi Tanabe, 5, 8, Novartis, 5, 8, Takeda, 5, 8, Pfizer, 5, 8; G. Gallo, Eli Lilly, 1, 3, 4, Eli Lilly and Company, 1, 3, 4; D. Adams, David Adams, 3, 4, Eli Lilly and Company, 1, 3; A. Leung, None; F. Zhao, Eli Lilly, 1, 3, 4, Eli Lilly and Company, 1, 3, 4; M. Hojnik, Eli Lilly and Company, 3, 4; H. Carlier, Eli Lilly and Company, 1, 3, 4; J. Sieper, AbbVie, 5, 8, Eli Lilly and Company, 5, 8, Janssen, 5, 8, Lilly, 5, 8, Merck, 5, 8, Novartis, 5, 8.

To cite this abstract in AMA style:

Deodhar A, van der Heijde D, Gensler L, Kim T, Maksymowych W, Østergaard M, Poddubnyy D, Marzo-Ortega H, Bessette L, Tomita T, Gallo G, Adams D, Leung A, Zhao F, Hojnik M, Carlier H, Sieper J. Ixekizumab in Non-Radiographic Axial Spondyloarthritis: Primary Results from a Phase 3 Trial [abstract]. Arthritis Rheumatol. 2019; 71 (suppl 10). https://acrabstracts.org/abstract/ixekizumab-in-non-radiographic-axial-spondyloarthritis-primary-results-from-a-phase-3-trial/. Accessed .

ACR Meeting Abstracts - https://acrabstracts.org/abstract/ixekizumab-in-non-radiographic-axial-spondyloarthritis-primary-results-from-a-phase-3-trial/

My Favorites

Save and print abstracts during your browser session by clicking the “Favorite” button at the bottom of any abstract (must have cookies enabled in browser). See saved favorites.

Abstract Policies

  • ACR Convergence Abstract Embargo Policies
  • ACR Convergence Abstract Permissions & Reprints
  • PRSYM Abstract Policies

ACR Convergence. Where Rheumatology Meets

ACR Convergence 2026

Join us November 6-11 in Orlando, Florida.
See Registration Information

  • Contact ACR
  • Privacy Policy
  • ACR Policies
  • Cookie Preferences

© Copyright 2026 American College of Rheumatology