
Session Information
Date: Sunday, November 13, 2016
Title: Miscellaneous Rheumatic and Inflammatory Diseases - Poster I
Session Type: ACR Poster Session A
Session Time: 9:00AM-11:00AM
Background/Purpose: Familial Mediterranean fever (FMF), the most common form of hereditary autoinflammatory diseases, is associated with increased risk for secondary (AA) amyloidosis. We herein aimed to investigate the features of FMF patients with amyloidosis with respect to their responses to current therapies.
Methods: We enrolled FMF patients with amyloidosis who were regularly followed-up for at least 6 months between 1978 and 2015 into the study. Starting times for colchicine, anakinra or canakinumab and treatment responses were recorded using a standard form. Proteinuria (spot urine protein/creatinine ratio) and C-reactive protein (CRP) levels were measured in every three months during follow-up. Partial response was defined as ³ 50% decrease in baseline proteinuria accompanied by a normal serum creatinine level, whereas complete response was defined as <0.3 gr/d baseline proteinuria and stable serum creatinine. Chi-square test was used to test associations between treatment response and CRP concentrations.
Results: We identified 79 FMF patients with confirmed AA-type amyloidosis, and all were on colchicine treatment. Their demographic features are shown in Table 1. Mean time to diagnosis after the first symptom was 10 years. Patients were evaluated for partial and complete response after mean follow-up period of 66±85 months. Response to full-dose colchicine was observed in 30/65 patients [partial response in 19 (29%), complete response in 11 (17%)]; and 54% was non-responder to colchicine. Anakinra was added to treatment in 22 patients with inadequate response to colchicine, which resulted in partial response in 12, and complete response in 2. Eight patients with partial response to colchicine also received anakinra for better control of attacks and/or elevated acute phase response, and a complete response was achieved in 3 patients. In 3 patients, anakinra was switched to canakinumab because of local injection site reaction (1 patient) and persistence of proteinuria (2 patients). Among those, two patients had partial response, and another underwent hemodialysis due to progressive kidney failure. No significant association was observed between normalized CRP levels and response to treatment with respect to proteinuria and creatinine levels (colchicine; p=0.67, anakinra or canakinumab;p=0.82). No serious infection requiring hospitalization was detected in association with IL-1 blockade. Table 1. Demographic features of FMF patients with amyloidosis.
| Male/Female | 40/39 |
| Age of onset (mean±SD) | 16±12(2-68) |
| Age of diagnosis (mean±SD) | 27±13(7-70) |
| Family history of FMF | 47% |
| Time to diagnosis(mo) | 121±136(2-576) |
| Family history of amyloidosis (%) | 18% |
| Arthritis at presentation (%) | 60% |
| MEFV variations (n=46) | M694V,68% V726A,10% M680I,15% Others,7% |
| IL-1 inhibitors n(%) | 43(54%) |
| Patients on hemodialysis | 7(9%) |
| Renal Transplantation n(%) | 17(21%) |
| High CRP levels in attack-free periods n(%) | 31(39%) |
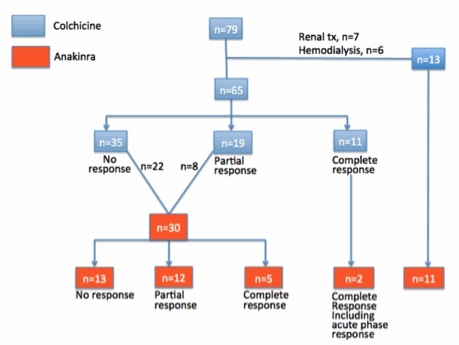
Conclusion: Amyloidosis still remains as an important complication of FMF, but patients with amyloidosis comprise a heterogeneous group including those ineffective treated with or refractory to colchicine. Therefore, it is possible to observe a satisfactory response to full-dose colchicine in an important proportion of patients. On the other hand, IL-1 inhibitors, both anakinra and canakinumab, seem to be an effective and safe option for those patients with an inadequate response to full-dose colchicine or with an intolerance to effective doses of colchicine. Efficacy of strict control of inflammatory response by IL-1 blockade on amyloidosis-associated clinical findings such as proteinuria and renal failure needs to be explored in longer series.
To cite this abstract in AMA style:
Toz B, Tecer S, Oğuz E, Erdugan M, Artim-Esen B, Kamali S, Inanc M, Ocal L, Erer B, Gul A. Efficacy of Colchicine and IL-1 Inhibitors in Amyloidosis Associated with Familial Mediterranean Fever: A Retrospective Analysis [abstract]. Arthritis Rheumatol. 2016; 68 (suppl 10). https://acrabstracts.org/abstract/efficacy-of-colchicine-and-il-1-inhibitors-in-amyloidosis-associated-with-familial-mediterranean-fever-a-retrospective-analysis/. Accessed .ACR Meeting Abstracts - https://acrabstracts.org/abstract/efficacy-of-colchicine-and-il-1-inhibitors-in-amyloidosis-associated-with-familial-mediterranean-fever-a-retrospective-analysis/