ACR Meeting Abstracts

ACR Meeting Abstracts

  • Meeting Abstracts
    • All Meetings
    • PRSYM 2026
    • ACR Convergence 2025
    • Download Abstract Supplements
  • Keyword Index
  • My Favorites
    • View & print my favorites
  • Search

Home » Meeting Abstracts » ACR Convergence 2025

Abstract Number: 0401

Longitudinal Effectiveness of Abatacept in JIA: Results From an Ongoing JIA Registry

Daniel Lovell1, Nicolino Ruperto2, Jennifer Huggins3, Ekaterina Alexeeva4, Colleen Correll5, John Bohnsack6, Stacey Tarvin7, Gabriele Simonini8, Thomas Griffin9, Andrew Zeft10, Gerd Horneff11, Pierre Quartier12, Iionka Orban13, Heather Walters14, Valda Stanevica15, Julisa Patel16, Adam M Huber17, Margalit Rosenkranz18, Daniel Kingsbury19, Rosie Scuccimarri20, Gabriel Vega Cornejo21, Joost Swart22, Robert Carroll23, Hermine Brunner1, Tina Sherrard24, Chiara Pallotti25, Clara Malattia26 and Alberto Martini26, 1Cincinnati Children's Hospital Medical Center, Cincinnati, OH, 2Università degli Studi Milano-Bicocca, Milan, Italy, 3Cincinnati Children's Medical Center, Cincinnati, OH, 4National Medical Research Center for Children’s Health Federal State Autonomous Institution of the Russian Federation Ministry of Health and I.M. Sechenov First Moscow State Medical University (Sechenovskiy University), Moscow, Russia, 5University of Minnesota, Minneapolis, MN, 6University of Utah, Salt Lake City, UT, 7Riley Hospital for Children at Indiana University, Indianapolis, IN, 8Rheumatology Unit, ERN-ReCONNET center, Meyer Children's Hospital IRCCS, Firenze, Firenze, Italy, 9Atrium Health Levine Children’s Hospital, Charlotte, NC, 10Cleveland Clinic, Cleveland, OH, 11Asklepios Klinik, Hamburg, Germany, 12Hôpital Necker-Enfants Malades, Paris, France, 13Department of Rheumatology and Clinical Immunology of Semmelweis University, Budapest, Hungary, 14Northwell, New Hyde Park, NY, 15Riga Stradiņš University, Riga, Latvia, 16Children’s Hospital of Georgia, Augusta University, Augusta, GA, 17IWK Grace Health Centre, Halifax, NS, Canada, 18University of Pittsburgh, Pittsburgh, PA, 19Randall Children’s Hospital at Legacy Emanuel, Portland, OR, 20McGill University Health Centre, Montreal, QC, Canada, 21Clinica de reumatología Guadalajara, Guadalajara, Jalisco, Mexico, 22Wilhelmina Children's Hospital / UMC Utrecht, Utrecht, Utrecht, Netherlands, 23Bristol Myers Squibb, London, United Kingdom, 24Cincinnati Children’s Hospital Medical Center, Cincinnati, OH, 25Istituto G. Gaslini, Servizio di Sperimentazioni Cliniche Pediatriche, Genova, Italy, 26Istituto G. Gaslini Pediatria II Reumatologia and University of Genova, Genova, Italy

Share on X (Twitter) Share on Facebook Share on LinkedIn Share on Email
Print

Meeting: ACR Convergence 2025

Keywords: Biologicals, clinical trial, Juvenile idiopathic arthritis, longitudinal studies, Pediatric rheumatology

Session Information

Date: Sunday, October 26, 2025

Title: (0387–0429) Pediatric Rheumatology – Clinical Poster I

Session Type: Poster Session A

Session Time: 10:30AM-12:30PM

Background/Purpose: Abatacept is a selective T-cell co-stimulation modulator approved for use in JIA. Efficacy and safety of abatacept in patients (pts) with JIA have been demonstrated previously in 2 phase 3 trials1,2 and earlier results from this phase 4 Abatacept JIA Registry (NCT01357668).3 The objective of this analysis was to provide data from a real-world setting for longitudinal safety and effectiveness of intravenous (IV) and subcutaneous (SC) abatacept in pts with JIA.

Methods: By protocol, clinical sites in the Pediatric Rheumatology Collaborative Study Group and Pediatric Rheumatology International Trial Organization enrolled pts meeting the ILAR criteria for 1 of the categories of JIA and currently taking or starting IV or SC abatacept. Planned duration of follow-up (FU) is 10 years; data were collected up to March 31, 2024. Effectiveness was assessed at day of entry into registry (baseline [BL]), 3 and 6 months, and 1, 2, 3, 4, and 5 years. Safety data were collected at each visit.

Results: Of the 740 pts enrolled, 701 were included in the analysis (476 IV, 225 SC); 561/701 (80%) were female. At BL, median age was 13.6 years and 28 (4%) pts were aged 2–5 years; JIA disease duration was 4.5 years. Median abatacept treatment duration was 6.1 months and number of active joints was 1.0 (mean 2.7). JIA categories were systemic (2%), oligo (25%), polyarticular RF-negative (48%), polyarticular RF-positive (10%), psoriatic (5%), enthesitis-related (4%), and undifferentiated (6%). Total abatacept exposure was 1513.2 pt-years with a mean/median duration of abatacept treatment of 25.9/19.7 months. At 1-year FU, pts had low Physician Global Disease Activity, low Juvenile Arthritis Multidimensional Assessment Report scores, and improvement in the number of joints with active arthritis compared with BL (Table 1). A higher percentage of pts achieved clinically inactive disease after 1 year of FU vs BL (46% vs 32%; Table 1). This trend continued despite low numbers of pts with 4 and 5 years of FU. There were 11 serious infections reported (incidence rate [IR] 0.52/100 pt-years of FU, 95% CI: 0.26, 0.92; IR 0.73/100 pt-years on treatment, 95% CI: 0.36, 1.30). There were 17 autoimmune events (IR 0.80/100 pt-years of FU, 95% CI: 0.46, 1.28; IR 1.12/100 pt-years on treatment, 95% CI: 0.65, 1.80). There were 2 adverse event malignancies (n=1 each: medulloblastoma, T-cell lymphoma). No cases of tuberculosis were reported. There was 1 unrelated death (pre-existing cardiac problems).

Conclusion: In this real-world JIA cohort, abatacept was safe and well-tolerated with no new safety risks identified. This longitudinal analysis further supports the persistent effectiveness of abatacept in pts with JIA.References: 1. Brunner HI, et al. Arthritis Rheumatol 2018;70:1144-1154.2. Ruperto N, et al. Lancet 2008;372:383-391.3. Lovell DJ, et al. Rheumatology 2024;63:S1195-S1026.Medical writing: Alexus Shirk, PhD (Caudex, an IPG Health Company), funded by Bristol Myers Squibb.
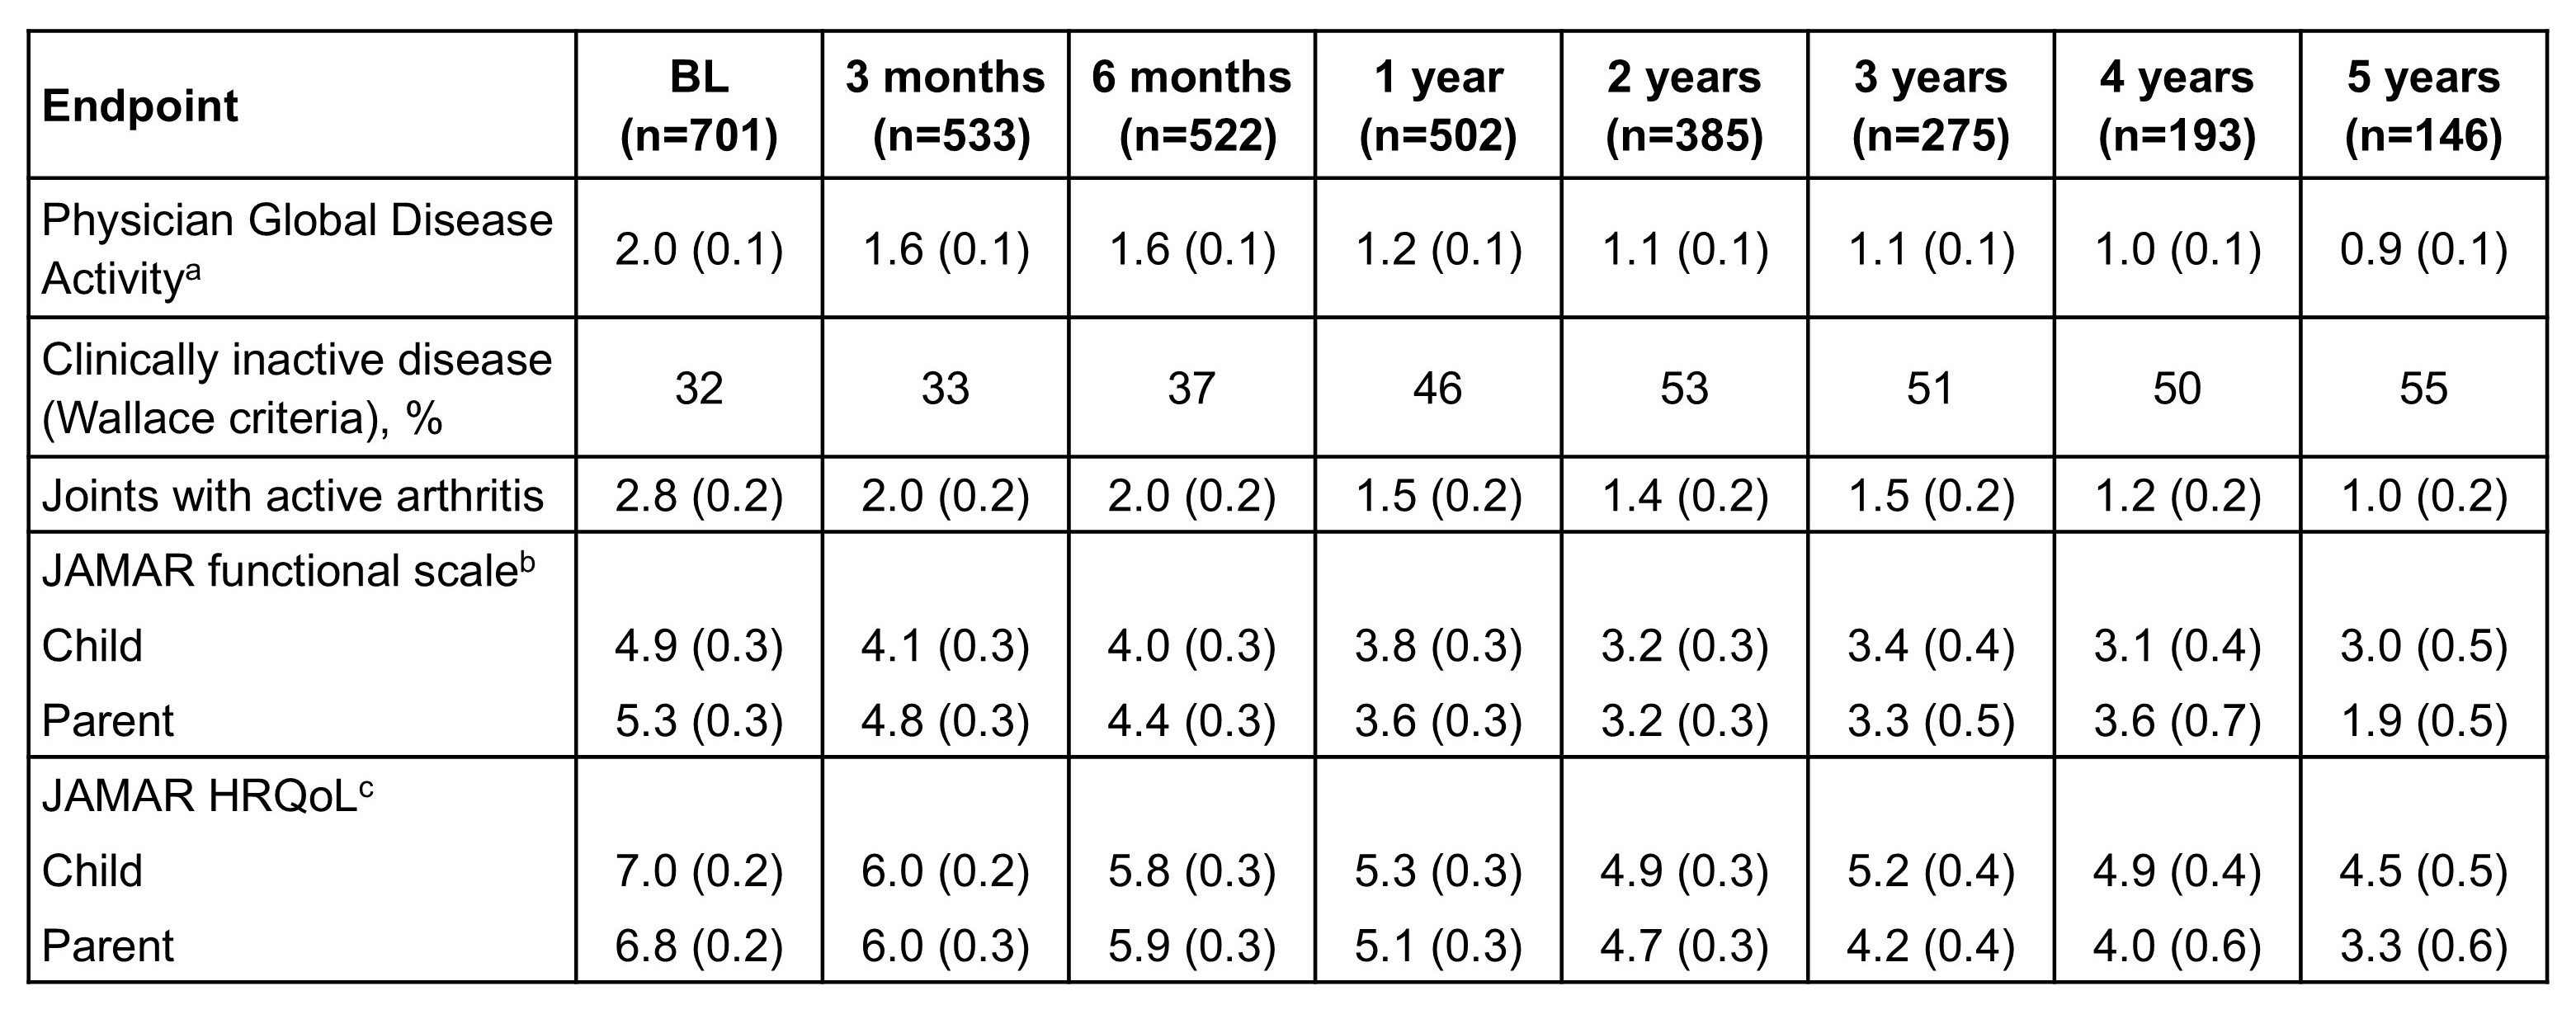
Supporting image 1Table 1. Assessment of disease activity and impact. Data are mean (SE), unless otherwise indicated. a: Visual analog scale 0–10; 0=inactive; b: Range 0–15, 0=no functional limitation; c: Range 0–15, 0=best possible HRQoL. HRQoL, health-related quality of life; JAMAR, Juvenile Arthritis Multidimensional Assessment Report; SE, standard error.


Disclosures: D. Lovell: AbbVie, 2, Bristol-Myers Squibb(BMS), 2, Canadian Arthritis Society, 12, DSMB memberNIH-NIAMS and NIAID, Canadian Arthritis Society, Novartis, 2; N. Ruperto: AbbVie/Abbott, 2, AClaris, 2, AlfaSigma, 2, Amgen, 2, AstraZeneca, 2, Aurinia, 2, Boehringer-Ingelheim, 2, Bristol-Myers Squibb(BMS), 2, Eli Lilly, 2, Galapagos, 2, Genentech, 2, Guidepoint, 2, Idorsia, 2, Janssen, 2, Novartis, 2, Pfizer, 2, Roche, 2, Sanofi, 2, Takeda, 2; J. Huggins: None; E. Alexeeva: Amgen, 12,, 5, AstraZeneca, 6, Biocad, 12,, 5, Eli Lilly, 12,, 5, Generium, 5, 6, Johnson & Johnson, 5, 6, Novartis, 5, 6, Pfizer, 12,, 5, Roche, 6, R-Pharm JSC, 5, 6, Sanofi, 12,, 5, Skopinpharm, 6, Sobi, 6, Swixx Biopharma, 6, UCB, 12,, 5; C. Correll: None; J. Bohnsack: Bristol-Myers Squibb(BMS), 5, Janssen, 5, Pfizer, 5; S. Tarvin: AbbVie/Abbott, 5, American Academy of Pediatrics, 12, Editor, Amgen, 5, Childhood Arthritis Rheumatology Research Alliance, 5, Roche, 5, UCB, 5; G. Simonini: None; T. Griffin: None; A. Zeft: GE Healthcare, 12,, Merck/MSD, 12,, Opko, 12,, Sobi, 1, Teva, 12,; G. Horneff: Janssen, 5, MSD, 5, 6, Novartis, 5, 6, Pfizer, 5, 6, Roche, 5, Sanofi, 6; P. Quartier: AbbVie, 2, 6, Chugai-Roche, 2, 6, Eli Lilly, 2, 6, Novartis, 2, 6, Pfizer, 2, 6, Sanofi, 1, 2, Sobi, 2, 6; I. Orban: None; H. Walters: None; V. Stanevica: None; J. Patel: None; A. Huber: None; M. Rosenkranz: None; D. Kingsbury: None; R. Scuccimarri: Bristol-Myers Squibb(BMS), 5, Sobi, 12, Attendee of sponsored CME; G. Vega Cornejo: None; J. Swart: None; R. Carroll: Bristol-Myers Squibb(BMS), 3; H. Brunner: AbbVie, 2, AstraZeneca-Medimmune, 2, Biogen, 2, Boehringer-Ingelheim, 2, Bristol-Myers Squibb(BMS), 2, Eli Lilly, 2, EMD Serono, 2, F. Hoffmann-La Roche, 2, Genentech, 5, GlaxoSmithKline, 2, Merck, 2, Novartis, 2, Pfizer, 2, 5, Sanofi, 2, UCB, 2; T. Sherrard: None; C. Pallotti: None; C. Malattia: None; A. Martini: Pfizer, 2.

To cite this abstract in AMA style:

Lovell D, Ruperto N, Huggins J, Alexeeva E, Correll C, Bohnsack J, Tarvin S, Simonini G, Griffin T, Zeft A, Horneff G, Quartier P, Orban I, Walters H, Stanevica V, Patel J, Huber A, Rosenkranz M, Kingsbury D, Scuccimarri R, Vega Cornejo G, Swart J, Carroll R, Brunner H, Sherrard T, Pallotti C, Malattia C, Martini A. Longitudinal Effectiveness of Abatacept in JIA: Results From an Ongoing JIA Registry [abstract]. Arthritis Rheumatol. 2025; 77 (suppl 9). https://acrabstracts.org/abstract/longitudinal-effectiveness-of-abatacept-in-jia-results-from-an-ongoing-jia-registry-2/. Accessed .

ACR Meeting Abstracts - https://acrabstracts.org/abstract/longitudinal-effectiveness-of-abatacept-in-jia-results-from-an-ongoing-jia-registry-2/

My Favorites

Save and print abstracts during your browser session by clicking the “Favorite” button at the bottom of any abstract (must have cookies enabled in browser). See saved favorites.

Abstract Policies

  • ACR Convergence Abstract Embargo Policies
  • ACR Convergence Abstract Permissions & Reprints
  • PRSYM Abstract Policies

ACR Convergence. Where Rheumatology Meets

ACR Convergence 2026

Join us November 6-11 in Orlando, Florida.
See Registration Information

  • Contact ACR
  • Privacy Policy
  • ACR Policies
  • Cookie Preferences

© Copyright 2026 American College of Rheumatology