
Session Information
Date: Monday, October 27, 2025
Title: Abstracts: Rheumatoid Arthritis – Treatment I: Preventative and Novel Treatments (1674–1679)
Session Type: Abstract Session
Session Time: 1:30PM-1:45PM
Background/Purpose: We assessed the safety and efficacy of UPA versus ADA from SELECT-COMPARE through 7-years.
Methods: Patients with RA and an inadequate response to MTX were randomized 2:2:1 to UPA 15 mg once daily, placebo(PBO), or ADA 40 mg every other week, with patients receiving background MTX. For < 20% improvement in tender or swollen joint counts at weeks 14, 18, or 22, or failure to achieve CDAI low disease activity (LDA) by week 26, patients were switched from PBO or ADA to UPA, or from UPA to ADA. All remaining on PBO switched to UPA at week 26. Safety was evaluated by exposure-adjusted event rates of treatment-emergent adverse events (TEAEs) per 100 patient-years up to 7 years (cutoff: September 19, 2024) for all patients receiving ≥1 dose of UPA or ADA. Efficacy through ~7 years was evaluated based on as observed data by treatment sequence on achievement of low disease activity (CDAI≤10) and remission (CDAI≤2.8), and DAS28(CRP) ≤3.2 and < 2.6.
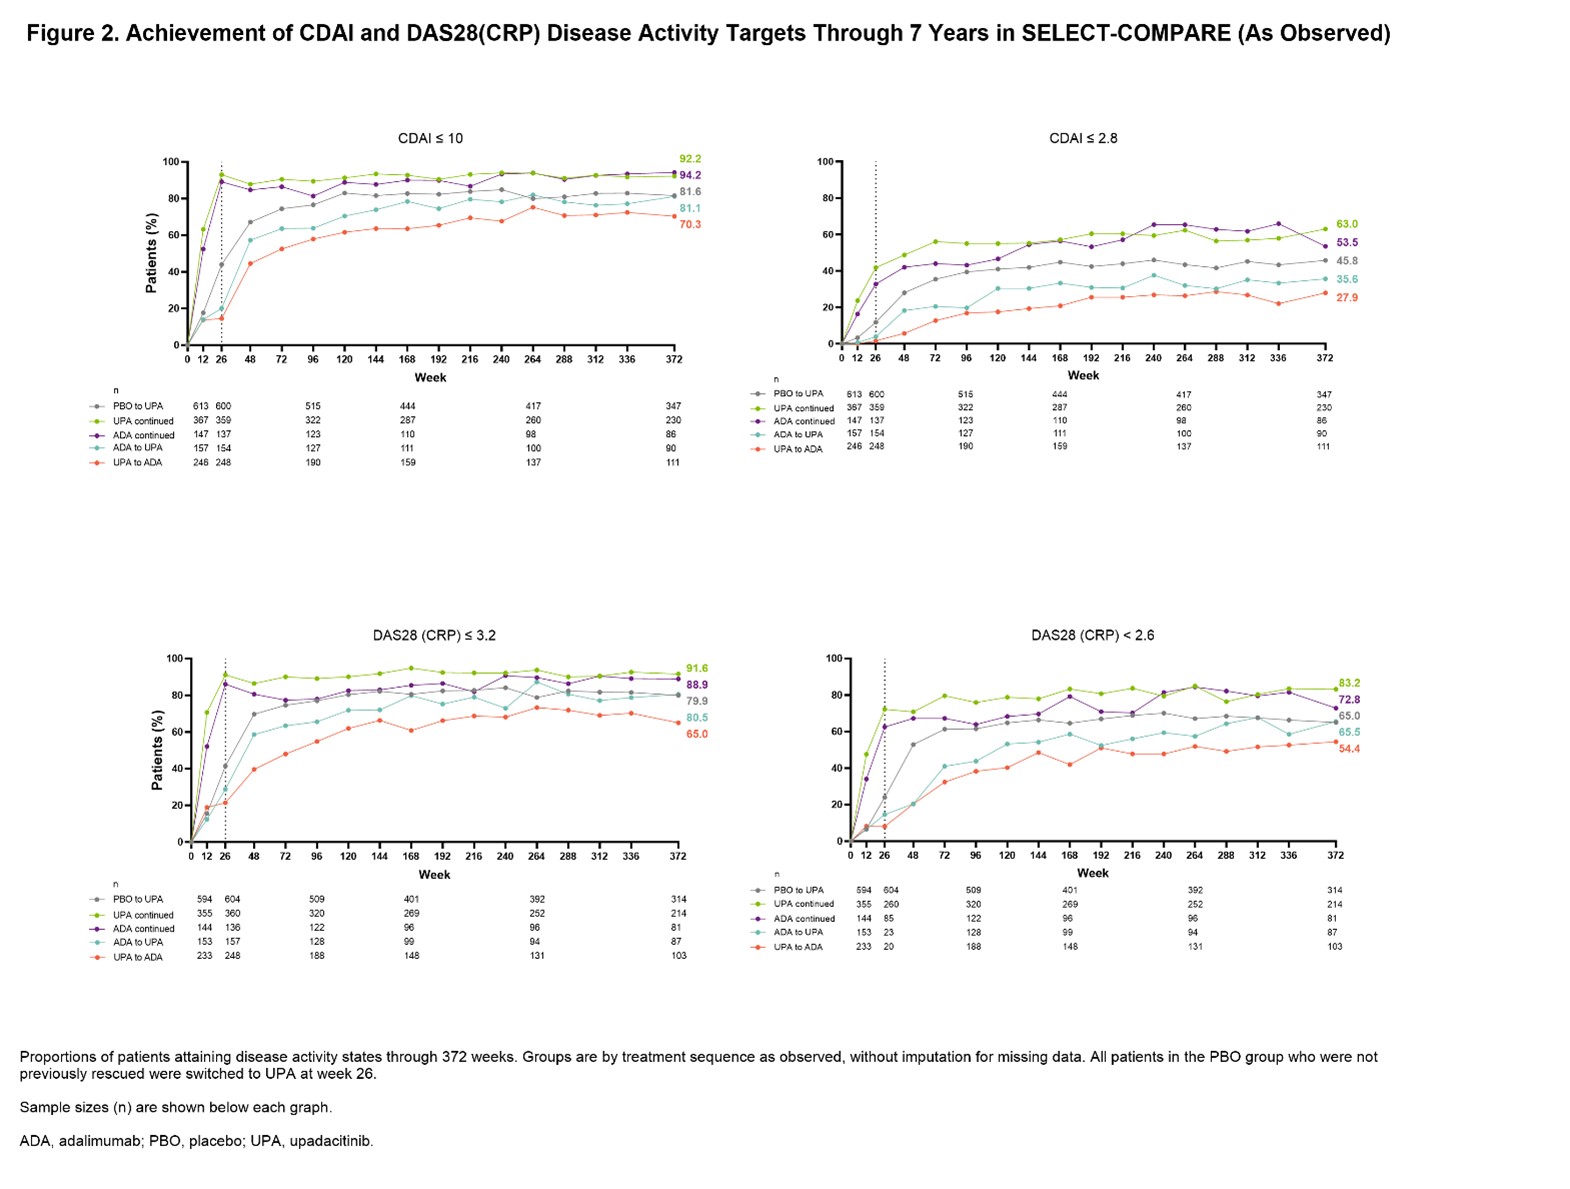
Results: 1,629 patients (PBO, Nf651;UPA, Nf651; ADA, Nf327) were randomized and treated. At 7 years, 820 patients remained on UPA or ADA (continuous UPA,n=216; PBO to UPA,n=338; continuous ADA, n=82; ADA to UPA, n=80;UPA toADA, n=104). UPA was generally well tolerated, displaying similar rates of overall TEAEs and most adverse events of special interest when compared to ADA (Figure 1). Most adverse events of special interest, such as MACE, VTE, and malignancies excluding nonmelanoma skin cancer (NMSC) occurred at similar rates for both treatments; UPA showed numerically higher rates of herpes zoster, creatine phosphokinase elevation, NMSC, lymphopenia, and hepatic disorders than ADA. Disease activity targets showed consistent achievement over 7 years, with >88% of patients receiving continuous UPA or ADA achieving CDAI LDA and/or DAS28(CRP) ≤ 3.2 at week 372. Generally similar proportions of patients receiving continuous UPA vs continuous ADA achieved CDAI remission and DAS28(CRP) < 2.6 over time. Numerically greater proportions of patients who switched from ADA to UPA after inadequate initial response achieved CDAI and DAS28(CRP) targets compared to those who switched from UPA to ADA. Evaluating efficacy responses by NRI, recognizing the limitation of applying NRI over long-term, randomized UPA showed greater efficacy than ADA at week 372 with higher rates of CDAI LDA (31.2% vs 23.5%), CDAI remission (21.8% vs 13.1%), DAS28(CRP) ≤ 3.2 (28.7% vs 20.8%), and DAS28(CRP) < 2.6 (26.4% vs 16.8%) (all comparisons, nominal P < .05).
Conclusion: The UPA safety profile at 7 years remained consistent to previous findings with no new safety concerns. Treatment with continuous UPA and ADA resulted in stable maintenance of disease activity targets over 7 years. In patients with an early insufficient response to their original treatment who switched to the alternate therapy, those who were switched from ADA to UPA showed numerically greater efficacy than those who switched from UPA to ADA.1. Conaghan P, et al. Rheumatol Ther. 2022;9:191-206. 2. Fleischmann R, et al. RMD Open. 2024;10:e004007. 3. Burmester GR, et al. RMD Open. 2023;9:e002735.

To cite this abstract in AMA style:
Fleischmann R, Swierkot J, Durez P, Bessette L, Bu X, Fish I, Gara A, Caballero D, Peterfy, MD, PhD C, Tanaka Y, Mysler E. Long-Term Safety and Efficacy of Upadacitinib or Adalimumab in Patients With Rheumatoid Arthritis: 7-Year Data From the SELECT-COMPARE Study [abstract]. Arthritis Rheumatol. 2025; 77 (suppl 9). https://acrabstracts.org/abstract/long-term-safety-and-efficacy-of-upadacitinib-or-adalimumab-in-patients-with-rheumatoid-arthritis-7-year-data-from-the-select-compare-study/. Accessed .ACR Meeting Abstracts - https://acrabstracts.org/abstract/long-term-safety-and-efficacy-of-upadacitinib-or-adalimumab-in-patients-with-rheumatoid-arthritis-7-year-data-from-the-select-compare-study/