ACR Meeting Abstracts

ACR Meeting Abstracts

  • Meeting Abstracts
    • All Meetings
    • PRSYM 2026
    • ACR Convergence 2025
    • Download Abstract Supplements
  • Keyword Index
  • My Favorites
    • View & print my favorites
  • Search

Home » Meeting Abstracts » ACR Convergence 2025

Abstract Number: 0562

Icotrokinra (ICO), a Novel Targeted Oral Peptide, in Patients (Pts) With Psoriatic Disease: Exploratory Assessments From a Phase 2 Psoriasis (PsO) Study Informing a Phase 3 Clinical Program in Psoriatic Arthritis (PsA)

Joseph F Merola1, Philip J. Mease2, Laura Coates3, Iain McInnes4, Peter Nash5, Alexis Ogdie6, Lihi Eder7, mitsumasa kishimoto8, Anna Beutler9, Konstantina Psachoulia9, Shihong Sheng10, Bei Zhou11, Mehrdad Javidi12, Chandni Valiathan12, Charles Iaconangelo10, Ya-Wen Yang13, Arun Kannan13, Chetan S. Karyekar9 and Tasneam Shagroni9, 1Department of Dermatology and Department of Medicine, UT Southwestern Medical Center, Dallas, TX, 2Department of Rheumatology, Providence-Swedish Medical Center and University of Washington, Seattle, WA, 3Nuffield Department of Orthopaedics, Rheumatology and Musculoskeletal Sciences, University of Oxford, Oxford, England, United Kingdom, 4University of Glasgow, Glasgow, United Kingdom, 5Griffith University and U of Queensland, Maroochydore, Queensland, Australia, Queensland, Australia, 6University of Pennsylvania, Philadelphia, PA, 7University of Toronto, Toronto, ON, Canada, 8Kyorin University School of Medicine, Tokyo, Japan, 9Johnson & Johnson, Spring House, PA, USA, Spring House, 10Johnson & Johnson, Chesterbrook, PA, USA, Chesterbrook, 11Johnson & Johnson, Spring House, PA, USA, Spring House, PA, 12Johnson & Johnson, San Diego, CA, USA, San Diego, 13Johnson & Johnson, San Diego, CA, USA, San Diego, CA

Share on X (Twitter) Share on Facebook Share on LinkedIn Share on Email
Print

Meeting: ACR Convergence 2025

Keywords: Biologicals, clinical trial, Dermatology, Inflammation

Session Information

Date: Sunday, October 26, 2025

Title: (0554–0592) Spondyloarthritis Including Psoriatic Arthritis – Treatment Poster I

Session Type: Poster Session A

Session Time: 10:30AM-12:30PM

Background/Purpose: PsA affects ~20-30% of pts with PsO, causing articular inflammation/damage, and impaired health-related quality of life (HRQoL). ICO, a novel targeted oral peptide that binds IL-23 Receptor, showed greater clinical response rates vs placebo (PBO) and a favorable safety profile in pts with moderate-to-severe plaque PsO in the Ph 2 FRONTIER 1&2 studies. We leveraged exploratory serum biomarker, Pt Reported Outcomes Measurement Information Systems (PROMIS-29), and Psoriasis Area and Severity Index 75% improvement (PASI75) data from a subset of FRONTIER 1 pts with PsO and PsA medical history (PsO+PsA) to support Ph 3 ICONIC-PsA 1 and ICONIC-PsA 2 studies.

Methods: Mean log fold-changes (logFC) in serum β-Defensin-2 (BD-2), IL-22, IL-17A, and IL-17F levels were summarized for FRONTIER pts with PsO only, and with PsO+PsA. Pts reported HRQoL via PROMIS-29 questionnaire. Improvements ≥5-points in PROMIS-29 domain scores (or ≥2 for pain), and physical/mental component summary (PCS/MCS) scores, are considered clinically meaningful. ICO PsA Ph 3 sample sizes were informed by ample safety data to support regulatory submission and estimates from model-based analyses, including a meta-analysis that bridged FRONTIER 1 PASI75 to expected American College of Rheumatology 20% improvement (ACR20) at Week (W)16 (primary endpoint) and meta-regression modeling that bridged ACR20 to secondary endpoints, ACR50/70, PASI90/100, Minimal Disease Activity.

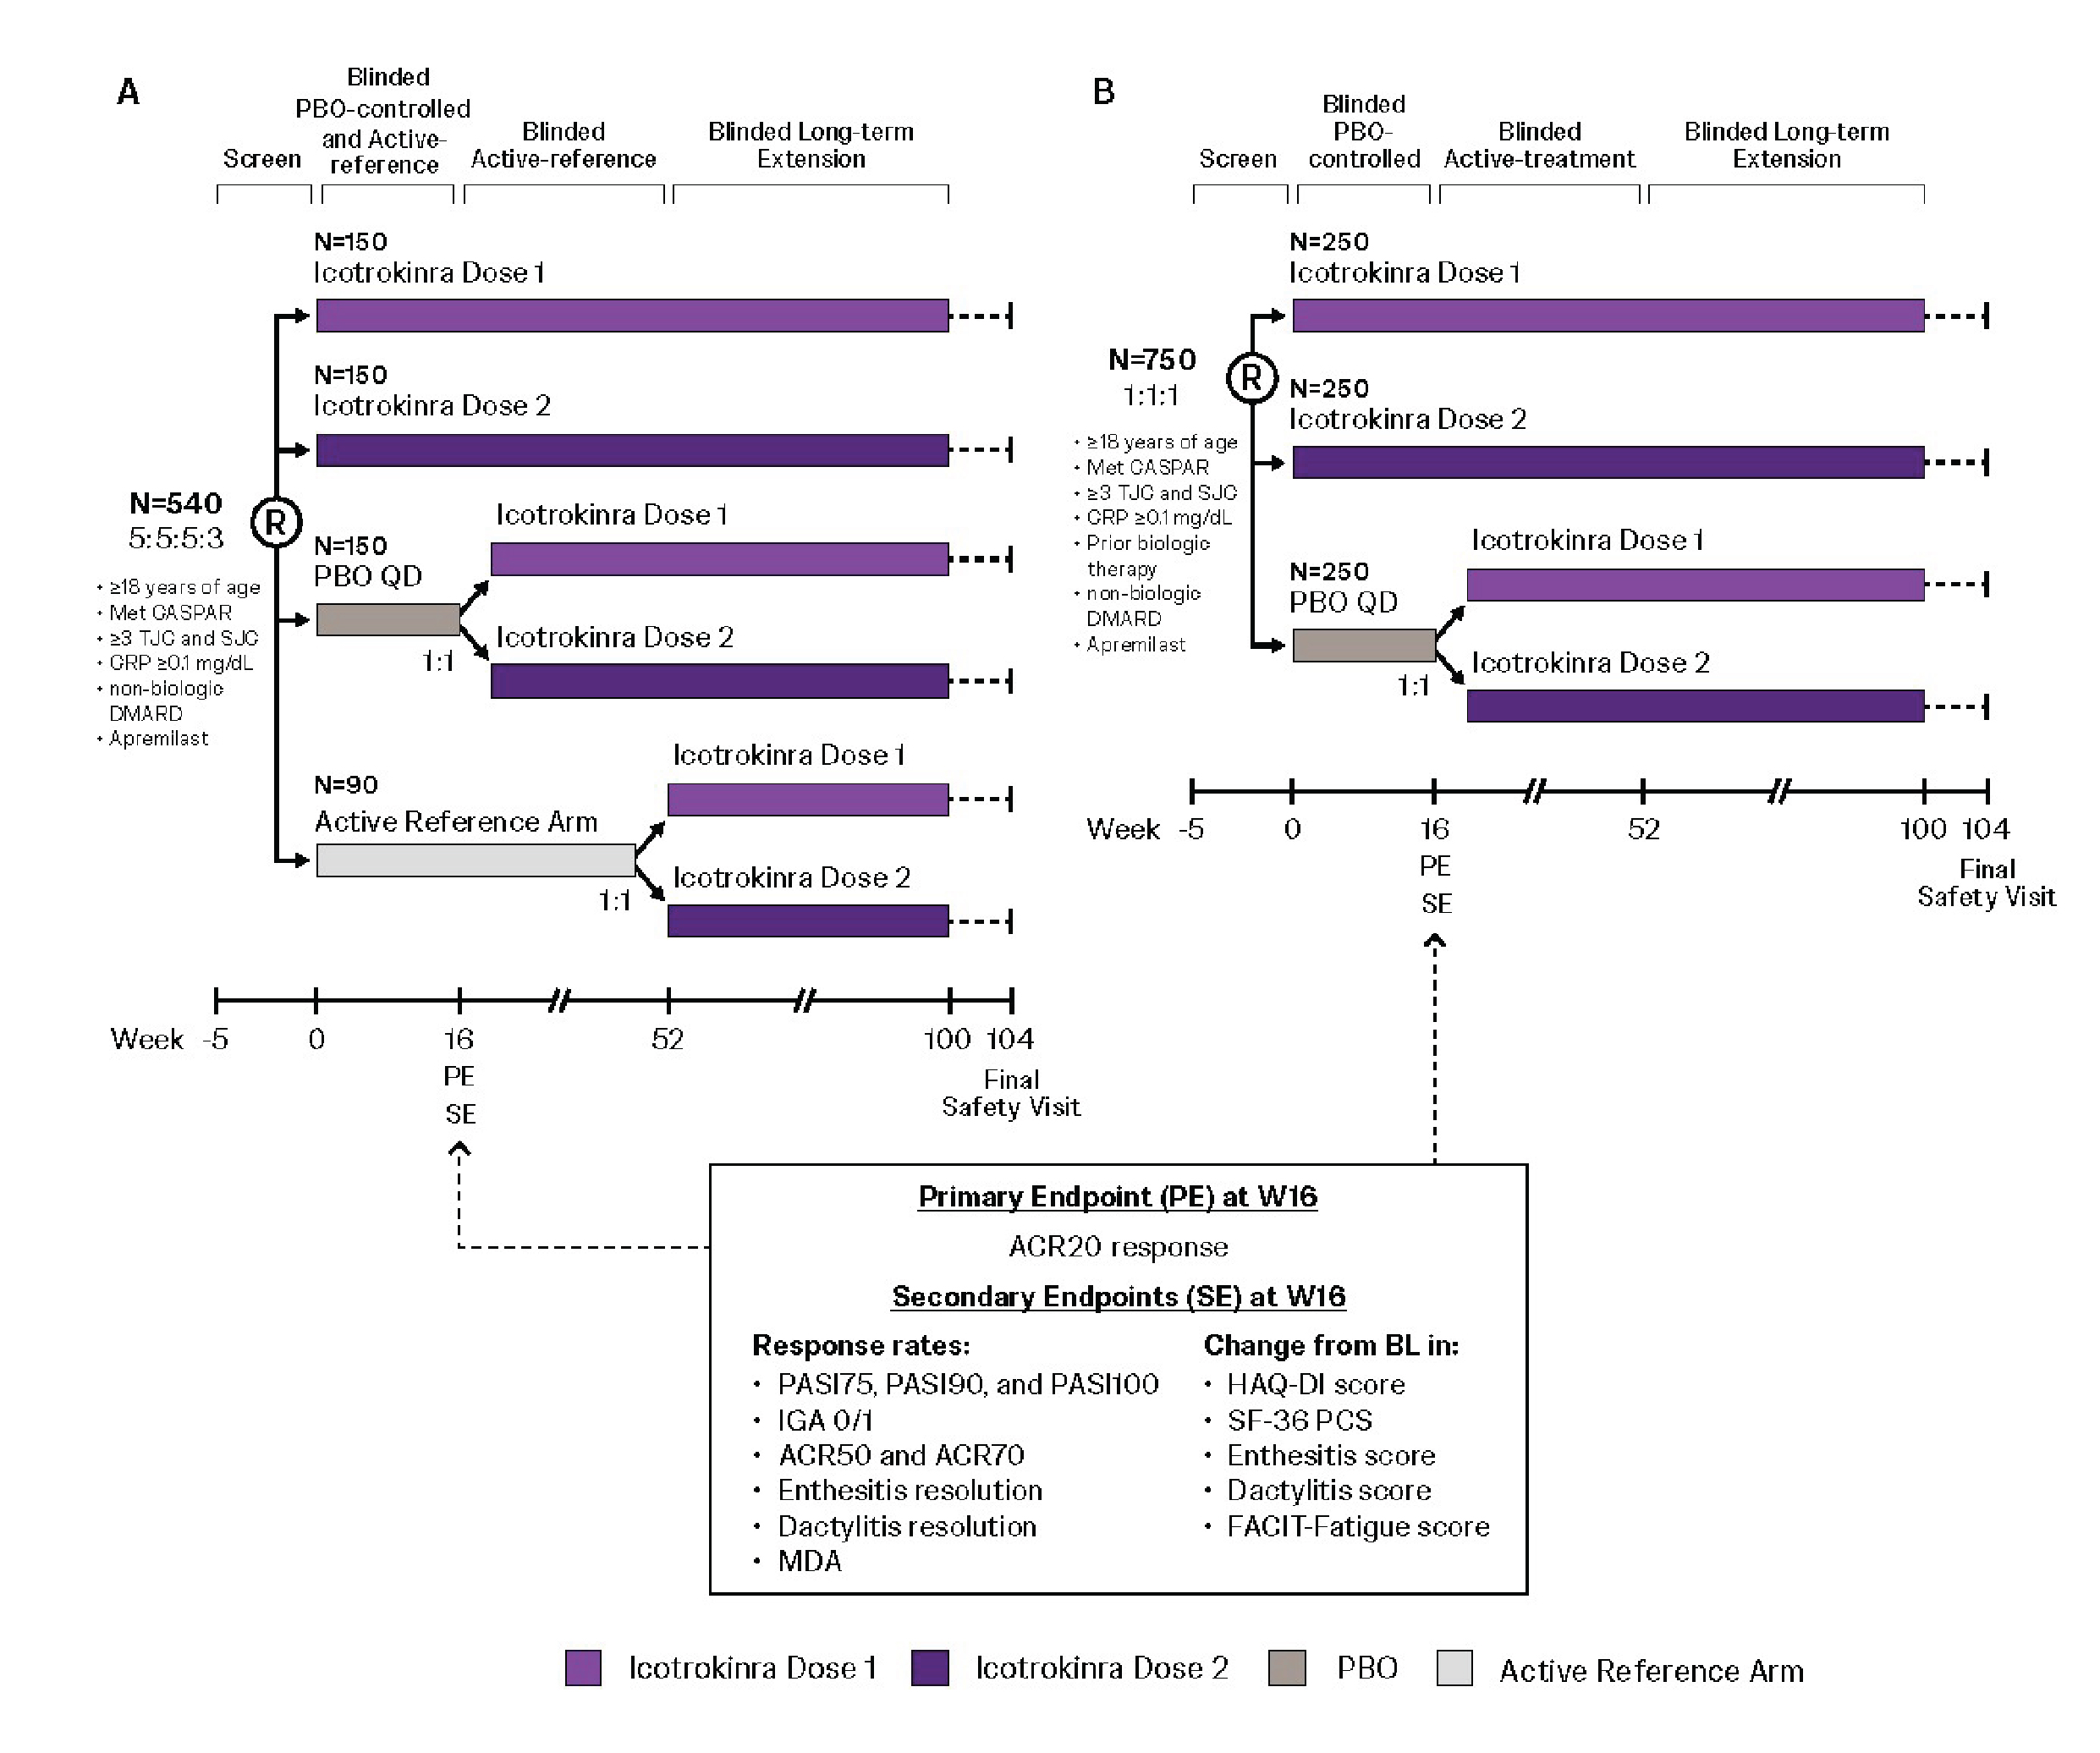
Results: 23/91 (25%) FRONTIER 1 pts had PsO+PsA (ICO, n=20; PBO, n=3). Among pts with evaluable biomarker data, mean logFC in serum BD-2, IL-22, IL-17A (Fig 1A-C), and IL-17F (data not shown) over time indicated consistent ICO pharmacodynamic (PD) effect between pts with PsO only and with PsO+PsA. ICO-treated PsO+PsA pts reported numerically greater mean changes from baseline (BL) at W16 vs PBO across PsA relevant PROMIS-29 domains, ie, improvements in physical function (7.7 vs 1) and reductions in fatigue (-7.4 vs 2.3 [worsening]), pain interference (-10.7 vs -1.3), and pain intensity (- 3.5 vs -1.5). In 20 ICO-treated pts with PsO+PsA, 45% and 70% reported ≥5 point improvement from BL in PROMIS-29 PCS and MCS scores, respectively, vs no pts receiving PBO. ICONIC-PsA 1&2 sample sizes of 540 (5:5:5:3 to ICO Dose 1/2/PBO/active reference arm with no formal statistical comparisons; Fig 2A) and 750 (1:1:1 to ICO Dose 1/2/PBO; Fig 2B) were estimated to provide ≥90% power to detect significant ICO vs PBO difference between ICO and PBO. Given minorities are often under-recruited in PsA trials, the ICO PsA program aims to assess diverse pts, of different racial/ethnicities.

Conclusion: Exploratory assessments from the Ph 2 FRONTIER 1 study showed comparable ICO PD effects between pts with PsO only, and with PsO+PsA. ICO-treated pts with PsO+PsA reported numerically greater improvements in PsA-relevant PROMIS-29 domains vs PBO. Informed by these post hoc analyses and model-based meta-analyses that bridged data from PsO to PsA, the multicenter, double-blind, PBO-controlled ICONIC-PsA 1 and ICONIC-PsA 2 studies will comprehensively evaluate the novel targeted oral peptide ICO in diverse population of pts with active PsA.
Supporting image 1Mean change in serum BD-2 (A), IL-22 (B), and IL-17A (C) levels through W16 in FRONTIER 1 participants with PsO only and PsO+PsA

Supporting image 2ICONIC PsA-1 (biologic-naïve [A]) and ICONIC PsA-2 (biologic-experienced [B]) study designs


Disclosures: J. Merola: AbbVie, 2, Amgen, 2, 5, AstraZeneca, 2, 5, Biogen, 2, 5, Boehringer Ingelheim, 2, 5, Bristol Myers Squibb, 2, 5, Dermavant, 2, 5, Eli Lilly and Company, 2, 5, Incyte, 2, Janssen, 2, 5, LEO Pharma, 2, MoonLake Immunotherapeutics, 2, 5, Novartis, 2, Pfizer, 2, Sanofi-Regeneron, 2, 5, Sun Pharma, 5, UCB, 2, 5; P. Mease: AbbVie, 2, 5, 6, Acelyrin, 2, 5, Amgen, 2, 5, 6, BMS, 2, 5, Century, 2, Cullinan, 2, Eli Lilly and Company, 2, 5, 6, Inmagene, 2, J&J Innovative Medicine, 2, 5, 6, MoonLake Immunotherapeutics, 2, Novartis, 2, 5, 6, Pfizer, 2, 5, 6, Sana, 5, Spyre, 5, Takeda, 2, UCB, 2, 5, 6; L. Coates: AbbVie, 2, 5, 6, Amgen, 2, 5, 6, Biogen, 6, BMS, 2, Boehringer Ingelheim, 2, Celgene, 2, 5, 6, Domain, 2, Eli Lilly and Company, 2, 5, 6, Galapagos, 2, 6, Gilead, 2, 5, 6, GSK, 6, Janssen, 2, 5, 6, Medac, 6, MoonLake Immunotherapeutics, 2, Novartis, 2, 5, 6, Pfizer, 2, 5, 6, UCB, 2, 5, 6; I. McInnes: AbbVie, 2, 6, AstraZeneca, 2, 6, BMS, 2, 5, 6, Boehringer Ingelheim, 2, 5, 6, Cabaletta, 2, 6, Causeway Therapeutics, 2, 6, Celgene, 2, 5, Eli Lilly and Company, 2, 6, Evelo, 2, Gilead, 5, 6, Janssen, 2, 5, 6, MoonLake Immunotherapeutics, 2, 6, Novartis, 2, 5, 6, Pfizer, 5, 6, Sanofi/Regeneron, 5, 6, UCB, 2, 5, 6; P. Nash: AbbVie, 1, 2, 5, Amgen, 1, 2, 5, Boehringer Ingelheim, 1, 2, 5, Bristol Myers Squibb, 1, 2, 5, Celgene, 1, 2, 5, Eli Lilly, 1, 2, 5, Galapagos, 1, 2, 5, GlaxoSmithKline, 1, 2, 5, Janssen, 1, 2, 5, Novartis, 1, 2, 5, Pfizer, 1, 2, 5, Sun Pharma, 1, 2, 5, UCB, 1, 2, 5; A. Ogdie: AbbVie, 2, 5, Amgen, 2, 5, 11, Bristol Myers Squibb, 2, 5, Celgene, 2, 5, CorEvitas, LLC, 2, 5, Eli Lilly, 2, 5, Forward Databank, 5, Gilead, 1, 2, Janssen, 2, 5, Kopa/Twill Health, 2, NIH/NIAMS, National Psoriasis Foundation, 5, Novartis, 2, 5, 11, Pfizer, 2, 5, 11, Rheumatology Research Foundation, 5, Spyre, 2, Takeda, 2, UCB, 2, 5, University of Pennsylvania, 5; L. Eder: AbbVie, 1, 2, 5, 6, BMS, 1, 2, Eli Lilly, 1, 2, 5, 6, Fresenius Kabi, 1, 5, J&J, 1, 2, 5, Janssen, 1, 5, Novartis, 1, 2, 5, 6, Pfizer, 1, 2, 5, UCB, 1, 2, 5; m. kishimoto: AbbVie, 2, 6, Amgen, 2, 6, Asahi-Kasei Pharma, 2, 6, Astellas, 2, 6, Ayumi, 2, 6, BMS, 2, 6, Celgene, 2, 6, Chugai, 2, 6, Daiichi-Sankyo, 2, 6, Eisai, 2, 6, Eli Lilly, 2, 6, Gilead, 2, 6, Johnson & Johnson, 2, 6, Kyowa Kirin, 2, 6, Novartis, 2, 6, Ono Pharma, 2, 6, Takeda, 2, 6, Tanabe-Mitsubishi, 2, 6, UCB, 2, 6; A. Beutler: Johnson & Johnson, 3; K. Psachoulia: Johnson & Johnson, 3, 11; S. Sheng: Johnson & Johnson, 3, 11; B. Zhou: Johnson & Johnson, 3, 11; M. Javidi: Johnson & Johnson, 3, 11; C. Valiathan: Johnson & Johnson, 3, 11; C. Iaconangelo: Johnson & Johnson, 3, 11; Y. Yang: Johnson & Johnson, 3, 11; A. Kannan: Johnson & Johnson, 3, 11; C. Karyekar: Johnson & Johnson, 3, 11; T. Shagroni: Johnson & Johnson, 3, 11.

To cite this abstract in AMA style:

Merola J, Mease P, Coates L, McInnes I, Nash P, Ogdie A, Eder L, kishimoto m, Beutler A, Psachoulia K, Sheng S, Zhou B, Javidi M, Valiathan C, Iaconangelo C, Yang Y, Kannan A, Karyekar C, Shagroni T. Icotrokinra (ICO), a Novel Targeted Oral Peptide, in Patients (Pts) With Psoriatic Disease: Exploratory Assessments From a Phase 2 Psoriasis (PsO) Study Informing a Phase 3 Clinical Program in Psoriatic Arthritis (PsA) [abstract]. Arthritis Rheumatol. 2025; 77 (suppl 9). https://acrabstracts.org/abstract/icotrokinra-ico-a-novel-targeted-oral-peptide-in-patients-pts-with-psoriatic-disease-exploratory-assessments-from-a-phase-2-psoriasis-pso-study-informing-a-phase-3-clinical-program-in-psoriat/. Accessed .

ACR Meeting Abstracts - https://acrabstracts.org/abstract/icotrokinra-ico-a-novel-targeted-oral-peptide-in-patients-pts-with-psoriatic-disease-exploratory-assessments-from-a-phase-2-psoriasis-pso-study-informing-a-phase-3-clinical-program-in-psoriat/

My Favorites

Save and print abstracts during your browser session by clicking the “Favorite” button at the bottom of any abstract (must have cookies enabled in browser). See saved favorites.

Abstract Policies

  • ACR Convergence Abstract Embargo Policies
  • ACR Convergence Abstract Permissions & Reprints
  • PRSYM Abstract Policies

ACR Convergence. Where Rheumatology Meets

ACR Convergence 2026

Join us November 6-11 in Orlando, Florida.
See Registration Information

  • Contact ACR
  • Privacy Policy
  • ACR Policies
  • Cookie Preferences

© Copyright 2026 American College of Rheumatology