
Session Information
Date: Monday, November 11, 2019
Title: RA – Diagnosis, Manifestations, & Outcomes Poster II: Treatments, Outcomes, & Measures
Session Type: Poster Session (Monday)
Session Time: 9:00AM-11:00AM
Background/Purpose: The Patient Activity Scale (PAS)-II is an accepted disease activity measure used in the care of patients with rheumatoid arthritis (RA). A clinically important change in this score has not been defined for patients with RA. We aimed to define the Minimal Clinically Important Improvement (MCII) and Worsening (MCIW) for the PAS-II using anchor- and distribution-based methods.
Methods: Data from Forward, The National Databank for Rheumatic Diseases was utilized. Data are collected at 6-month intervals by questionnaires. Data shown in these analyses spans four 6-month data collection periods: (A) January 2017 (n = 3680, (B) July 2017 (n = 3504), (C) January 2018 (n = 3737), and (D) July 2018 (n = 3102). Both anchor-based and distribution-based methods were used to estimate MCII and MCIW. For the anchor-based analyses, the primary anchors used were comparisons of pain and general health to six months ago (e.g., “Compared to 6 months ago, would you say your pain is: much better now, somewhat better now, about the same, somewhat worse, or much worse?”). Mean changes in PAS-II scores and effect sizes were summarized and averaged over the 4 change periods. For the distribution-based calculations, we used 0.5 and 0.35 standard deviations. We further stratified analyses based on PAS-II score (above/below 3.7), hypothesizing that the MCII and MCIW would be dependent on the baseline PAS-II score.
Results: The population (baseline from Period A, n=3680) average age was 64.9 (12.0) years with an average disease duration of 20.8 (12.7) years and an average PAS-II of 3.3 (2.2). The population was 83.1% female, 91.3% white and 43% ever-smokers. For pain and health-related anchor questions, the MCIW was defined as approximately 0.50 to 0.55, respectively (Table 1), representing a small effect size (d=0.23-0.25). The MCII was defined as 0.39 to 0.45 (d=0.18, 0.21), respectively. Stratifying by the PAS-II score affected the results obtained by anchor-based methods. The MCIW for anchor-based methods among participants in low disease activity (< 3.7) was approximately 1.1 [1.09/1.11 (pain/general health)], while the MCII for those in moderate to high disease activity ( >3.7) was 1.09 (1.15/1.02) (Table 2). These changes represented a large effect size. Distribution-based methods for 0.5 SD and 0.35 SD were 1.08 and 0.76, respectively. Results were similar in each 6-month data collection periods.
Conclusion: We defined minimal clinically important change for the PAS-II as a change in the score of 0.5 units. Among participants with moderate to high PAS-II, the MCII was estimated to be 1.1 and among participants with in low disease activity, the MCIW was 1.1. These data suggest that only a more substantial worsening is likely be important to patients that report low activity. Similarly, only a substantial improvement will be important to patients who report high activity. The characterization of clinically meaningful changes in disease activity is important for clinical research studies and clinical settings where this disease assessment is used.

MCII MCIW PASII Abstract_Table 1
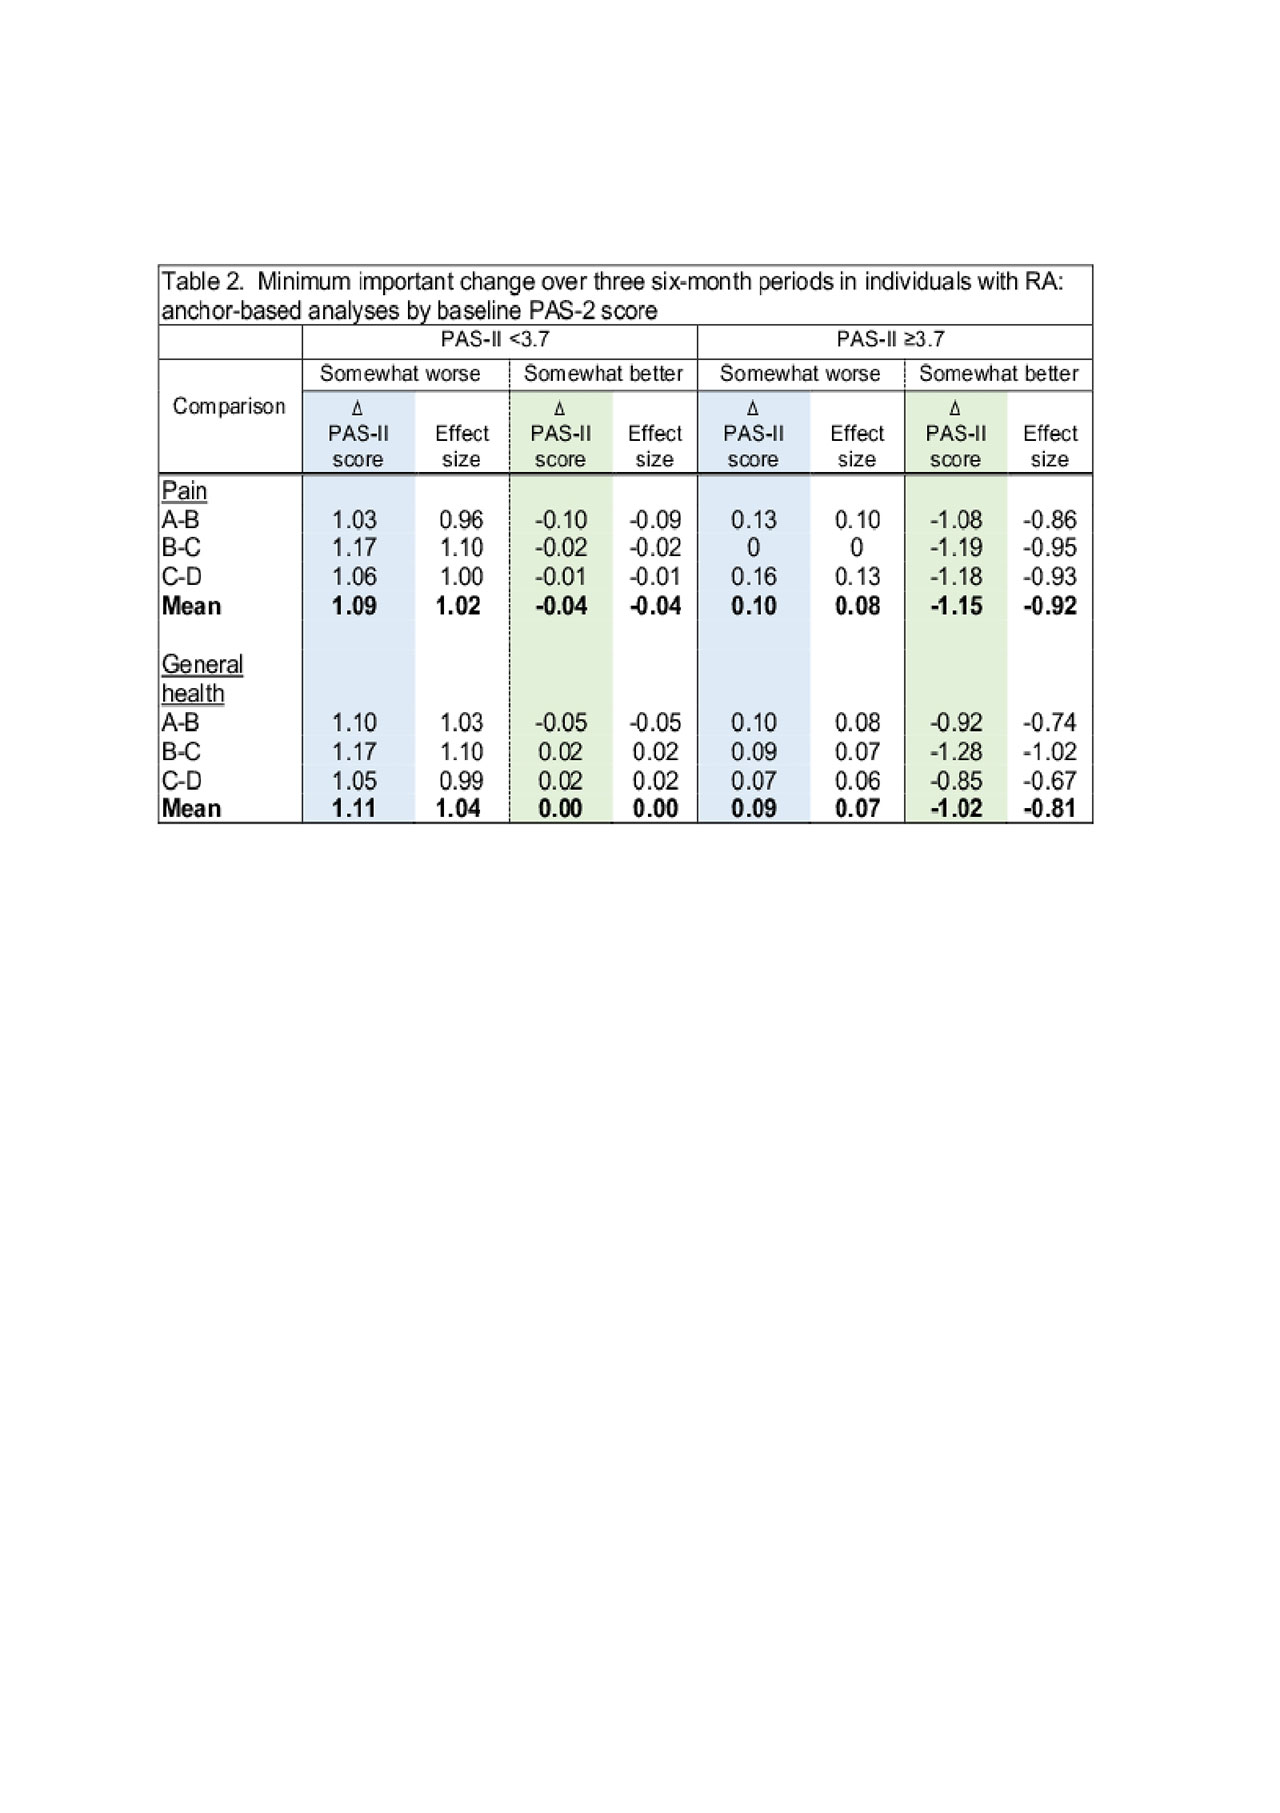
MCII MCIW PASII Abstract_Table 2
To cite this abstract in AMA style:
Baker J, Katz P, Michaud K. Defining Minimal Clinically Important Changes for the Patient Activity Scale-II [abstract]. Arthritis Rheumatol. 2019; 71 (suppl 10). https://acrabstracts.org/abstract/defining-minimal-clinically-important-changes-for-the-patient-activity-scale-ii/. Accessed .ACR Meeting Abstracts - https://acrabstracts.org/abstract/defining-minimal-clinically-important-changes-for-the-patient-activity-scale-ii/