
Session Information
Date: Monday, October 27, 2025
Title: (1088–1122) Immunological Complications of Medical Therapy Poster
Session Type: Poster Session B
Session Time: 10:30AM-12:30PM
Background/Purpose: Immune checkpoint inhibitor (ICI) induced myositis is the ICI rheumatic toxicity with the greatest case mortality rate, especially when associated with myocarditis and/or myasthenia gravis (MG). Presentation, progression and treatment for ICI-myositis/myocarditis/myasthenia gravis overlap syndrome (IMOS) is poorly understood. We aim to better understand IMOS clinical presentation, evaluation and disease progression.
Methods: This is a retrospective, single center, observational study investigating patients with IMOS defined as patients with history of ICI treatment for cancer and development of some combination of ICI-myositis, myocarditis and/or MG overlap. We included adult patients with ICI therapy for cancer between 1/1/2011 and 4/1/2025. IMOS diagnosis was determined by the multidisciplinary treating team of clinicians. We examined demographics, presenting syndrome, clinical evaluation, treatment and outcomes as available in clinical annotations. Data were analyzed using descriptive statistics.
Results: Of 35 patients with either ICI-induced myositis, myocarditis or MG, 10 patients had overlap and fit definition of IMOS: four patients with ICI-myositis, myocarditis and MG (Triple M); three with myocarditis/myositis, three with myocarditis/MG (Table 1). Only three patients (30%) were diagnosed with overlap syndrome at initial diagnosis, with the other seven (70%) being diagnosed sequentially (Table 2). Initial creatine kinase (CK) was elevated in all patients (median 2507, IQR 894, 5543), even in patients without myositis. Median time to steroids after symptom onset was 4 days (IQR 3-6) and time from symptoms to steroid sparing agent was 13 days (IQR 7-15). IVIg was the most frequently used steroid-sparing agent (37.5%). Overall, eight patients (80%) died during the follow up period, with six deaths (60%) attributed to IMOS. The myocarditis/MG had the highest mortality at follow-up (100%) followed by Triple M (75%) and then myocarditis/myositis (67%).
Conclusion: Our findings reflect high mortality with IMOS, especially with myocarditis/MG overlap. High CK was prevalent even without myositis and 70% of patients had sequential rather than simultaneous diagnosis of the overlap syndrome. Delay in steroid sparing agent initiation may be a result of time necessary for multidisciplinary conversations and ambivalence in optimal second line therapy. Future research will require higher-powered multi-institutional study to identify the most effective and safe therapies for IMOS.
 Figure 1: Most patients required therapy beyond systemic steroids. The steroid-sparing therapies ranged for the immune checkpoint inhibitor (ICI) associated Myositis/Myocarditis/Myasthenia Gravis (MG) Overlap Syndrome (IMOS) as depicted here.
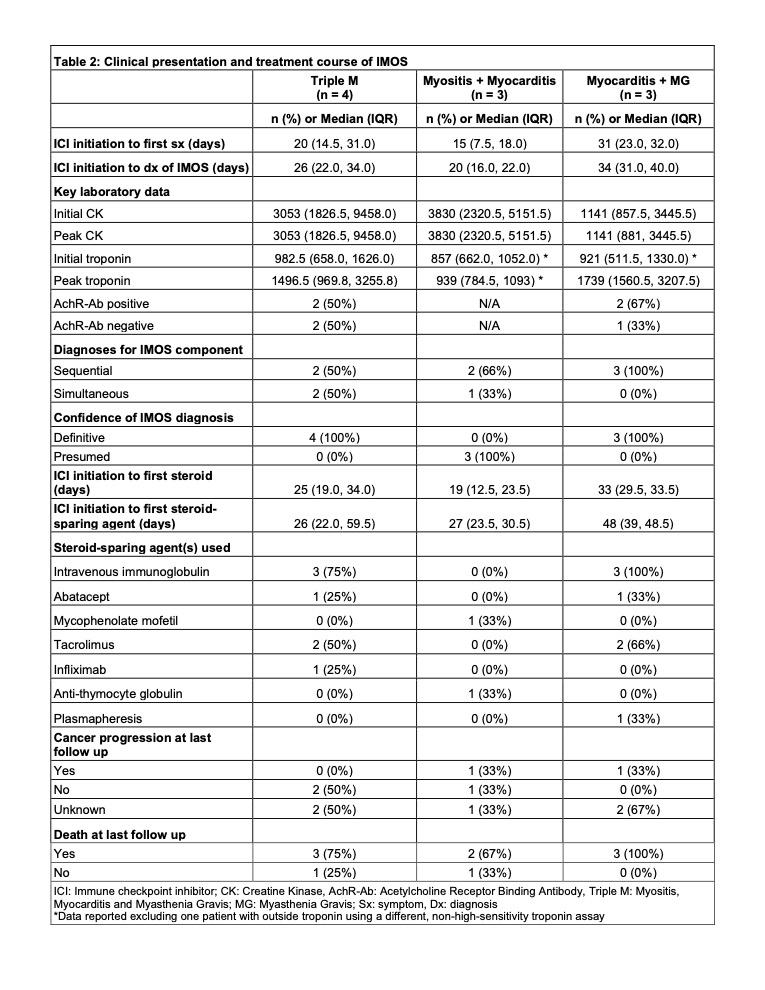 Table 1: Baseline characteristics for the 10 patients with immune checkpoint inhibitor (ICI) associated Myositis/Myocarditis/Myasthenia Gravis (MG) Overlap Syndrome (IMOS) as depicted here.
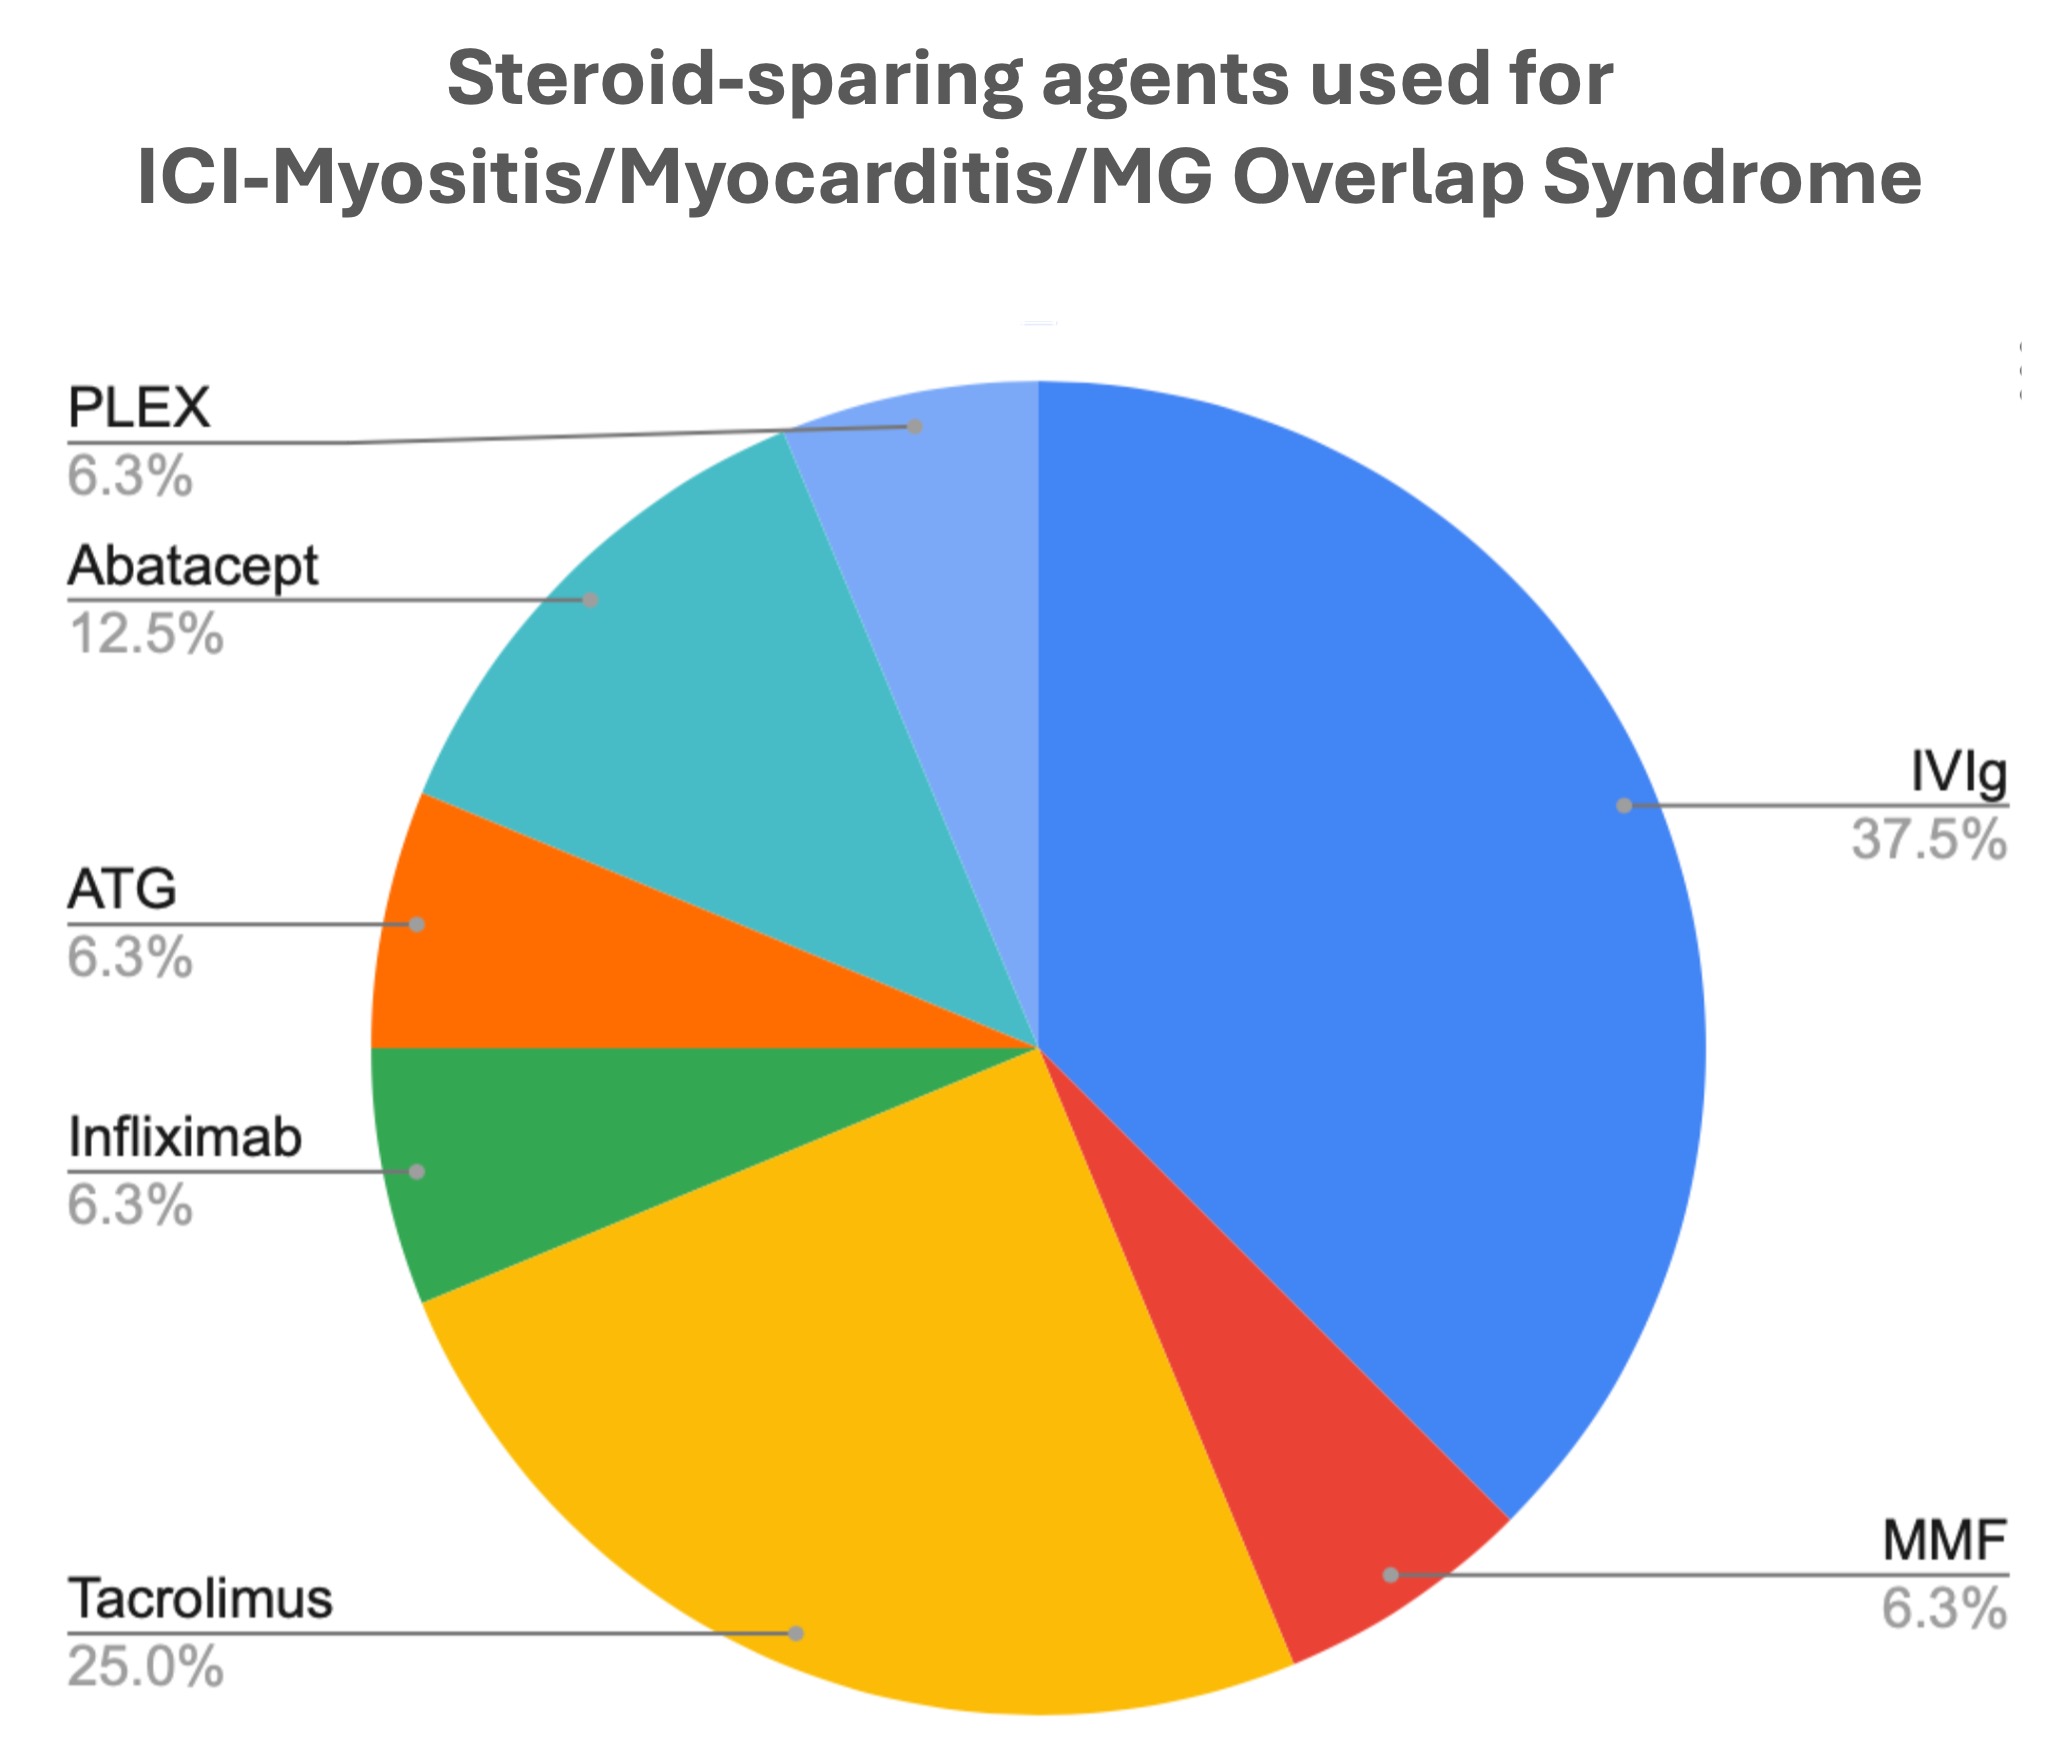 Table 2: Outcomes for the 10 patients with Myositis/Myocarditis/Myasthenia Gravis (MG) Overlap Syndrome (IMOS), organized by predominant syndrome of Triple M, Myocarditis + Myositis, and Myocarditis + Myasthenia Gravis.
To cite this abstract in AMA style:
Ivanovic M, Shao D, Wang A, Smuda C, Reid P. Checkpoint Inhibitor Induced Myocarditis with Myositis/Myasthenia Gravis Concurrence: An Observational Study [abstract]. Arthritis Rheumatol. 2025; 77 (suppl 9). https://acrabstracts.org/abstract/checkpoint-inhibitor-induced-myocarditis-with-myositis-myasthenia-gravis-concurrence-an-observational-study/. Accessed .ACR Meeting Abstracts - https://acrabstracts.org/abstract/checkpoint-inhibitor-induced-myocarditis-with-myositis-myasthenia-gravis-concurrence-an-observational-study/