ACR Meeting Abstracts

ACR Meeting Abstracts

  • Meeting Abstracts
    • All Meetings
    • ACR Convergence 2026
    • PRSYM 2026
    • ACR Convergence 2025
    • Download Abstract Supplements
  • Keyword Index
  • My Favorites
    • View & print my favorites
  • Search

Home » Meeting Abstracts » ACR Convergence 2023

Abstract Number: 2250

Bimekizumab Impact on Health-Related Quality of Life and Physical Function in Patients with Active Psoriatic Arthritis Who Were Biologic DMARD‑Naïve or Had Inadequate Response or Intolerance to TNF-α Inhibitors: 1-Year Results from Two Phase 3, Randomized Studies

Dafna Gladman1, Laure Gossec2, M. Elaine Husni3, Lars Erik4, Paolo Gisondi5, Alice B. Gottlieb6, Diamant Thaçi7, Barbara Ink8, Rajan Bajracharya8, Jérémy Lambert9, Nikos Lyris8, Jason Coarse10 and William R Tillett11, 1Schroeder Arthritis Institute, Krembil Research Institute, Toronto Western Hospital, Department of Medicine, University of Toronto, Toronto, ON, Canada, 2Sorbonne Université and Pitié Salpêtrière Hospital, Paris, France, 3Cleveland Clinic / Department of Rheumatic and Immunologic Diseases, Cleveland, OH, 4Bispebjerg-Frederiksberg Hospital, Vedbæk, Denmark, 5Università di Verona, Verona, Italy, 6Icahn School of Medicine at Mount Sinai, New York, NY, 7Institute and Comprehensive Center for Inflammation Medicine, University of Lübeck, Lübeck, Germany, 8UCB Pharma, Slough, United Kingdom, 9UCB Pharma, Irigny, France, 10UCB Pharma, Morrisville, NC, 11Department of Rheumatology, Royal National Hospital for Rheumatic Diseases, Bath, United Kingdom

Share on X (Twitter) Share on Facebook Share on LinkedIn Share on Email
Print

Meeting: ACR Convergence 2023

Keywords: Psoriatic arthritis, quality of life, spondyloarthritis

Session Information

Date: Tuesday, November 14, 2023

Title: (2227–2256) Spondyloarthritis Including Psoriatic Arthritis – Treatment: SpA Poster III

Session Type: Poster Session C

Session Time: 9:00AM-11:00AM

Background/Purpose: PsA has a substantial negative impact on patient (pt) health-related quality of life (HRQoL);1 symptom control, preventing structural damage, and normalizing physical and social function to maximize HRQoL are key treatment goals.2 Bimekizumab (BKZ), a monoclonal IgG1 antibody that selectively inhibits IL-17F in addition to IL-17A, has demonstrated clinically relevant improvements in HRQoL measures to Week (Wk) 16 vs placebo (PBO) in pts with PsA in two phase 3 trials.3,4 In this study, the impact of BKZ treatment on HRQoL is reported up to 1 year.

Methods: The phase 3 BE OPTIMAL (NCT03895203) and BE COMPLETE (NCT03896581) trials, both with a 16-wk double-blind, PBO-controlled phase, assessed BKZ in pts with PsA who were biologic DMARD (bDMARD)-naïve or had intolerance or inadequate response to TNF-α inhibitors (TNFi‑IR), respectively. BE OPTIMAL pts were randomized 3:2:1 to subcutaneous (sc) BKZ 160 mg every 4 wks (Q4W), PBO, or reference (sc adalimumab 40 mg Q2W; data not reported). At Wk 16, PBO pts switched to BKZ (PBO/BKZ). BE COMPLETE pts were randomized 2:1 to sc BKZ 160 mg Q4W or PBO. Pts completing Wk 16 were eligible to enter an open‑label extension, BE VITAL (NCT04009499), when PBO pts switched to BKZ (PBO/BKZ). BE COMPLETE plus BE VITAL is referred to as ‘BE COMPLETE’ hereafter.

Endpoints reported for HRQoL, health status, and physical function included Short-Form 36-Item Health Survey (SF-36) Physical and Mental Component Summaries (PCS; MCS) and subscale norm-based scores; PsA Impact of Disease 12‑item (PsAID-12); EuroQol-5 Dimensions-3 Level Visual Analog Scale (EQ-5D-3L VAS); PsA Quality of Life (PsAQoL); HAQ-Disability Index (HAQ-DI). BE COMPLETE outcomes were collected to Wk 40/52 as stated in the Table. Non-responder and multiple imputation (NRI; MI) were used for missing binary and continuous variables.

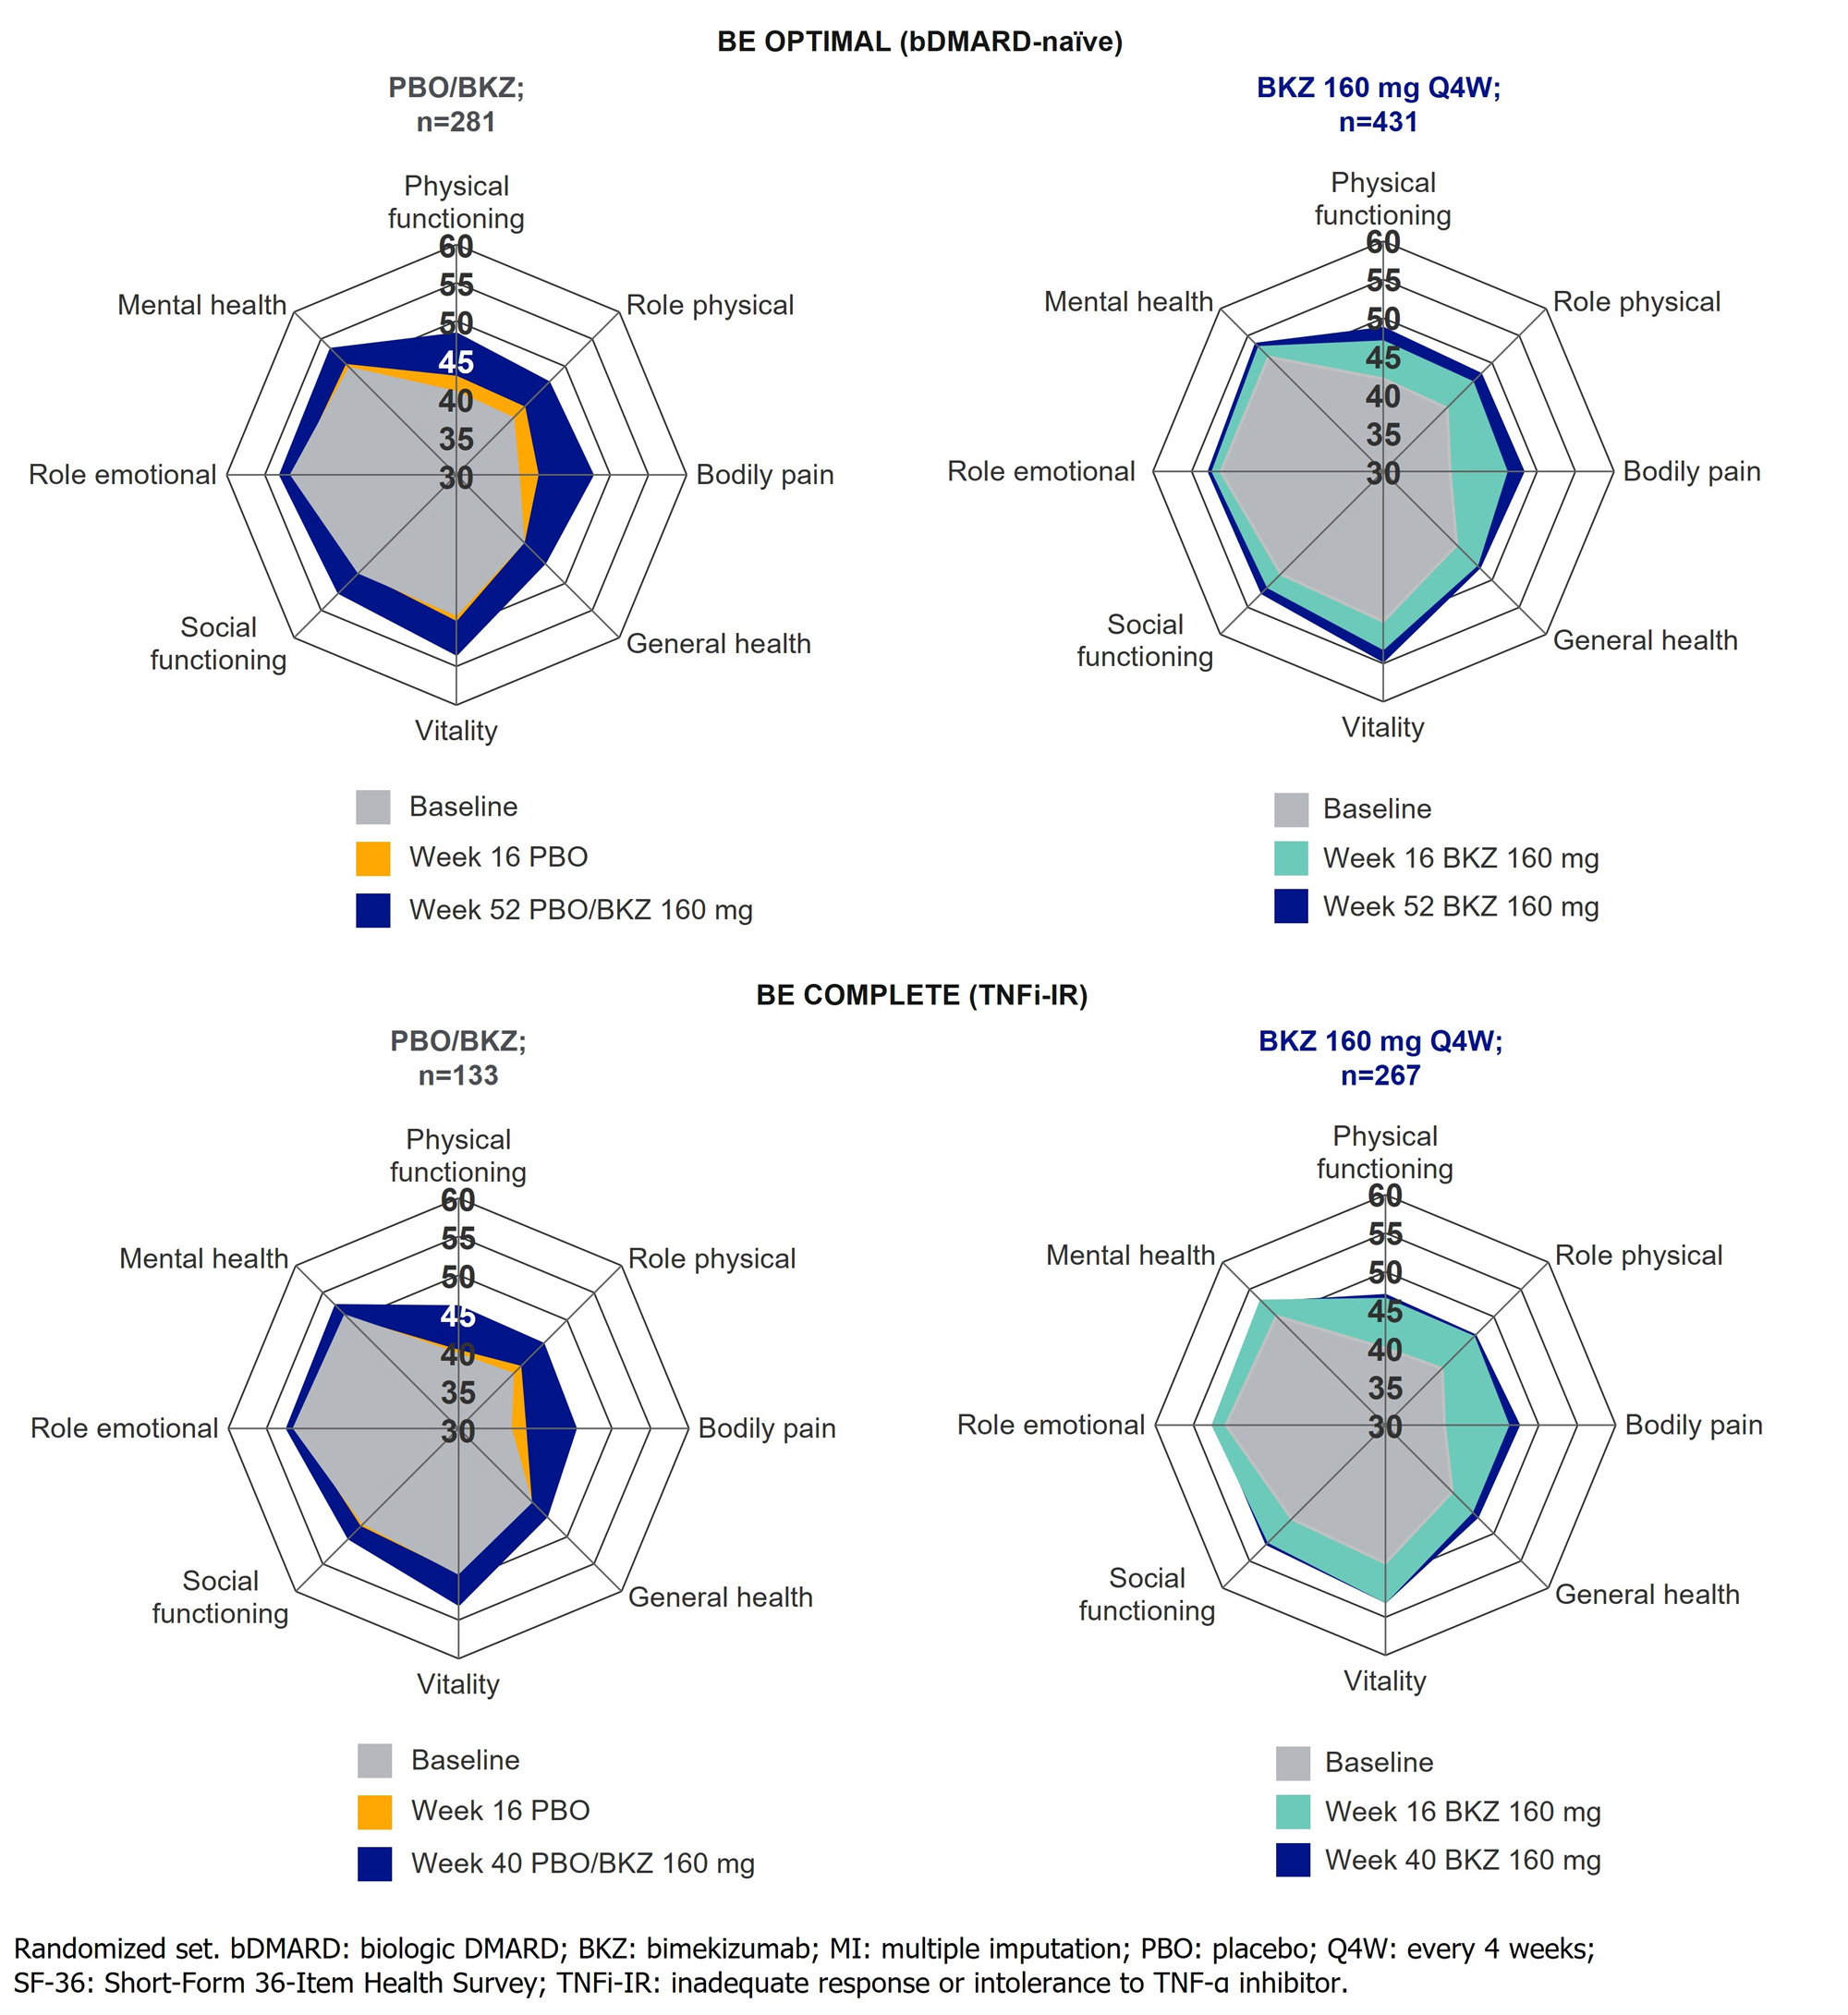
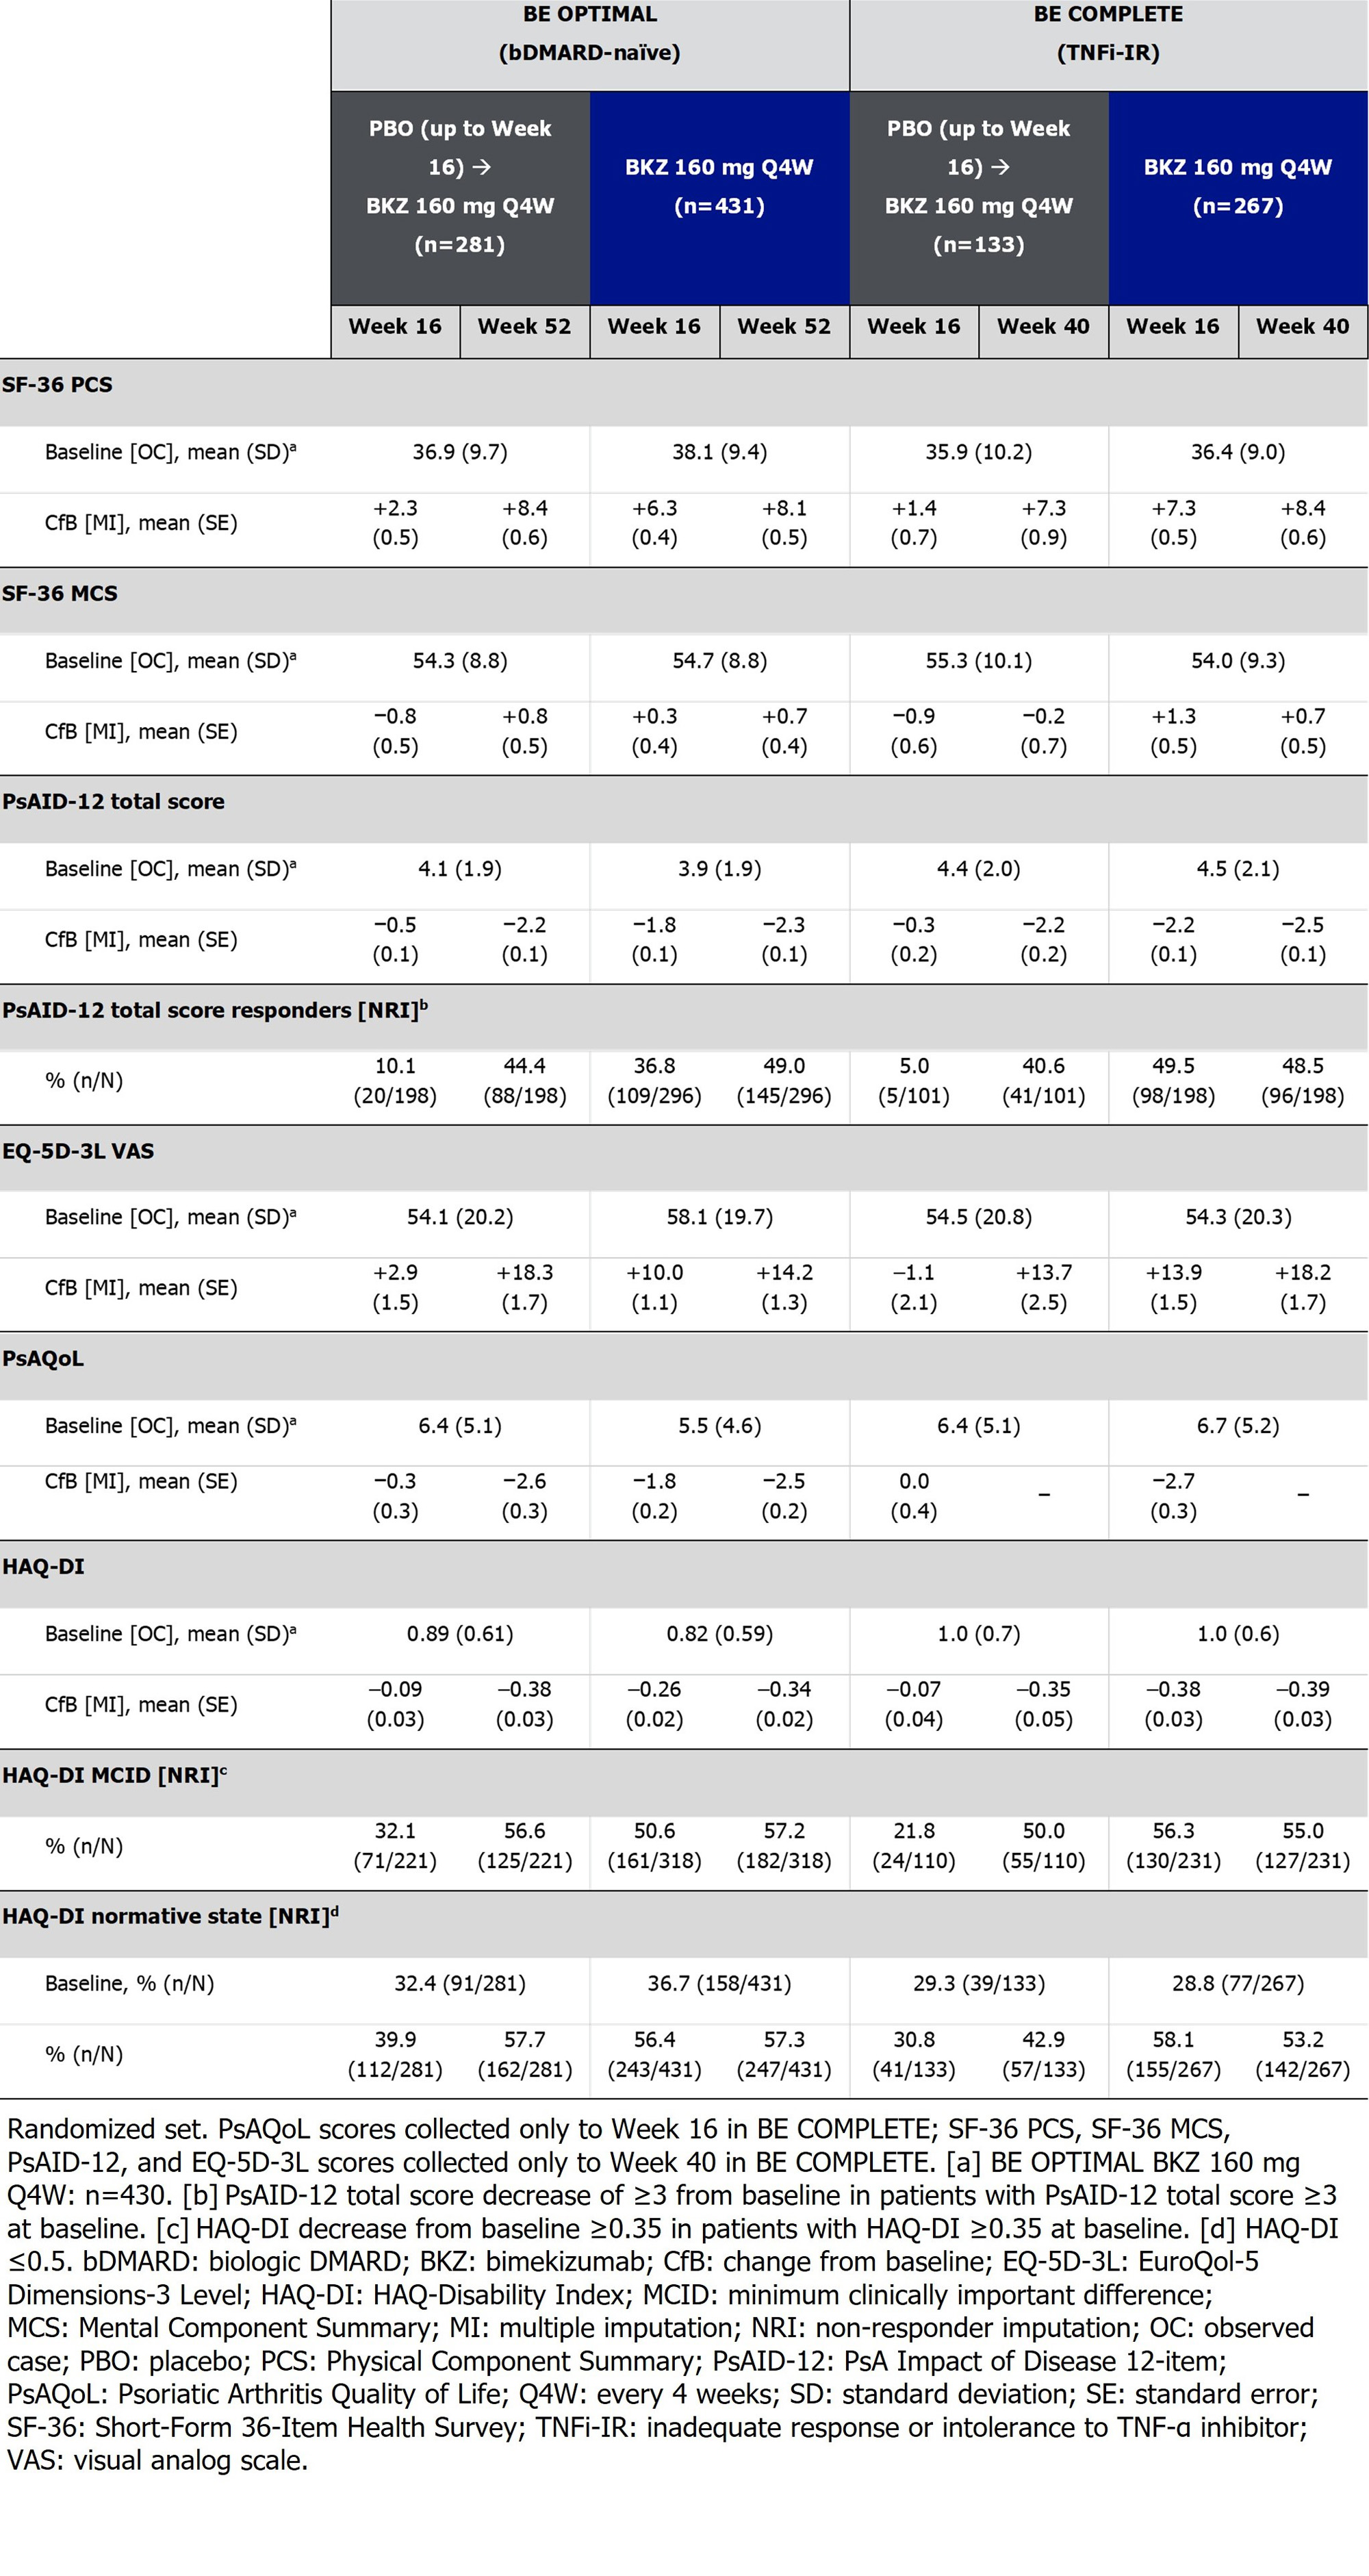
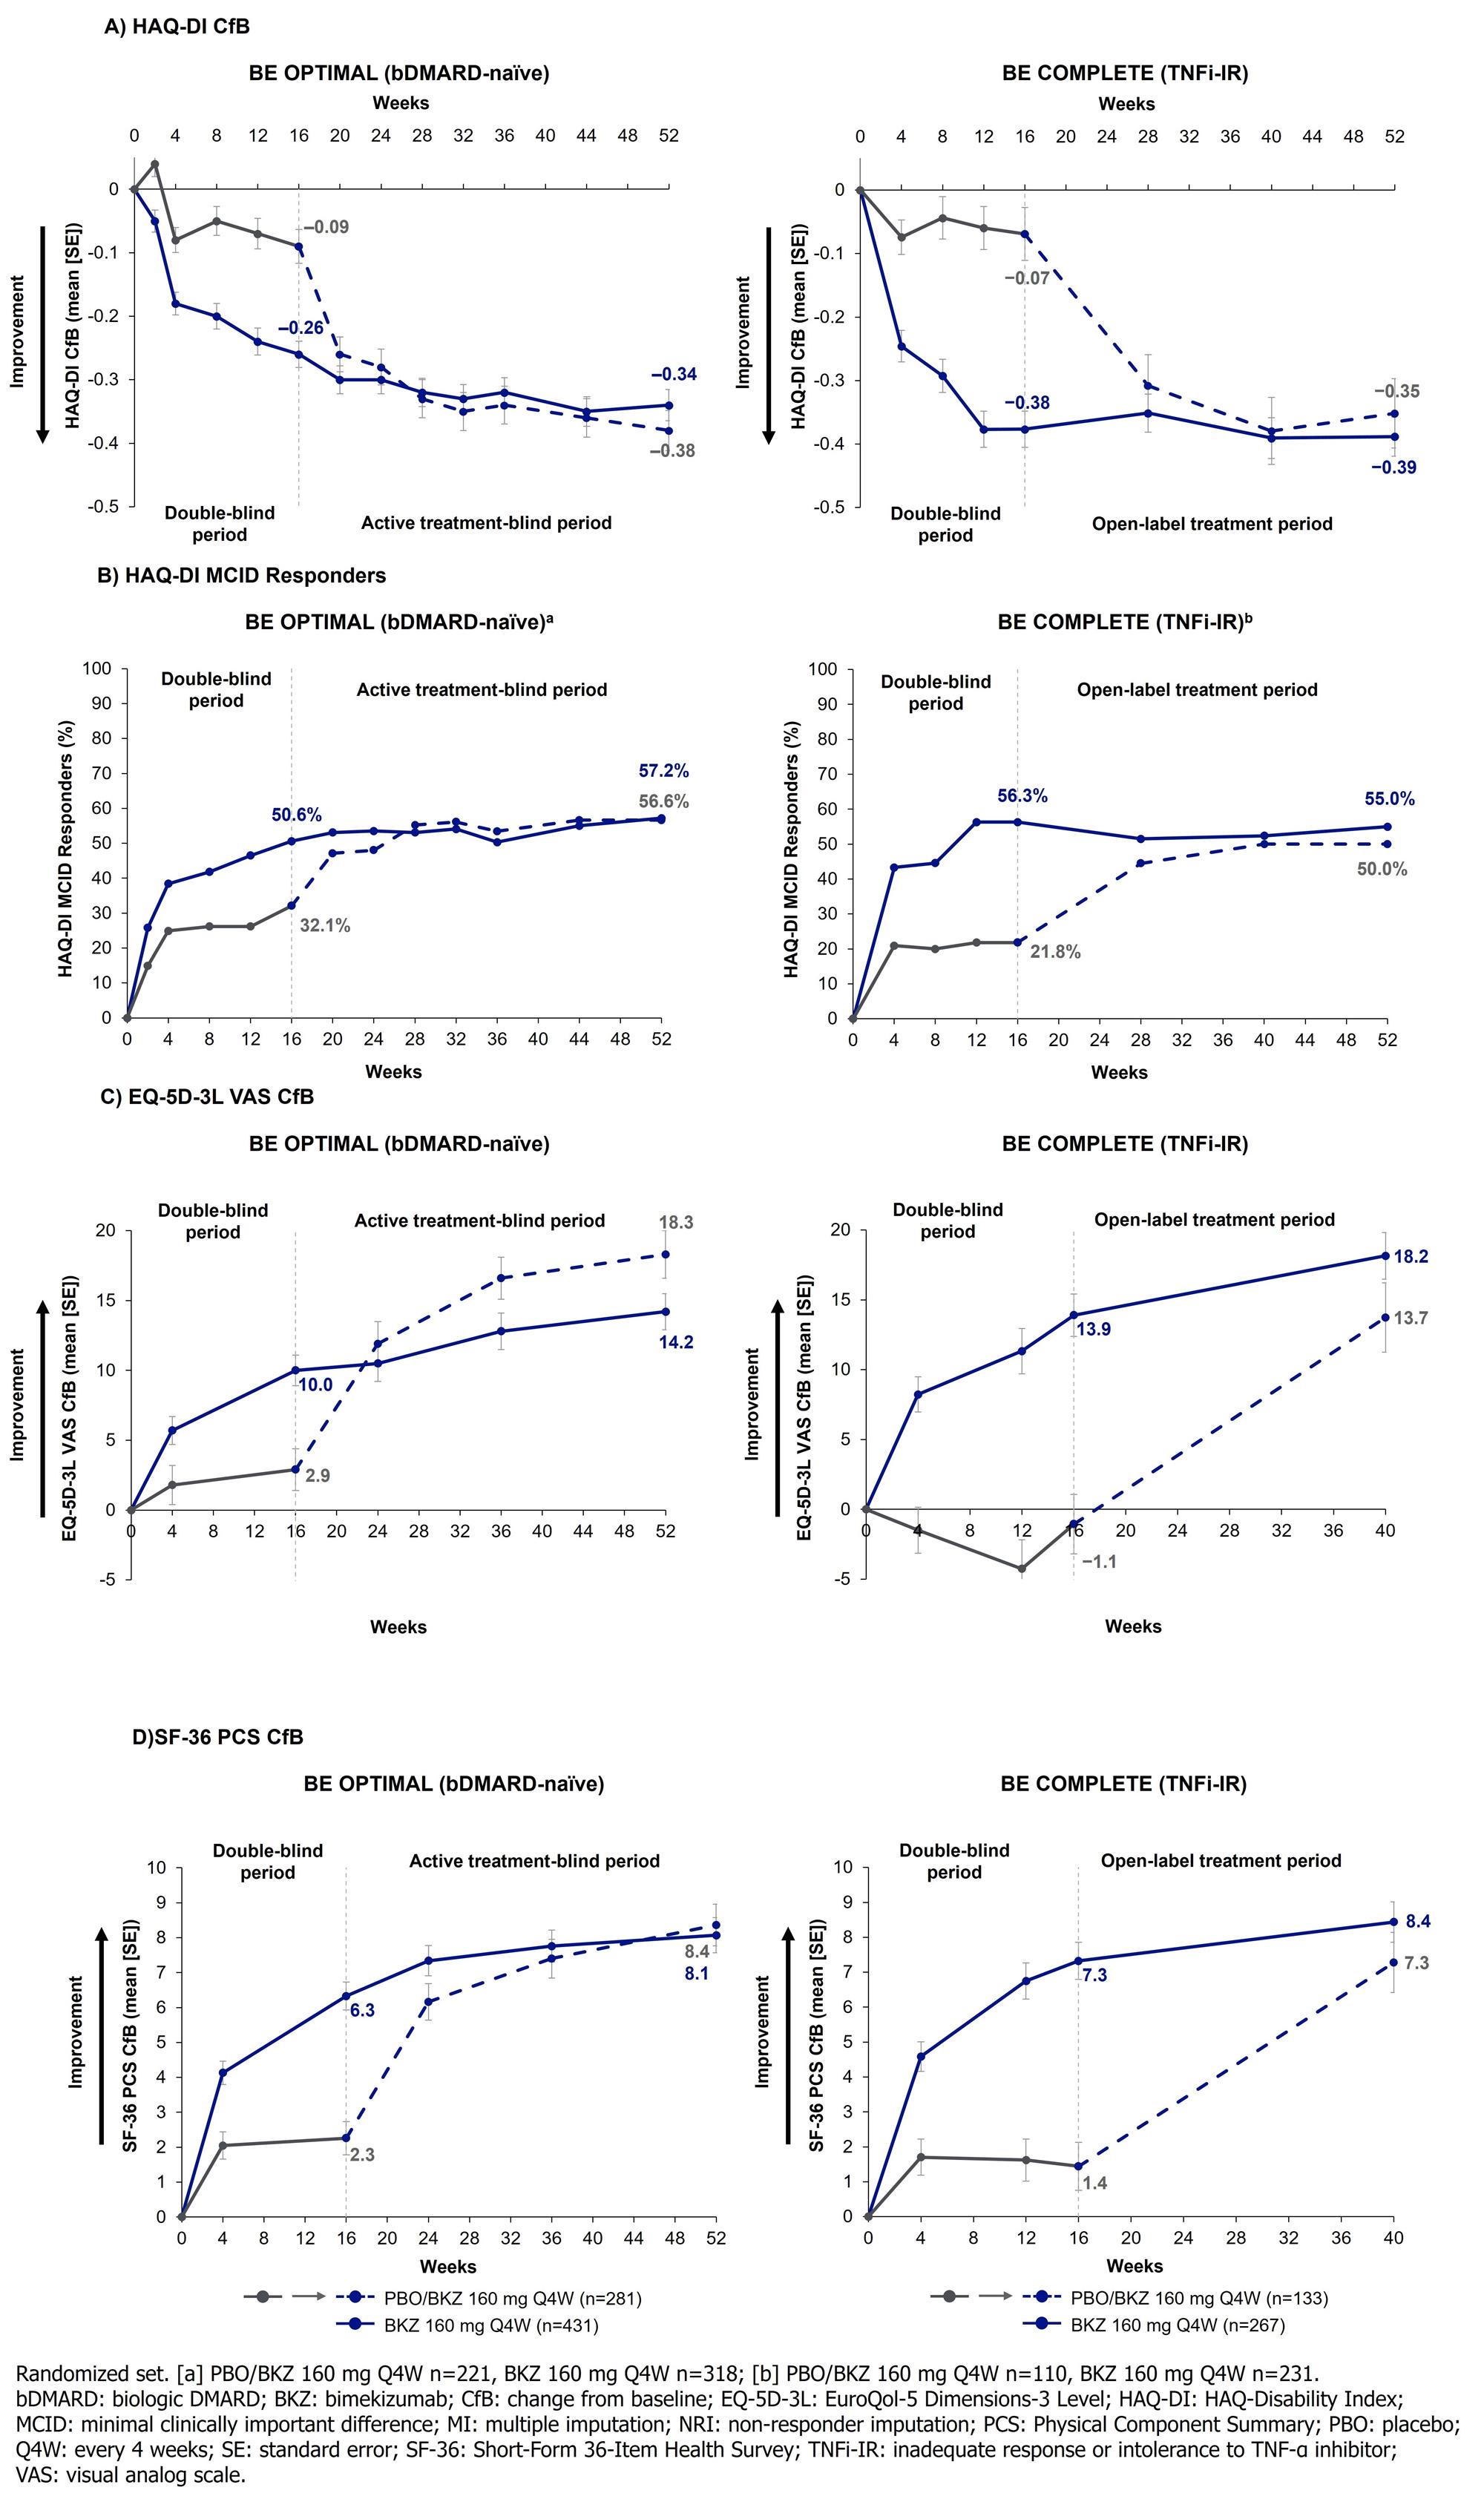
Results: Overall, 770/852 (90.4%) and 347/400 (86.8%) pts completed Wk 52 of BE OPTIMAL and BE COMPLETE. Across both trials, Wk 16 improvements in HRQoL, health status, and physical function were sustained to Wk 52 on BKZ (Table). PBO/BKZ pts achieved comparable improvements to BKZ-randomized pts by Wk 52/40, including PsAID-12 total score response (decrease from baseline ≥3; bDMARD-naïve/TNFi-IR BKZ: 49.0/48.5%, PBO/BKZ: 44.4/40.6%), HAQ-DI minimal clinically important difference (MCID; decrease from baseline ≥0.35; BKZ:‍ 57.2/55.0%, PBO/BKZ: 56.6/50.0%; Figure 1), and reaching HAQ-DI normative state of ≤0.5 (BKZ:‍ 57.3/53.2%, PBO/BKZ: 57.7/42.9%). SF-36 PCS improved to a greater extent at Wk 16 in BKZ vs PBO pts (Figure 1); responses were sustained to Wk 52 on BKZ. SF-36 physical functioning, role physical, and bodily pain subscales showed the most improvement over the other subscales (Figure 2). Similar improvement trends were seen in EQ-5D-3L VAS (Table; Figure 1).

Conclusion: Clinically meaningful improvements in measures of HRQoL, health status, and physical function were observed up to 1 year with BKZ treatment, irrespective of prior bDMARD use.

References:1.Gudu T. Expert Rev Clin Immunol 2018;14:405–17; 2. Gossec L. Ann Rheum Dis 2020;79:700–12; 3.McInnes IB. Lancet 2023;401:25–37; 4. Merola JF. Lancet 2023;401:38–48.
Supporting image 1

Table. Health-related quality of life, physical function, and health status measures at baseline, Week 16, and Week 40/52 (MI, NRI, OC)

Supporting image 2

Figure 1. Change from baseline HAQ-DI (A), proportion of HAQ-DI MCID responders (B), change from baseline EQ-5D_3L VAS (C), and change from baseline SF_36 PCS (D) to Week 40/52 (MI/NRI)

Supporting image 3

Figure 2. SF_36 single-item subscale scores at baseline, Week 16, and Week 40/52 (MI)


Disclosures: D. Gladman: AbbVie, 2, 5, Amgen, 2, 5, Bristol Myers Squibb, 2, Celgene, 2, 5, Eli Lilly, 2, 5, Galapagos, 2, Gilead Sciences, 2, Janssen, 2, 5, Novartis, 2, 5, Pfizer Inc, 2, 5, UCB, 2, 5; L. Gossec: AbbVie, 2, 12, Personal fees, Amgen, 2, Biogen, 5, BMS, 12, Personal fees, Celltrion, 12, Personal fees, Eli Lilly, 5, 12, Personal fees, Galapagos, 12, Personal fees, Janssen, 12, Personal fees, MSD, 12, Personal fees, Novartis, 5, 12, Personal fees, Pfizer, 12, Personal fees, Sandoz, 5, 12, Personal fees, UCB Pharma, 5, 12, Personal fees; M. Husni: AbbVie, 1, 2, Amgen, 1, 2, Bristol-Myers Squibb, 1, 2, Eli Lilly, 1, 2, Janssen, 1, 2, Novartis, 1, 2, Pfizer, 1, 2, UCB, 1, 2; L. Erik: AbbVie, 2, 5, 6, Amgen, 2, 6, Biogen, 2, 6, Bristol-Myers Squibb, 2, 6, Eli Lilly, 2, 5, 6, Gilead, 2, 6, Janssen, 2, 6, MSD, 2, 6, Novartis, 2, 5, 6, Pfizer, 2, 6, UCB, 2, 5, 6; P. Gisondi: AbbVie, 2, Abiogen, 2, Almirall, 2, Celgene, 2, Eli Lilly, 2, Janssen, 2, LEO Pharma, 2, Merck, 2, MSD, 2, Novartis, 2, Otsuka, 2, Pfizer, 2, Pierre Fabre, 2, Sanofi, 2, UCB Pharma, 2; A. Gottlieb: Amgen, 1, 2, AnaptysBio, 1, 2, 5, Avotres Therapeutics, 1, 2, Boehringer Ingelheim, 1, 2, Bristol Myers Squibb, 1, 2, 5, Dice Therapeutics, 1, 2, Eli Lilly, 1, 2, Janssen, 1, 2, MoonLake Immunotherapeutics, 5, Novartis, 1, 2, 5, Sanofi, 1, 2, UCB Pharma, 1, 2, 5, XBiotech, 1, 2; D. Thaçi: AbbVie, 1, 2, 5, 12, Investigator, Almirall, 1, 2, 12, Investigator, Amgen, 1, 2, 12, Investigator, Boehringer-Ingelheim, 1, 2, 12, Investigator, Bristol-Myers Squibb(BMS), 1, 2, 12, Investigator, Celltrion, 1, 2, 12, Investigator, Eli Lilly, 1, 2, 12, Investigator, Galapagos, 1, 2, 12, Investigator, Galderma, 1, 2, 5, 12, Investigator, Janssen-Cilag, 1, 2, 12, Investigator, LEO Pharma, 1, 2, 5, 12, Investigator, Novartis, 1, 2, 5, 12, Investigator, Pfizer, 1, 2, 12, Investigator, Regeneron, 1, 2, 12, Investigator, Samsung, 1, 2, 12, Investigator, Sandoz, 1, 2, 12, Investigator, Sanofi, 1, 2, 12, Investigator, Target-Solution, 1, 2, 12, Investigator, UCB, 1, 2, 12, Investigator; B. Ink: AbbVie, 11, GSK, 11, UCB Pharma, 3, 11; R. Bajracharya: UCB Pharma, 3, 11; J. Lambert: UCB Pharma, 3, 11; N. Lyris: UCB Pharma, 3; J. Coarse: UCB Pharma, 3, 11; W. Tillett: AbbVie, 2, 5, 6, Amgen, 2, 5, 6, Celgene, 2, 5, 6, Eli Lilly, 2, 5, 6, GSK, 2, 5, 6, Janssen, 2, 5, 6, MSD, 2, 5, 6, Novartis, 2, 5, 6, Ovo Pharma, 2, 5, 6, Pfizer, 2, 5, 6, UCB Pharma, 2, 5, 6.

To cite this abstract in AMA style:

Gladman D, Gossec L, Husni M, Erik L, Gisondi P, Gottlieb A, Thaçi D, Ink B, Bajracharya R, Lambert J, Lyris N, Coarse J, Tillett W. Bimekizumab Impact on Health-Related Quality of Life and Physical Function in Patients with Active Psoriatic Arthritis Who Were Biologic DMARD‑Naïve or Had Inadequate Response or Intolerance to TNF-α Inhibitors: 1-Year Results from Two Phase 3, Randomized Studies [abstract]. Arthritis Rheumatol. 2023; 75 (suppl 9). https://acrabstracts.org/abstract/bimekizumab-impact-on-health-related-quality-of-life-and-physical-function-in-patients-with-active-psoriatic-arthritis-who-were-biologic-dmard%e2%80%91naive-or-had-inadequate-response-or-intolerance-t/. Accessed .

ACR Meeting Abstracts - https://acrabstracts.org/abstract/bimekizumab-impact-on-health-related-quality-of-life-and-physical-function-in-patients-with-active-psoriatic-arthritis-who-were-biologic-dmard%e2%80%91naive-or-had-inadequate-response-or-intolerance-t/

My Favorites

Save and print abstracts during your browser session by clicking the “Favorite” button at the bottom of any abstract (must have cookies enabled in browser). See saved favorites.

Abstract Policies

  • ACR Convergence Abstract Embargo Policies
  • ACR Convergence Abstract Permissions & Reprints
  • PRSYM Abstract Policies

ACR Convergence. Where Rheumatology Meets

ACR Convergence 2026

Join us November 6-11 in Orlando, Florida.
See Registration Information

  • Contact ACR
  • Privacy Policy
  • ACR Policies
  • Cookie Preferences

© Copyright 2026 American College of Rheumatology